Related Experiment Video
Updated: May 1, 2026
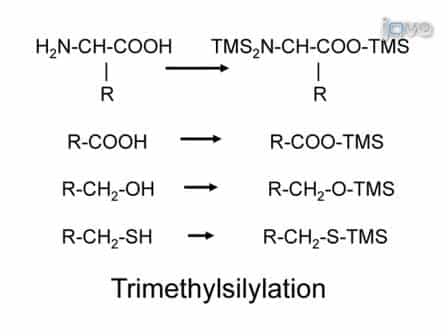

One-step Metabolomics: Carbohydrates, Organic and Amino Acids Quantified in a Single Procedure
Published on: June 25, 2010
Newborn screening for galactosemia in the United States: looking back, looking around, and looking ahead
Brook M Pyhtila1, Kelly A Shaw, Samantha E Neumann
1Department of Human Genetics, Emory University School of Medicine, Atlanta, GA, 30322, USA.

Insights
Newborn screening for galactosemia has saved thousands of lives, but inconsistencies in follow-up testing and intervention for Duarte galactosemia persist. Standardizing these practices is crucial for improved infant health outcomes.
Area of Science:
- Biochemistry
- Genetics
- Public Health
Background:
- Newborn screening (NBS) for galactosemia has been implemented nationwide, identifying over 2,500 infants with classic galactosemia.
- Early diagnosis and intervention through NBS have significantly improved outcomes, preventing severe disease complications.
Purpose of the Study:
- To compare galactosemia screening and follow-up data across 39 NBS programs in the US.
- To identify disparities in screening approaches and intervention recommendations for galactosemia, particularly Duarte galactosemia (DG).
Main Methods:
- Data collection from 39 US newborn screening programs.
- Comparative analysis of screening protocols, detection rates, and follow-up recommendations for galactosemia and DG.
Main Results:
- All surveyed programs identify classic galactosemia at a similar rate (approx. 1/50,000) and recommend lifelong galactose restriction.
- Significant variation exists in Duarte galactosemia detection rates and recommended interventions, with over 80% recommending some dietary restriction for the first year.
Conclusions:
- While NBS for galactosemia is a success, inconsistencies in DG management pose challenges for families and healthcare providers.
- Standardization of screening and follow-up protocols for DG is needed to resolve current disparities and ensure optimal infant care.
Abstract:
It has been 50 years since the first newborn screening (NBS) test for galactosemia was conducted in Oregon, and almost 10 years since the last US state added galactosemia to their NBS panel. During that time an estimated >2,500 babies with classic galactosemia have been identified by NBS. Most of these infants were spared the trauma of acute disease by early diagnosis and intervention, and many are alive today because of NBS. Newborn screening for galactosemia is a success story, but not yet a story with a completely happy ending. NBS, follow-up testing, and intervention for galactosemia continue to present challenges that highlight gaps in our knowledge. Here we compare galactosemia screening and follow-up data from 39 NBS programs gathered from the states directly or from public sources. On some matters the programs agreed: for example, those providing relevant data all identify classic galactosemia in close to 1/50,000 newborns and recommend immediate and lifelong dietary restriction of galactose for those infants. On other matters the programs disagree. For example, Duarte galactosemia (DG) detection rates vary dramatically among states, largely reflecting differences in screening approach. For infants diagnosed with DG, >80% of the programs surveyed recommend complete or partial dietary galactose restriction for the first year of life, or give mixed recommendations; <20% recommend no intervention. This disparity presents an ongoing dilemma for families and healthcare providers that could and should be resolved.

Related Concept Videos
 01:27
Glucose Transporters
Facilitated diffusion-glucose transporters (GLUTs) are encoded by the solute-linked carrier (SLC) family 2, subfamily A gene family, or SLC2A. The 14 GLUT protein members are distributed into three classes:
 02:46
Genetic Screens
Forward genetic screens
Forward or “classical” genetic screens involve creating random mutations in an organism’s DNA using radiation, mutagens, or insertion of additional bases, which...
 01:20
Inborn Errors of Metabolism