Related Experiment Video
Updated: May 1, 2026
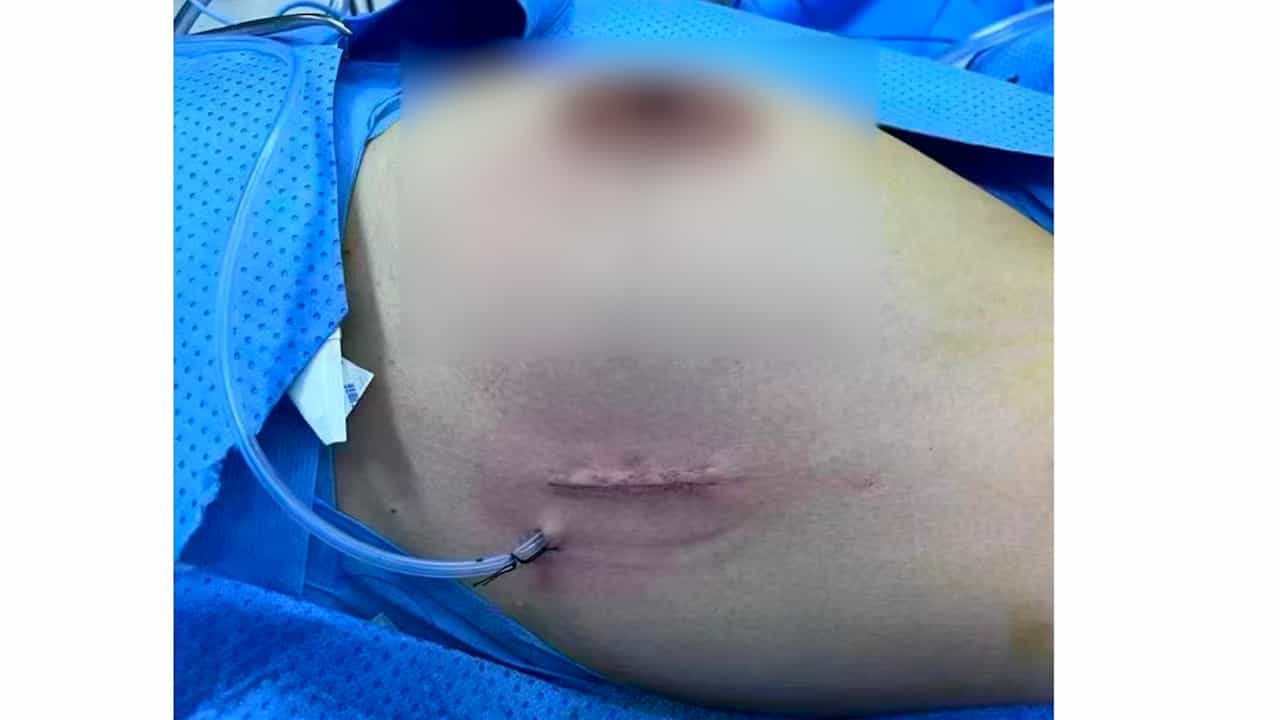

Single-port Non-liposuction Endoscopic Axillary Lymph Node Dissection in Breast Cancer Surgery
Published on: April 3, 2026
Addition of an iliac/obturator lymph node dissection does not improve nodal recurrence or survival in melanoma
Michael E Egger1, Russell E Brown2, Brent A Roach1
1University of Louisville, Hiram C Polk Jr MD Department of Surgery, Louisville, KY.

Background:
Controversy exists regarding the value and indications for inguinal dissection alone or in combination with an iliac/obturator lymph node dissection for melanoma.
Study Design:
We reviewed patients from a multicenter prospective clinical trial and a single center who underwent inguinal dissection alone or combined with an iliac/obturator dissection for cutaneous melanoma. Analyses were stratified and compared by microscopic or macroscopic (palpable or detected by imaging) disease.
Results:
The study was composed of 134 patients with a median follow-up of 39 months. Indications for inguinal dissection were microscopic disease in 94 (70%) patients and macroscopic nodal disease in 40 (30%) patients. An iliac/obturator dissection yielded tumor-positive pelvic nodes in 25% vs 55% in the microscopic vs macroscopic groups, respectively (p = 0.10). No risk factors for positive pelvic nodes were identified. For both microscopic and macroscopic disease, addition of an iliac/obturator dissection to an inguinal dissection did not significantly reduce the risk of pelvic nodal recurrence. Five-year overall survival rates for 4 groups were compared: microscopic disease, inguinal dissection alone (72%); microscopic disease, iliac/obturator dissection (68%); macroscopic disease, inguinal dissection alone (51%); and macroscopic disease, iliac/obturator dissection (44%) (p = 0.0163). On survival analysis, addition of an iliac/obturator dissection in either microscopic or macroscopic disease did not affect disease-free survival or regional lymph node recurrence-free survival.
Conclusions:
The addition of an iliac/obturator dissection to an inguinal dissection for both microscopic and macroscopic nodal disease did not significantly affect lymph node recurrence rates, disease-free survival, or overall survival.

