Related Experiment Video
Updated: May 1, 2026
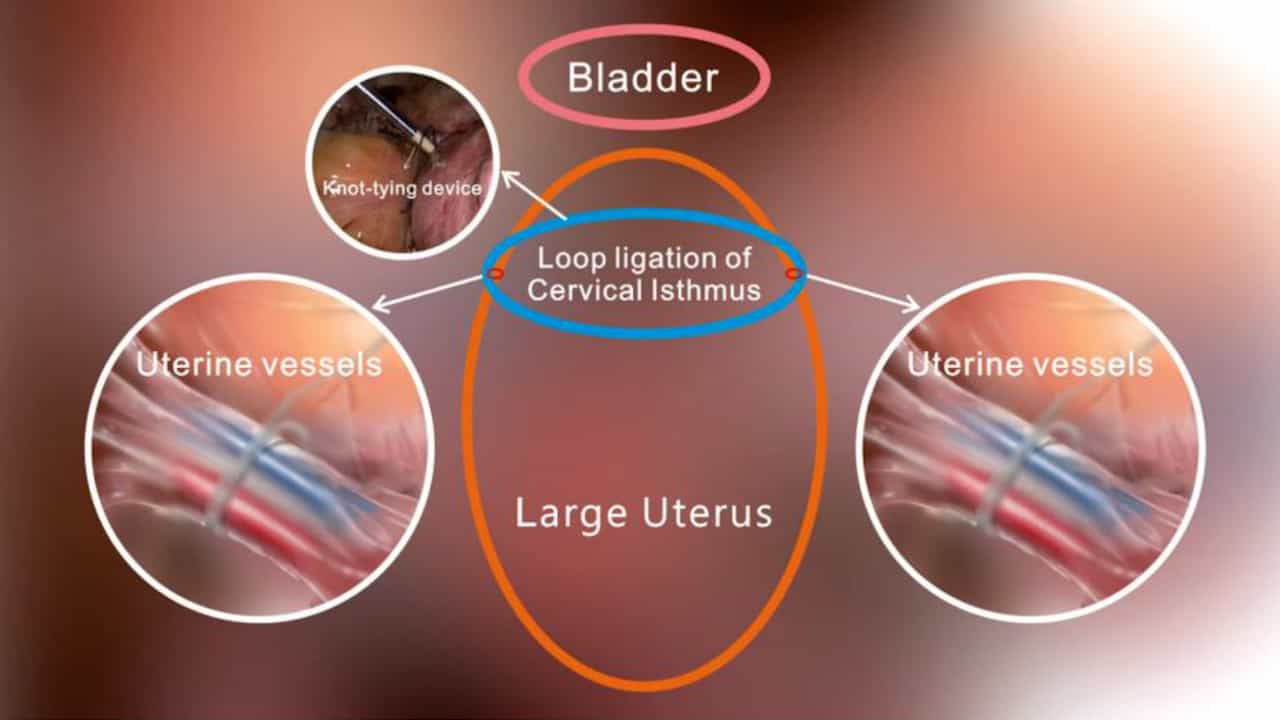

Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
A rare obstetric emergency: acute uterine torsion in a 32-week pregnancy
Karen Louise Moores1, Matthew G Wood, Richard P Foon
1Department of Maternity, Royal Shrewsbury Hospital, Shrewsbury, UK.

Uterine torsion is rare in pregnancy and the cause in most cases is unknown. It is associated with fetal compromise, with perinatal mortality reported to be around 12%. Our case describes an acute torsion, presenting in pregnancy with severe abdominal pain and vomiting with a viable 32-week gestation. Emergency caesarean section was performed and the 180° uterine torsion was diagnosed intraoperatively. Posterior hysterotomy was required for delivery prior to detorsion of the uterus. This report describes that prompt recognition and intraoperative vigilance can achieve a successful maternal and fetal outcome in this rare and difficult obstetric scenario.
Uterine torsion is rare in pregnancy and the cause in most cases is unknown. It is associated with fetal compromise, with perinatal mortality reported to be around 12%. Our case describes an acute torsion, presenting in pregnancy with severe abdominal pain and vomiting with a viable 32-week gestation. Emergency caesarean section was performed and the 180° uterine torsion was diagnosed intraoperatively. Posterior hysterotomy was required for delivery prior to detorsion of the uterus. This report describes that prompt recognition and intraoperative vigilance can achieve a successful maternal and fetal outcome in this rare and difficult obstetric scenario.


Related Concept Videos
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:19
Appendicitis
 01:07
Intestinal Obstruction II: Pathophysiology