Related Experiment Video
Updated: May 1, 2026
Full-Endoscopic Transforaminal Approach for Lumbar Discectomy
Published on: September 8, 2023
Surgical technique and effectiveness of microendoscopic discectomy for large uncontained lumbar disc herniations: a
Mohamed Hussein1, Ashraf Abdeldayem, Mahmoud M M Mattar
1Tennessee University, Memphis, USA, m_hussien9@yahoo.com.

Background:
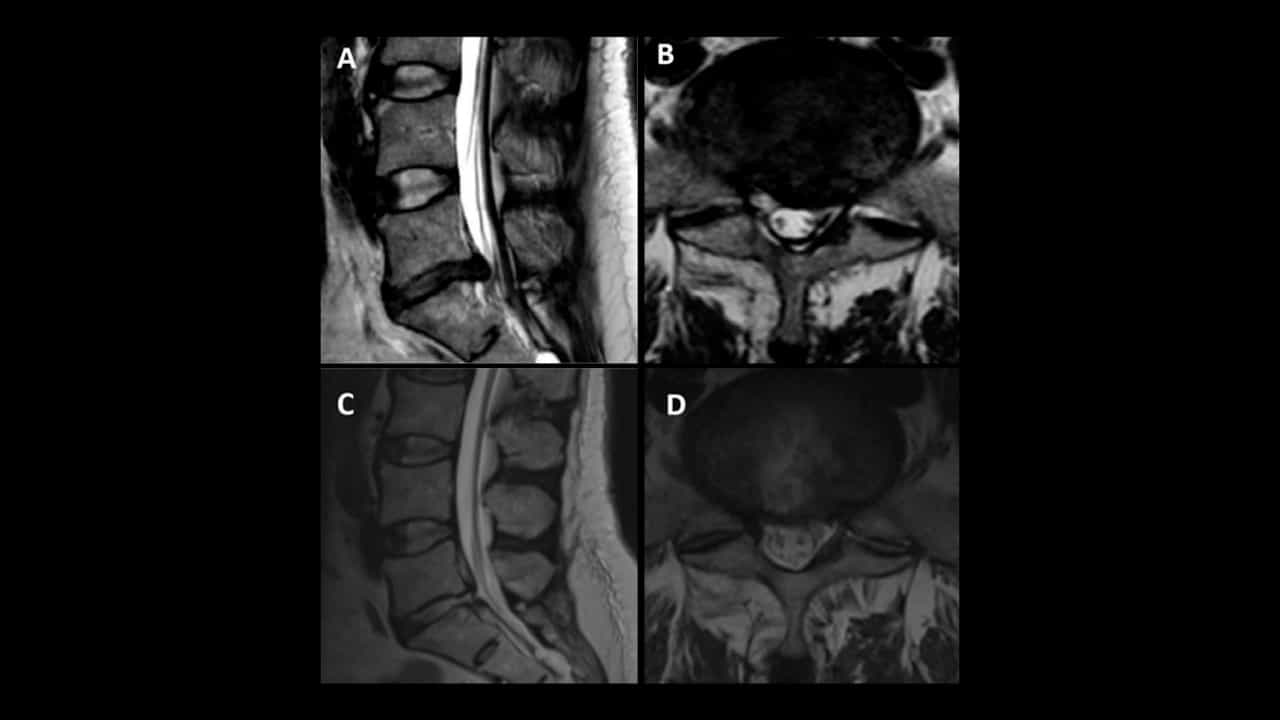
There is a long-held concept among spine surgeons that endoscopic lumbar discectomy procedures are reserved for small-contained disc herniation; 8-year follow-up has not been reported. The purpose of this study is to assess microendoscopic discectomy (MED) in patients with large uncontained lumbar disc herniation (the antero-posterior diameter of the extruded fragment is 6-12 mm or more on axial cuts of MRI) and report long-term outcome.
Methods:
One hundred eighty-five patients with MED or standard open discectomy underwent follow-up for 8 years. Primary (clinical) outcomes data included Numerical Rating Scale (NRS) for back and leg symptoms and Oswestry Disability Index (ODI) to quantify pain and disability, respectively. Secondary (objective) outcomes data included operative time, blood loss, postoperative analgesics, length of hospital stay, time to return to work, reoperation and complication rate, patient satisfaction index (PSI), and modified (MacNab) criteria.
Results:
At the end of the follow-up, the leg pain relief was statistically significant for both groups. NRS back pain, ODI, PSI and MacNab criteria showed significant deterioration for control group. Secondary outcomes data of MED group were significantly better than the control group.
Conclusions:
Large, uncontained, lumbar disc herniations can be sufficiently removed using MED which is an effective alternative to open discectomy procedures with remarkable long-term outcome. Although the neurological outcome of the two procedures is the same, the morbidity of MED is significantly less than open discectomy. Maximum benefit can be gained if we adhere to strict selection criteria. The optimum indication is single- or multi-level radiculopathy secondary to a single-level, large, uncontained, lumbar disc herniation.
Insights
Microendoscopic discectomy (MED) effectively treats large, uncontained lumbar disc herniations, offering a less invasive alternative to open surgery. This 8-year follow-up shows MED provides comparable neurological outcomes with significantly reduced morbidity.
Area of Science:
- Neurosurgery
- Spinal Surgery
- Minimally Invasive Procedures
Background:
- Traditional view: endoscopic discectomy for small herniations.
- Limited long-term data for large herniations.
Purpose of the Study:
- Evaluate microendoscopic discectomy (MED) for large uncontained lumbar disc herniations.
- Assess 8-year clinical and objective outcomes.
Main Methods:
- 185 patients undergoing MED or open discectomy.
- 8-year follow-up assessing pain (NRS), disability (ODI), and patient satisfaction (PSI).
- Objective outcomes: operative time, blood loss, hospital stay, reoperation rates.
Main Results:
- Significant leg pain relief in both MED and open discectomy groups.
- MED group showed better secondary outcomes and less deterioration in back pain and disability.
- MED demonstrated significantly lower morbidity compared to open discectomy.
Conclusions:
- MED is a viable alternative for large uncontained lumbar disc herniations.
- Neurological outcomes are similar, but MED has lower morbidity.
- Strict patient selection is crucial for optimal results.