Related Experiment Video
Updated: May 1, 2026
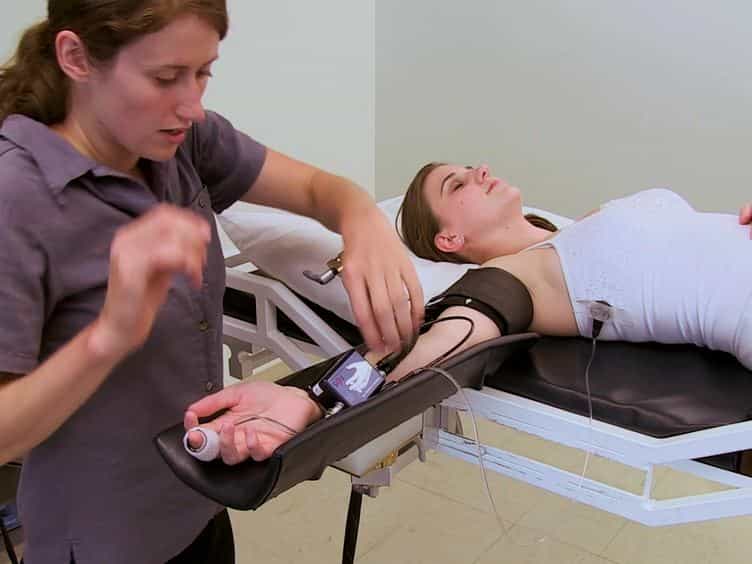

Tilt Testing with Combined Lower Body Negative Pressure: a "Gold Standard" for Measuring Orthostatic Tolerance
Published on: March 21, 2013
[Treatment of syncope]
1Klinik für Kardiologie, Intensivmedizin und Allgemeine Innere Medizin, Vivantes Klinikum Am Urban, Dieffenbachstr. 1, 10967, Berlin, Deutschland, dietrich.andresen@vivantes.de.

Abstract:
The therapy of patients with syncope is oriented to the underlying pathophysiological mechanisms. Patients with reflex syncope require careful education regarding recognition of warning signs and the avoidance of trigger factors. Treatment with beta blockers is nowadays obsolete. Even other drugs have failed to show any benefit. Pacemaker therapy should only be considered if syncope attacks are frequent and if there is a correlation between symptoms and the electrocardiogram (ECG). Because autonomic failure in patients with orthostatic hypotension is often drug-induced, reduction of the dosage or the complete elimination is the treatment of choice in these patients. A higher than normal salt and fluid intake as well as general measures to avoid delayed venous backflow, e.g. elastic stockings, may also be helpful. A change in blood pressure medication can be decisive for therapy success, especially in elderly patients with arterial hypertension. Pacemaker and defibrillator therapy is the treatment of choice in patients with bradycardia and tachycardia arrhythmias, respectively. Although these measures are simple but effective, in individual cases it is still difficult to find clinical proof that arrhythmic disorders are the causal factors for the syncope. However, also in these patients cardiac pacing should be based on a symptom ECG correlation. The recently conducted market release of the injectable miniaturized ECG recorder will alleviate the diagnostic process. The limits of this approach, however, become obvious when there is the suspicion of a life-threatening rhythm disorder, because the only difference between syncope and sudden cardiac death is that in one case the patient wakes up again.
Insights
Effective syncope treatment targets underlying causes, not just symptoms. Identifying triggers and tailoring therapies like pacemaker or medication adjustments are key for managing fainting spells and preventing serious cardiac events.
Area of Science:
- Cardiology
- Internal Medicine
Context:
- Syncope management requires understanding diverse pathophysiological mechanisms.
- Current therapeutic strategies vary significantly based on syncope type.
Purpose:
- To outline current, evidence-based therapeutic approaches for different syncope etiologies.
- To emphasize the importance of mechanism-specific treatment and diagnostic correlation.
Summary:
- Reflex syncope management focuses on patient education and trigger avoidance; drug therapies are largely ineffective. Orthostatic hypotension treatment involves addressing drug-induced autonomic failure, increasing salt/fluid intake, and using compression. Cardiac pacing is indicated for frequent syncope with ECG correlation.
- Pacemaker and defibrillator therapy are crucial for bradycardia and tachycardia arrhythmias, respectively, though establishing causal links can be challenging. Miniaturized ECG recorders aid diagnosis, but suspicion of life-threatening arrhythmias necessitates careful evaluation.
Impact:
- Optimized syncope treatment strategies can improve patient outcomes and reduce healthcare burden.
- Accurate diagnosis and targeted therapy are essential to differentiate syncope from sudden cardiac death.
- Advances in diagnostic tools like implantable ECG recorders enhance the management of recurrent syncope.

Related Concept Videos
 01:25
Dysrhythmias VI: Management of Dysrhythmias
 01:25
Dysrhythmias VII: Nursing Management of Dysrhythmias
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:26
Pharmaceutical Poisoning: Treatment Strategies