Related Experiment Video
Updated: May 1, 2026


An In Vivo Estrogen Deficiency Mouse Model for Screening Exogenous Estrogen Treatments of Cardiovascular Dysfunction After Menopause
Published on: August 13, 2019
Progesterone for Symptomatic Perimenopause Treatment - Progesterone politics, physiology and potential for
1Endocrinology, University of British Columbia, and Vancouver Coastal Health Research. Institute, Vancouver, Canada V5Z 1M9. Scientific Director, Centre for Menstrual Cycle and Ovulation Research ( www.cemcor.ubc.ca ).

Abstract:
Perimenopause, women's normal midlife reproductive transition, is highly symptomatic for about 20% of women who are currently inaccurately counseled and inappropriately treated with oral contraceptives, menopausal hormone therapy or hysterectomy. About 80% of perimenopausal women experience vasomotor symptoms (VMS), 25% have menorrhagia, and about 10% experience mastalgia. The majority of women describe varying intensities of sleep, -coping or mood difficulties. Women are more symptomatic because common knowledge inaccurately says that estradiol (E2) levels are dropping/deficient. Evidence shows that with disturbed brain-ovary feedbacks, E2 levels average 26% higher and soar erratically - some women describe feeling pregnant! Also, ovulation and progesterone (P4) levels become insufficient or absent. The most symptomatic women have higher E2 and lower P4 levels. Because P4 and E2 complement/counterbalance each other's tissue effects, oral micronized P4 (OMP4 300 mg at -bedtime) is a physiological therapy for treatment-seeking, symptomatic perimenopausal women. Given cyclically (cycle d 14-27, or 14 on/off) in menstruating midlife women, OMP4 decreases cyclic VMS, improves sleep and premenstrual mastalgia. Menorrhagia is treated with ibuprofen 200mg/6h plus OMP4 cycle d 4-28. For insulin resistance, metformin plus cyclic or daily OMP4 decreases insulin resistance and weight gain. Non-responsive migraines need daily OMP4 plus usual therapies. VMS and insomnia in late perimenopause respond to daily OMP4. In summary, OMP4 is a physiology-based therapy that improves sleep, treats VMS, does not increase breast proliferation or cancer risk, increases bone formation and has beneficial cardiovascular effects. A controlled trial is testing OMP4 for perimenopausal VMS - more evidence-based data are needed.
Related Concept Videos
 01:28
Menopause
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH...
 01:20
Proliferative Phase
Notably, the stratum basale, the basal layer of the endometrium, including the basal parts of the uterine glands, remains unaffected by menstruation. Stem cells in this layer undergo mitosis, regenerating the stratum functionalis and thickening the...
 01:18
Menses Phase
When fertilization does not occur, the corpus luteum deteriorates, causing a significant drop in the levels of estrogen and progesterone in the body. This hormonal decrease triggers the release of prostaglandins, which cause the uterine...
 01:24
Disorders of the Female Reproductive System
 01:30
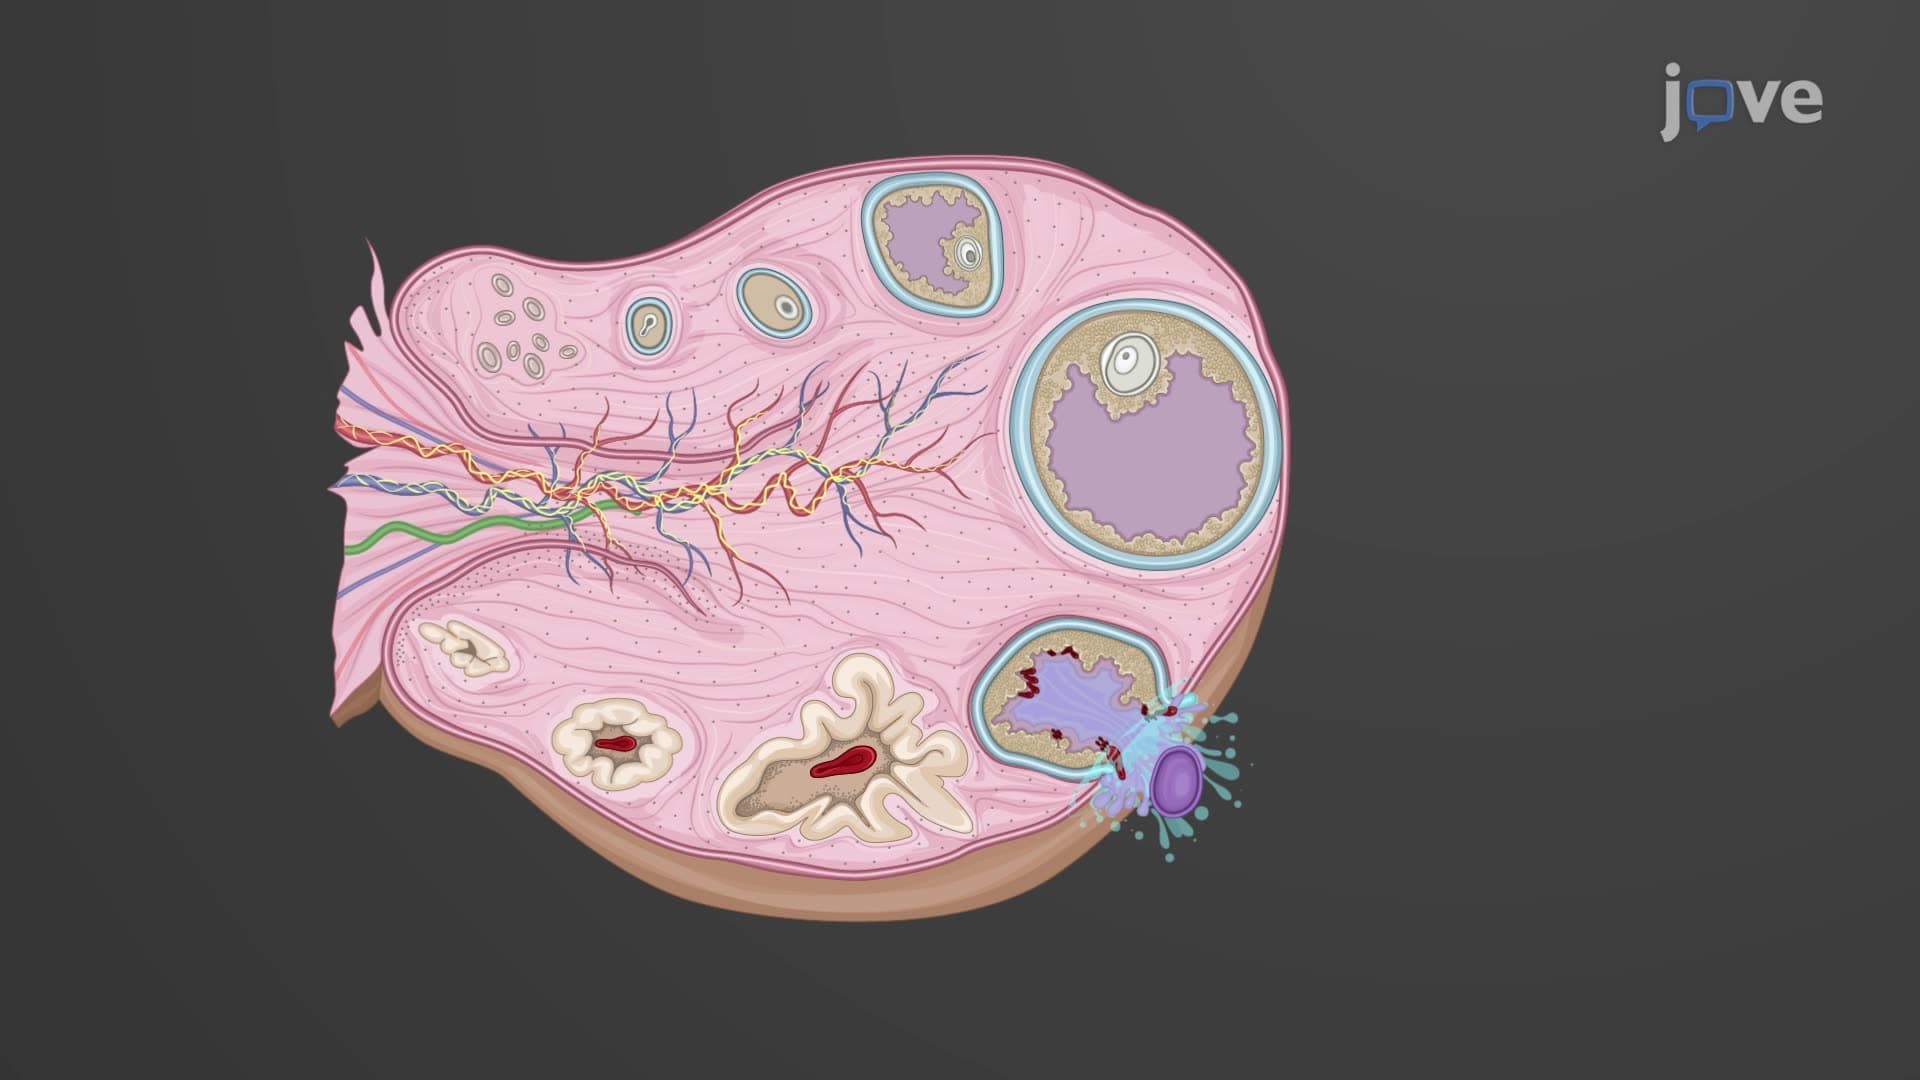
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...