Related Experiment Video For Pulmonary
Updated: Apr 30, 2026


Author Spotlight: Advancing Pathogen Detection and Disease Assessment in Real-Time Using M-ROSE
Published on: March 1, 2024
Pulmonary cryptococcosis: comparison of CT findings in immunocompetent and immunocompromised patients
Li-xuan Xie1, You-san Chen2, Shi-yuan Liu3
1Department of Nuclear Medicine, Wuhan General Hospital of CPLA Guangzhou Military Command, Wuhan, PR China xielixuan1110@163.com.

Background:
Computed tomography (CT) findings in patients with pulmonary cryptococcosis have been reported, however, many reports were limited by the small number of patients, and not taken into account the distinction between immunocompetent and immunocompromised patients.
Purpose:
To retrospectively evaluate thoracic CT findings in patients with pulmonary cryptococcosis whose immune status ranged from normal to severely compromised, and determine characteristic imaging features of pulmonary cryptococcosis between patients with different immune status.
Material And Methods:
CT scan findings of 29 immunocompetent and 43 immunocompromised patients with clinically proven pulmonary cryptococcosis were reviewed retrospectively. Different patterns of CT scan abnormalities between immunocompromised and immunocompetent patients, AIDS and non-AIDS immunocompromised patients were compared by Fisher's exact test.
Results:
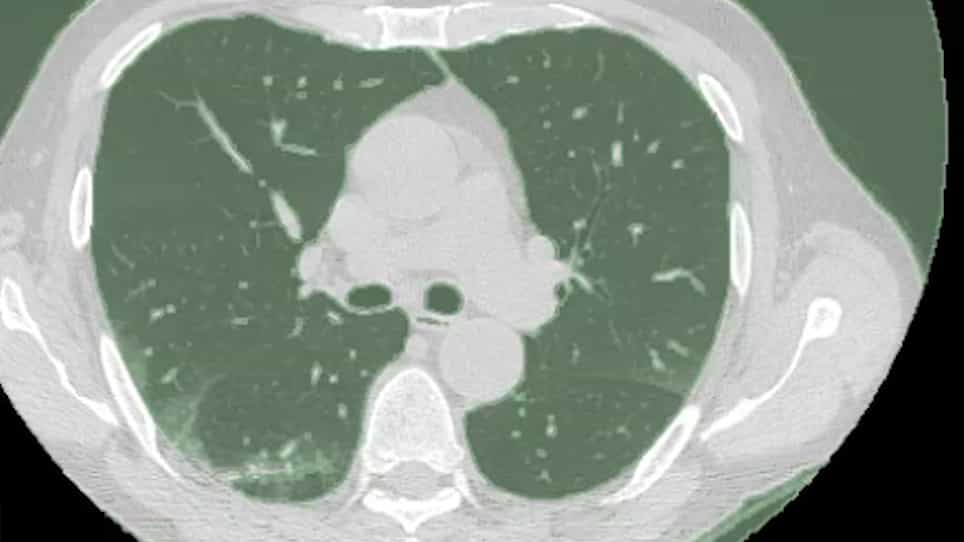
Pulmonary nodules/masses, either solitary or multiple, were the most common CT finding, present in 65 (90.3%) of the 72 patients; associated findings included CT halo sign (n = 24), cavitation (n = 23), and air bronchogram (n = 17). Areas of consolidation (n = 14), areas of GGO (n = 13), linear opacities (n = 11), lymphadenopathy (n = 5), and pleural effusion (n = 8) were uncommon. The parenchymal abnormalities were peripherally located in 47 (65.2%) of the cases. Cavitations within nodules/masses were more frequently present in immunocompromised patients than in immunocompetent patients (P = 0.009), and in AIDS patients than in non-AIDS immunocompromised patients (P = 0.002). Air bronchograms within nodules/masses were more frequent present in immunocompetent patients than in immunocompromised patients (P = 0.005). Nodules/masses with halo sign were less frequent in AIDS patients than those in non-AIDS immunocompromised patients (P = 0.027).
Conclusion:
Pulmonary cryptococcosis should be considered in the differential diagnosis of solitary or multiple pulmonary nodules. Cavitations within nodules/masses were more commonly seen in immunocompromised patients, especially AIDS patients, while air bronchograms were more commonly seen in immunocompetent patients.

Related Concept Videos
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...
 01:30
Pneumonia III: Complications and Assessment
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:27
Cytomegalovirus Disease