Related Experiment Video
Updated: Apr 30, 2026

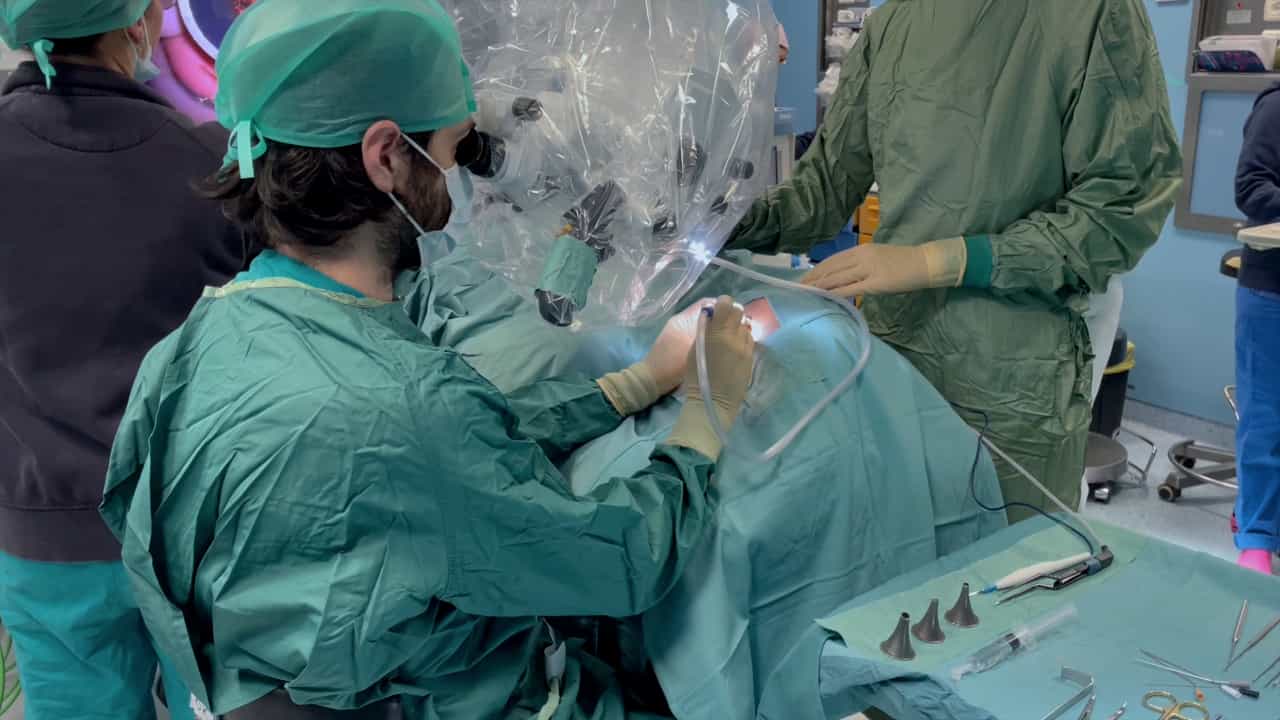
Role of Diffusion MRI Tractography in Endoscopic Endonasal Skull Base Surgery
Published on: July 5, 2021
Cerebellopontine angle facial schwannoma relapsing towards middle cranial fossa
Takafumi Nishizaki1, Norio Ikeda1, Shigeki Nakano1
1Department of Neurosurgery, Ube Industries Central Hospital, Nishikiwa, Ube, Yamaguchi, Japan.

Facial nerve schwannomas involving posterior and middle fossas are quite rare. Here, we report an unusual case of cerebellopontine angle facial schwannoma that involved the middle cranial fossa, two years after the first operation. A 53-year-old woman presented with a 3-year history of a progressive left side hearing loss and 6-month history of a left facial spasm and palsy. Magnetic resonance imaging (MRI) revealed 4.5 cm diameter of left cerebellopontine angle and small middle fossa tumor. The tumor was subtotally removed via a suboccipital retrosigmoid approach. The tumor relapsed towards middle cranial fossa within a two-year period. By subtemporal approach with zygomatic arch osteotomy, the tumor was subtotally removed except that in the petrous bone involving the facial nerve. In both surgical procedures, intraoperative monitoring identified the facial nerve, resulting in preserved facial function. The tumor in the present case arose from broad segment of facial nerve encompassing cerebellopontine angle, meatus, geniculate/labyrinthine and possibly great petrosal nerve, in view of variable symptoms. Preservation of anatomic continuity of the facial nerve should be attempted, and the staged operation via retrosigmoid and middle fossa approaches using intraoperative facial monitoring, may result in preservation of the facial nerve.
Facial nerve schwannomas involving posterior and middle fossas are quite rare. Here, we report an unusual case of cerebellopontine angle facial schwannoma that involved the middle cranial fossa, two years after the first operation. A 53-year-old woman presented with a 3-year history of a progressive left side hearing loss and 6-month history of a left facial spasm and palsy. Magnetic resonance imaging (MRI) revealed 4.5 cm diameter of left cerebellopontine angle and small middle fossa tumor. The tumor was subtotally removed via a suboccipital retrosigmoid approach. The tumor relapsed towards middle cranial fossa within a two-year period. By subtemporal approach with zygomatic arch osteotomy, the tumor was subtotally removed except that in the petrous bone involving the facial nerve. In both surgical procedures, intraoperative monitoring identified the facial nerve, resulting in preserved facial function. The tumor in the present case arose from broad segment of facial nerve encompassing cerebellopontine angle, meatus, geniculate/labyrinthine and possibly great petrosal nerve, in view of variable symptoms. Preservation of anatomic continuity of the facial nerve should be attempted, and the staged operation via retrosigmoid and middle fossa approaches using intraoperative facial monitoring, may result in preservation of the facial nerve.

Related Concept Videos
 01:19
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...
 01:14
Cranial Nerves: Types Part I
Olfactory Nerve (Cranial Nerve I)
The olfactory nerve, or cranial nerve I, is unique as it is purely sensory and dedicated to the sense of smell. This nerve originates in the olfactory epithelium of the...
 01:22
Cranial Nerves: Types Part II
Facial Nerve (Cranial Nerve VII)
Cranial nerve VII, or the facial nerve,...
 01:19
Cranial Nerves: Overview and Anatomy
 01:19
Multiple Sclerosis l: Introduction
 01:24
Prosopagnosia