Related Experiment Video
Updated: Apr 30, 2026


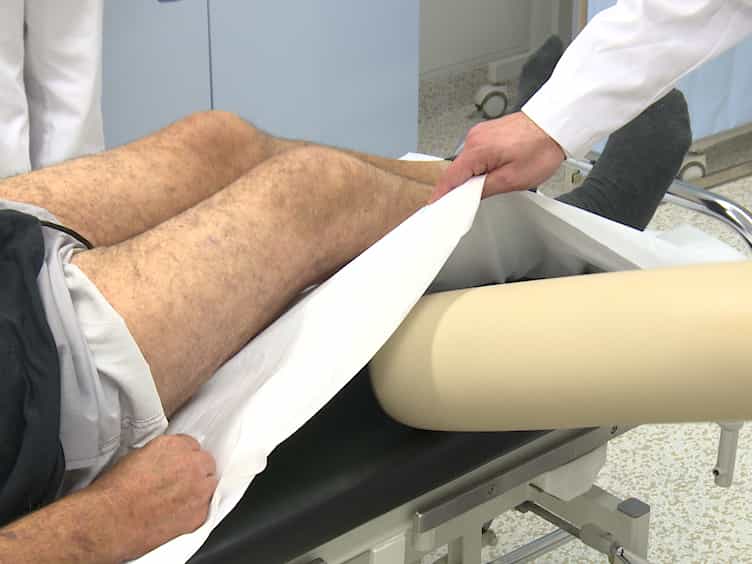
Knee Arthrocentesis in Adults
Published on: February 25, 2022
Septic arthritis in the era of immunosuppressive treatments

Immunosuppressants have been the mainstay of treatment for certain inflammatory joint conditions for many years. Developments in this field, namely biological treatments, have led to a change in the classical presentation of acute bone, joint and soft tissue infections. The normal findings of severe pain and tenderness on examination may be absent or simply mimic a typical exacerbation of the chronic joint condition. A minimally raised white cell count and elevated C-reactive protein in the absence of systemic signs of infection may be interpreted as further evidence for the diagnosis of an exacerbation of inflammatory arthritis. We present a unique case of recurrent polyarticular septic arthritis in a patient treated with immunosuppression for refractory rheumatoid arthritis. We hope this article will enable doctors to appreciate and recognise the changing face of septic arthritis in the modern era of immunosuppressant treatments.
Immunosuppressants have been the mainstay of treatment for certain inflammatory joint conditions for many years. Developments in this field, namely biological treatments, have led to a change in the classical presentation of acute bone, joint and soft tissue infections. The normal findings of severe pain and tenderness on examination may be absent or simply mimic a typical exacerbation of the chronic joint condition. A minimally raised white cell count and elevated C-reactive protein in the absence of systemic signs of infection may be interpreted as further evidence for the diagnosis of an exacerbation of inflammatory arthritis. We present a unique case of recurrent polyarticular septic arthritis in a patient treated with immunosuppression for refractory rheumatoid arthritis. We hope this article will enable doctors to appreciate and recognise the changing face of septic arthritis in the modern era of immunosuppressant treatments.
More Related Videos

Related Concept Videos
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:18
Endocarditis III: Medical Management
 01:25
Endocarditis I: Introduction
 01:27
Acute Pyelonephritis I: Introduction
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:26
Bacterial Meningitis II: Pathophysiology