Related Experiment Video
Updated: Apr 30, 2026
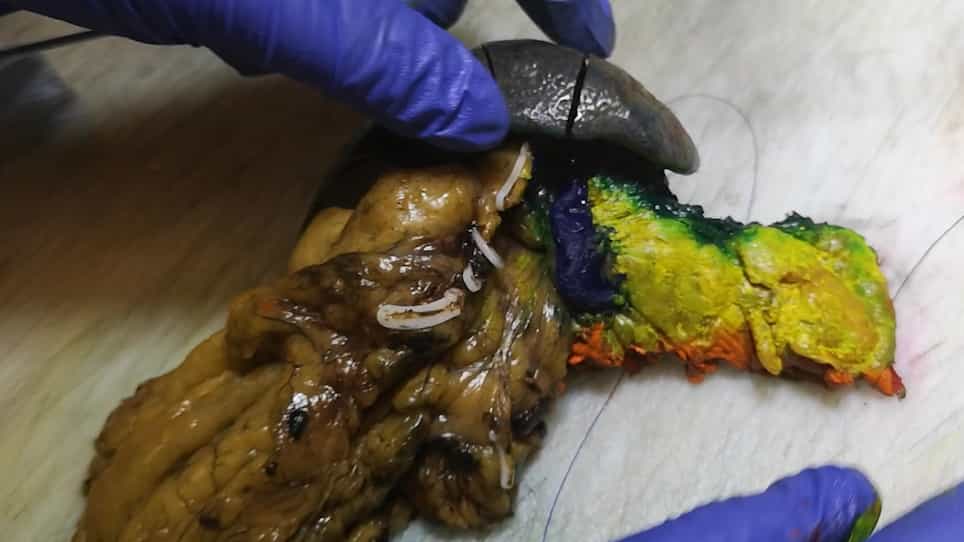
DIPLOMA Approach for Standardized Pathology Assessment of Distal Pancreatectomy Specimens
Published on: February 1, 2020
Surgical pathology report defects: a College of American Pathologists Q-Probes study of 73 institutions
Keith E Volmar1, Michael O Idowu, Jennifer L Hunt
1From the Department of Pathology, Rex Pathology Associates, Raleigh, North Carolina (Dr Volmar); the Department of Pathology, Virginia Commonwealth University, Richmond (Dr Idowu); the Department of Pathology, University of Arkansas, Little Rock (Dr Hunt); Statistics/Biostatistics, College of American Pathologists, Northfield, Illinois (Ms Souers); the Department of Pathology, Henry Ford Health System, Detroit, Michigan (Dr Meier); and the Department of Pathology, Mayo Clinic-Jacksonville, Jacksonville, Florida (Dr Nakhleh).

Context:
The rate of surgical pathology report defects is an indicator of quality and it affects clinician satisfaction.
Objective:
To establish benchmarks for defect rates and defect fractions through a large, multi-institutional prospective application of standard taxonomy.
Design:
Participants in a 2011 Q-Probes study of the College of American Pathologists prospectively reviewed all surgical pathology reports that underwent changes to correct defects and reported details regarding the defects.
Results:
Seventy-three institutions reported 1688 report defects discovered in 360,218 accessioned cases, for an aggregate defect rate of 4.7 per 1000 cases. Median institutional defect rate was 5.7 per 1000 (10th to 90th percentile range, 13.5-0.9). Defect rates were higher in institutions with a pathology training program (8.5 versus 5.0 per 1000, P = .01) and when a set percentage of cases were reviewed after sign-out (median, 6.7 versus 3.8 per 1000, P = .10). Defect types were as follows: 14.6% misinterpretations, 13.3% misidentifications, 13.7% specimen defects, and 58.4% other report defects. Overall, defects were most often detected by pathologists (47.4%), followed by clinicians (22.0%). Misinterpretations and specimen defects were most often detected by pathologists (73.5% and 82.7% respectively, P < .001), while misidentifications were most often discovered by clinicians (44.6%, P < .001). Misidentification rates were lower when all malignancies were reviewed by a second pathologist before sign-out (0.0 versus 0.6 per 1000, P < .001), and specimen defect rates were lower when intradepartmental review of difficult cases was conducted after sign-out (0.0 versus 0.4 per 1000, P = .02).
Conclusion:
This study provides benchmarking data on report defects and defect fractions using standardized taxonomy.


Related Concept Videos
 02:18
The Proteasome
In this pathway, the target proteins are first tagged with small proteins called ubiquitin. A series of enzymes carry out the ubiquitination of the target proteins - E1 (ubiquitin-activating enzyme), E2 (ubiquitin-conjugating enzyme), and E3...
 01:28
Urologic Endoscopic Procedure: Cystoscopic Examination