

Treatment of olecranon fractures with 2.4- and 2.7-mm plating techniques
David S Wellman1, Lionel E Lazaro, Rachel M Cymerman
1*Department of Orthopaedic Surgery, Hospital for Special Surgery, New York, NY; and †Department of Orthopaedic Surgery, New York Presbyterian Hospital, Weill Cornell Medical College, New York, NY.

Objectives:
To evaluate the outcomes of olecranon fractures treated with 2.4- and 2.7-mm plate constructs.
Design:
Retrospective Case Series.
Setting:
One-level 1 trauma center and 1 tertiary care hospital.
Patients:
Thirty-five consecutive patients meeting inclusion criteria.
Intervention:
A 2.7- or 2.4-mm reconstruction plate was placed on the dorsal ulnar cortex and contoured to allow passage of either a 2.7- or 3.5-mm intramedullary screw. In 9 patients, additional plates were required to control comminution. Available computed tomographic (CT) scans were evaluated for the presence of comminution.
Main Outcome Measurements:
Average Disabilities of the Arm, Shoulder, and Hand (DASH) and Mayo Elbow Performance Score (MEPS).
Results:
All fractures were united. Average extension deficit was 4.2 degrees, and average flexion angle was 137.4 degrees. Outcome scores were completed by 94% (33/35) of study patients. Average DASH score was 6.6, and average MEPS score was 94.5. Implants were removed in 18 patients. In the cohort of patients with CT scans, 6 of the 7 fractures thought to be simple on plain film analysis were found to have occult comminution on CT scan.
Conclusions:
Comminution should be considered in all olecranon fractures, even when plain films display simple patterns; although this did not affect treatment in this series of plated patients, it may be important if selecting tension band wiring. Fixation with 2.4- and 2.7-mm plates addresses comminution in olecranon fractures, avoiding the pitfalls of tension band wiring. In patients with completed outcome scores, 97% (32/33) reported their outcomes as good or excellent according to the MEPS.
Level Of Evidence:
Therapeutic Level IV. See Instructions for Authors for a complete description of levels of evidence.
More Related Videos
 04:41
Treatment with Locking Intramedullary Nailing for Intertrochanteric Fracture of the Femur Utilizing a New Awl with a Distal Positioner
Published on: June 6, 2025
 11:21
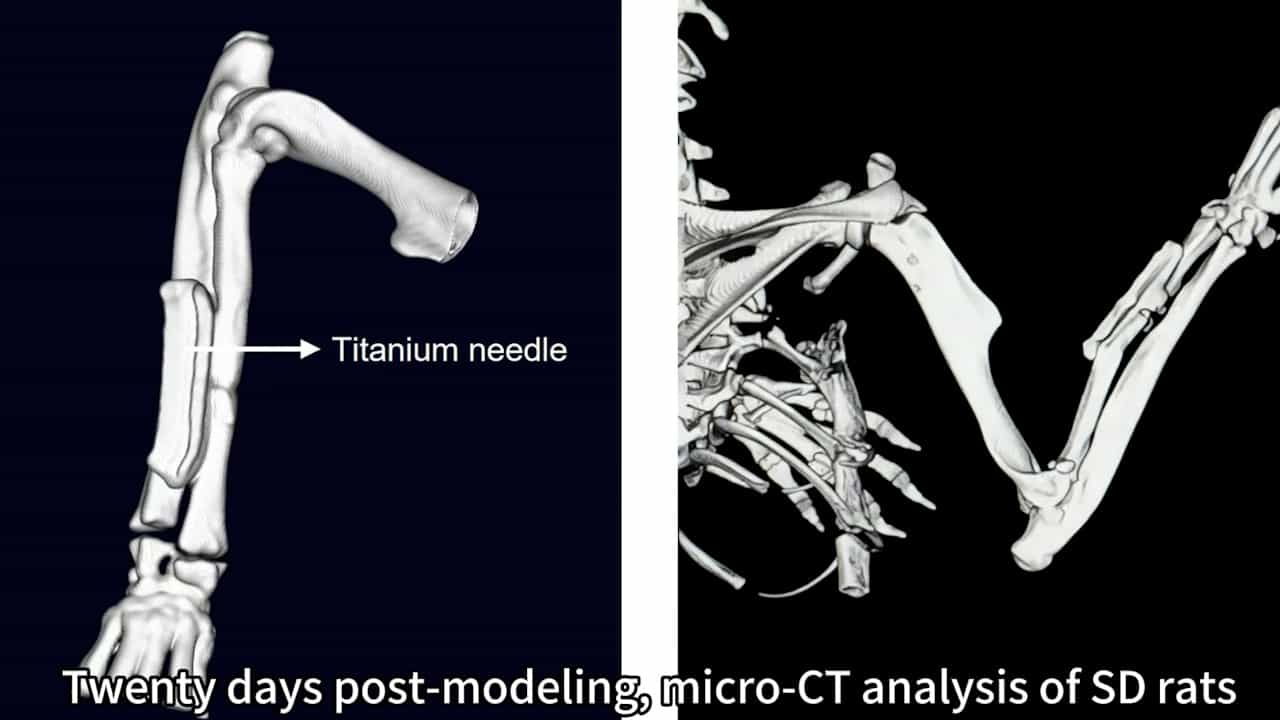
Development of a Novel Internal Fixation Model for Rat Radial Fractures: Fracture Healing Assessment and Dorsal Root Ganglion Isolation
Published on: March 13, 2026
Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History: