Related Experiment Video
Updated: Apr 29, 2026
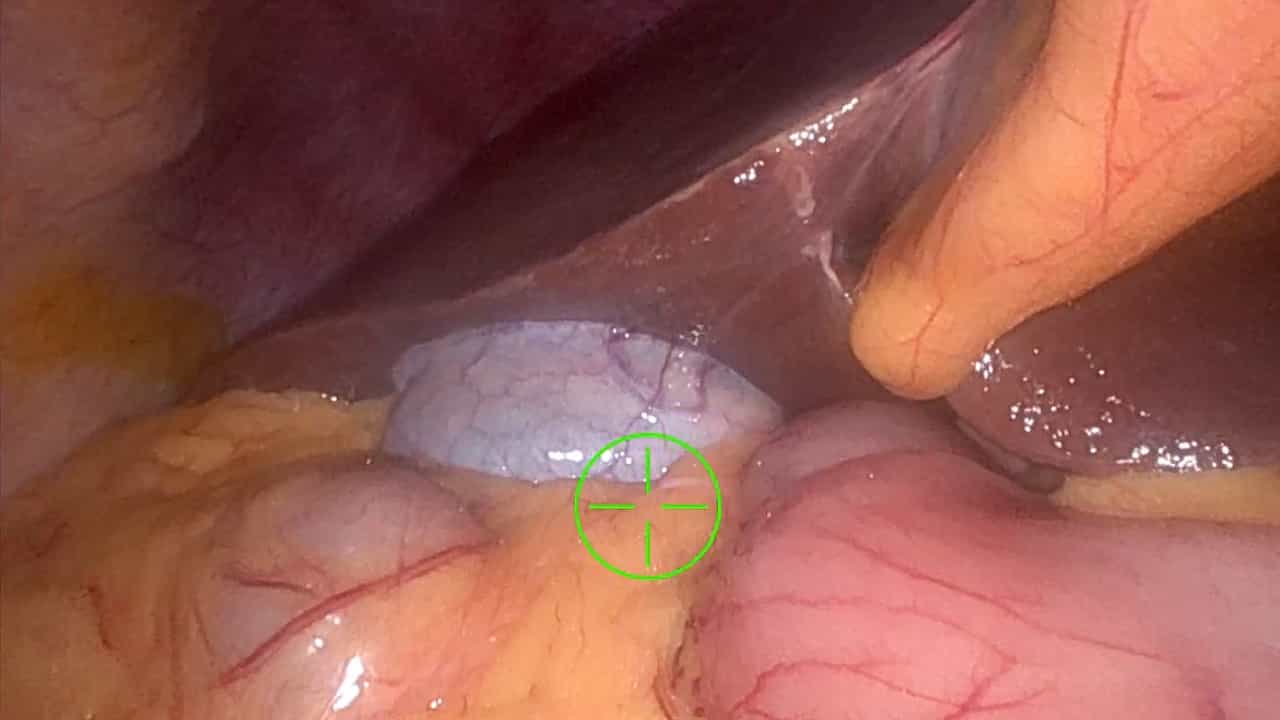

Application of Robot-assisted Pancreaticobiliary Junction Resection in Benign Duodenal Tumors
Published on: December 20, 2024
Biliopancreatic diversion requires multiple vitamin and micronutrient adjustments within 2 years of surgery
Philippe Topart1, Guillaume Becouarn1, Agnès Sallé2
1Société de Chirurgie Viscérale, Clinique de l'Anjou, 142, avenue de Lattre de Tassigny, 49000 Angers, France.

Background:
Malabsorptive bariatric procedures require multiple vitamin supplements, especially regarding fat-soluble vitamins. The exact amount required to maintain normal serum concentrations is still largely unknown. Based on the initial postoperative prescription, we assessed the number of adjustments and the amount of vitamins/micronutrients to normalize the biological markers 2 years after the biliopancreatic diversion with duodenal switch (BPD/DS).
Methods:
A total of 112 consecutive patients had a laparoscopic BPD/DS between February 2007 and November 2010 for a body mass index of 53.1±5.9 kg/m² at a private hospital. Complete blood checks with vitamin status were obtained at each of the 3-month interval visits during the 1(st) postoperative year as well as twice during the 2(nd) year.
Results:
Initially, all of the patients were prescribed daily 25,000 International units (IU) of vitamin A, 1000 mg of calcium, multivitamins, and 1900 IU of vitamin D3. Significant adjustments were necessary 3.6±1.1 times during this period. A total of 80% of the patients required added vitamin A, vitamin D, as well as calcium, zinc, and iron. After 2 years,≥20% of patients exhibited vitamin A and iron deficiency with low prealbumin or micropenic anemia. Seventy percent had vitamin D deficiency and 50% secondary hyperparathyroidism.
Conclusion:
The initial prescription was insufficient to cover the requirements after BPD/DS. At least 3000 mg of calcium with 7000 IU of vitamin D, 50,000 IU of vitamin A, 40 mg of zinc, and 200 mg of iron must be prescribed to start with. The trend toward a decrease in 25 OH vitamin D and hyperparathyroidism remains difficult to control although it can result from increased bone turnover during the early postoperative period.
Related Concept Videos
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD: