Related Experiment Video
Updated: Apr 29, 2026


Isolation of Human Islets from Partially Pancreatectomized Patients
Published on: July 30, 2011
Pancreatic endocrine and exocrine function in children following near-total pancreatectomy for diffuse congenital
Ved Bhushan Arya1, Senthil Senniappan1, Huseyin Demirbilek2
1Department of Paediatric Endocrinology, Great Ormond Street Hospital for Children NHS Foundation Trust, London, United Kingdom; Institute of Child Health, University College London, London, United Kingdom.

Context:
Congenital hyperinsulinism (CHI), the commonest cause of persistent hypoglycaemia, has two main histological subtypes: diffuse and focal. Diffuse CHI, if medically unresponsive, is managed with near-total pancreatectomy. Post-pancreatectomy, in addition to persistent hypoglycaemia, there is a very high risk of diabetes mellitus and pancreatic exocrine insufficiency.
Setting:
International referral centre for the management of CHI.
Patients:
Medically unresponsive diffuse CHI patients managed with near-total pancreatectomy between 1994 and 2012.
Intervention:
Near-total pancreatectomy.
Main Outcome Measures:
Persistent hypoglycaemia post near-total pancreatectomy, insulin-dependent diabetes mellitus, clinical and biochemical (faecal elastase 1) pancreatic exocrine insufficiency.
Results:
Of more than 300 patients with CHI managed during this time period, 45 children had medically unresponsive diffuse disease and were managed with near-total pancreatectomy. After near-total pancreatectomy, 60% of children had persistent hypoglycaemia requiring medical interventions. The incidence of insulin dependent diabetes mellitus was 96% at 11 years after surgery. Thirty-two patients (72%) had biochemical evidence of severe pancreatic exocrine insufficiency (Faecal elastase 1<100 µg/g). Clinical exocrine insufficiency was observed in 22 (49%) patients. No statistically significant difference in weight and height standard deviation score (SDS) was found between untreated subclinical pancreatic exocrine insufficiency patients and treated clinical pancreatic exocrine insufficiency patients.
Conclusions:
The outcome of diffuse CHI patients after near-total pancreatectomy is very unsatisfactory. The incidence of persistent hypoglycaemia and insulin-dependent diabetes mellitus is very high. The presence of clinical rather than biochemical pancreatic exocrine insufficiency should inform decisions about pancreatic enzyme supplementation.
Related Concept Videos
 01:16
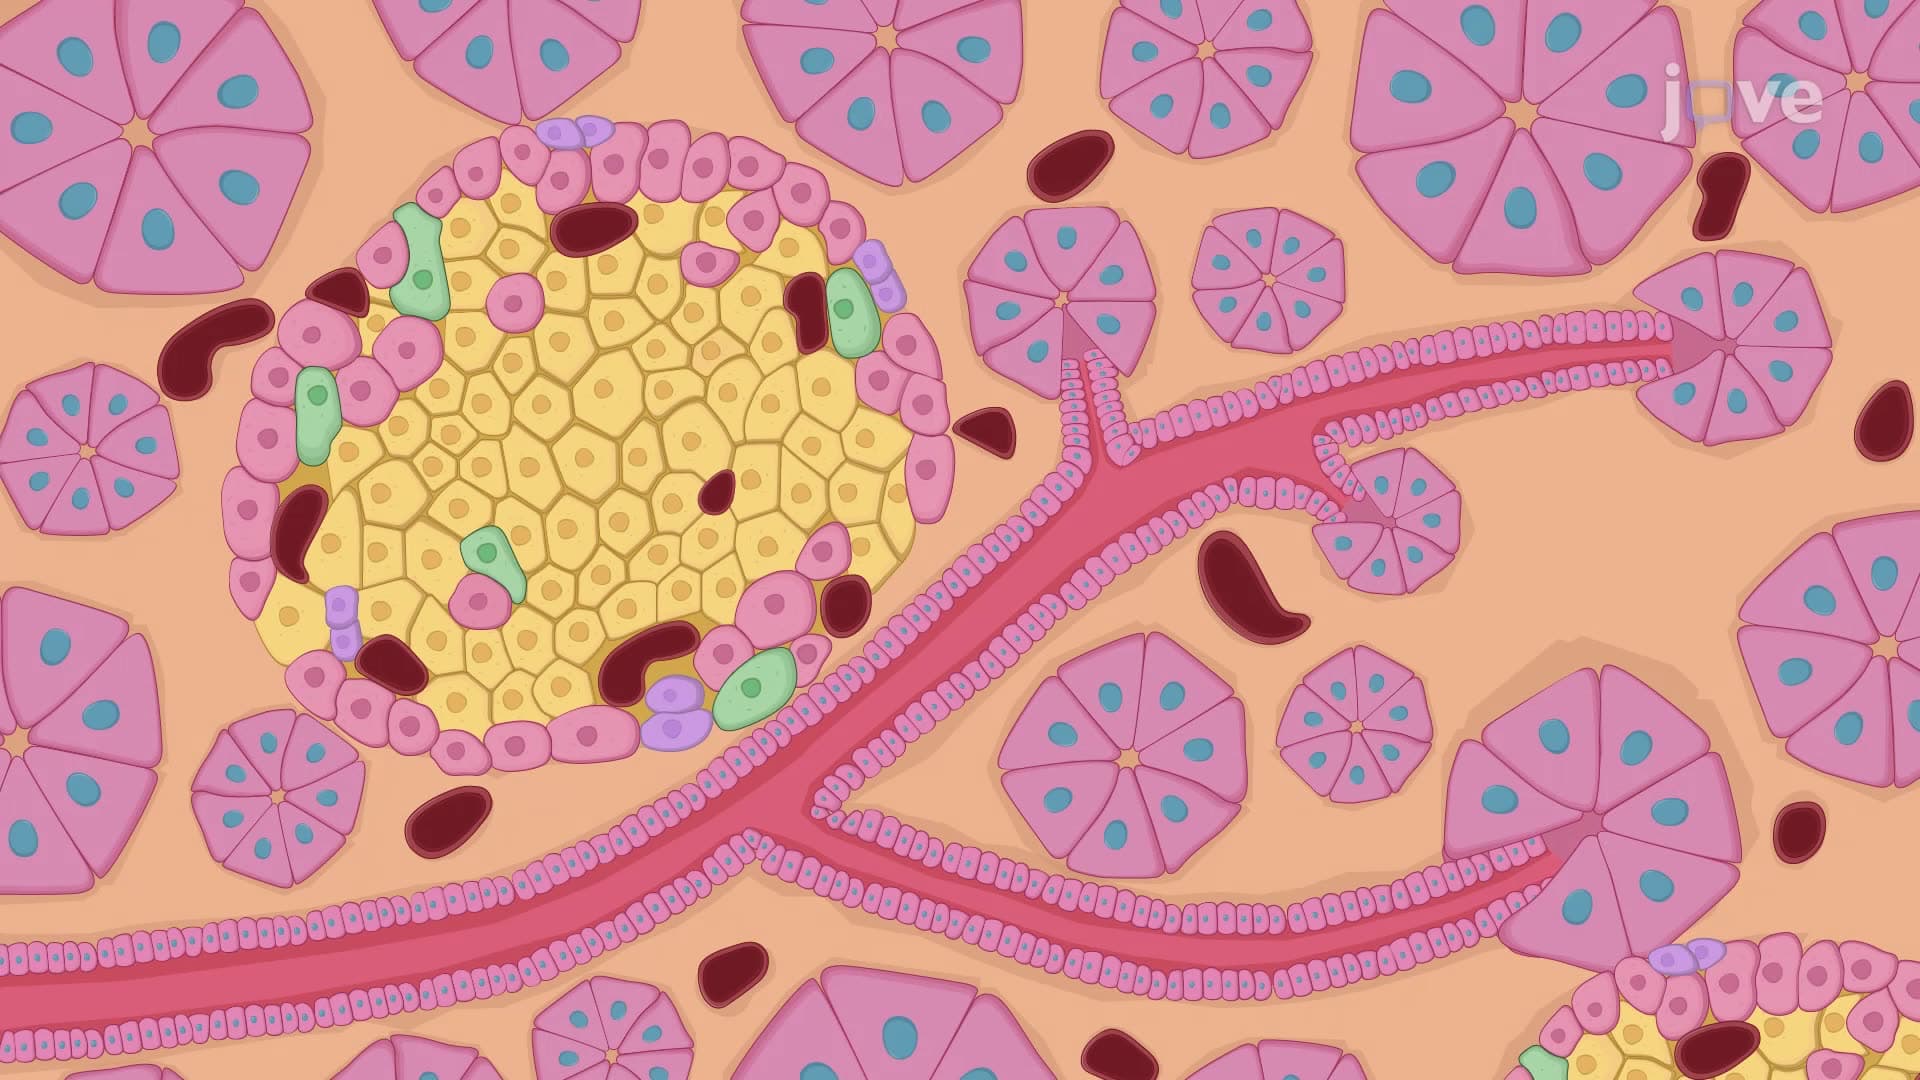
Cells and Secretions of the Pancreas
Exocrine function is carried out by acinar cells, organized into clusters known as acini. These cells contribute to digestion by releasing substantial quantities of enzyme-rich, alkaline digestive juices.
Concurrently, the dispersed clusters of endocrine cells throughout the...
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
Insulin and C-peptide are...
 01:19
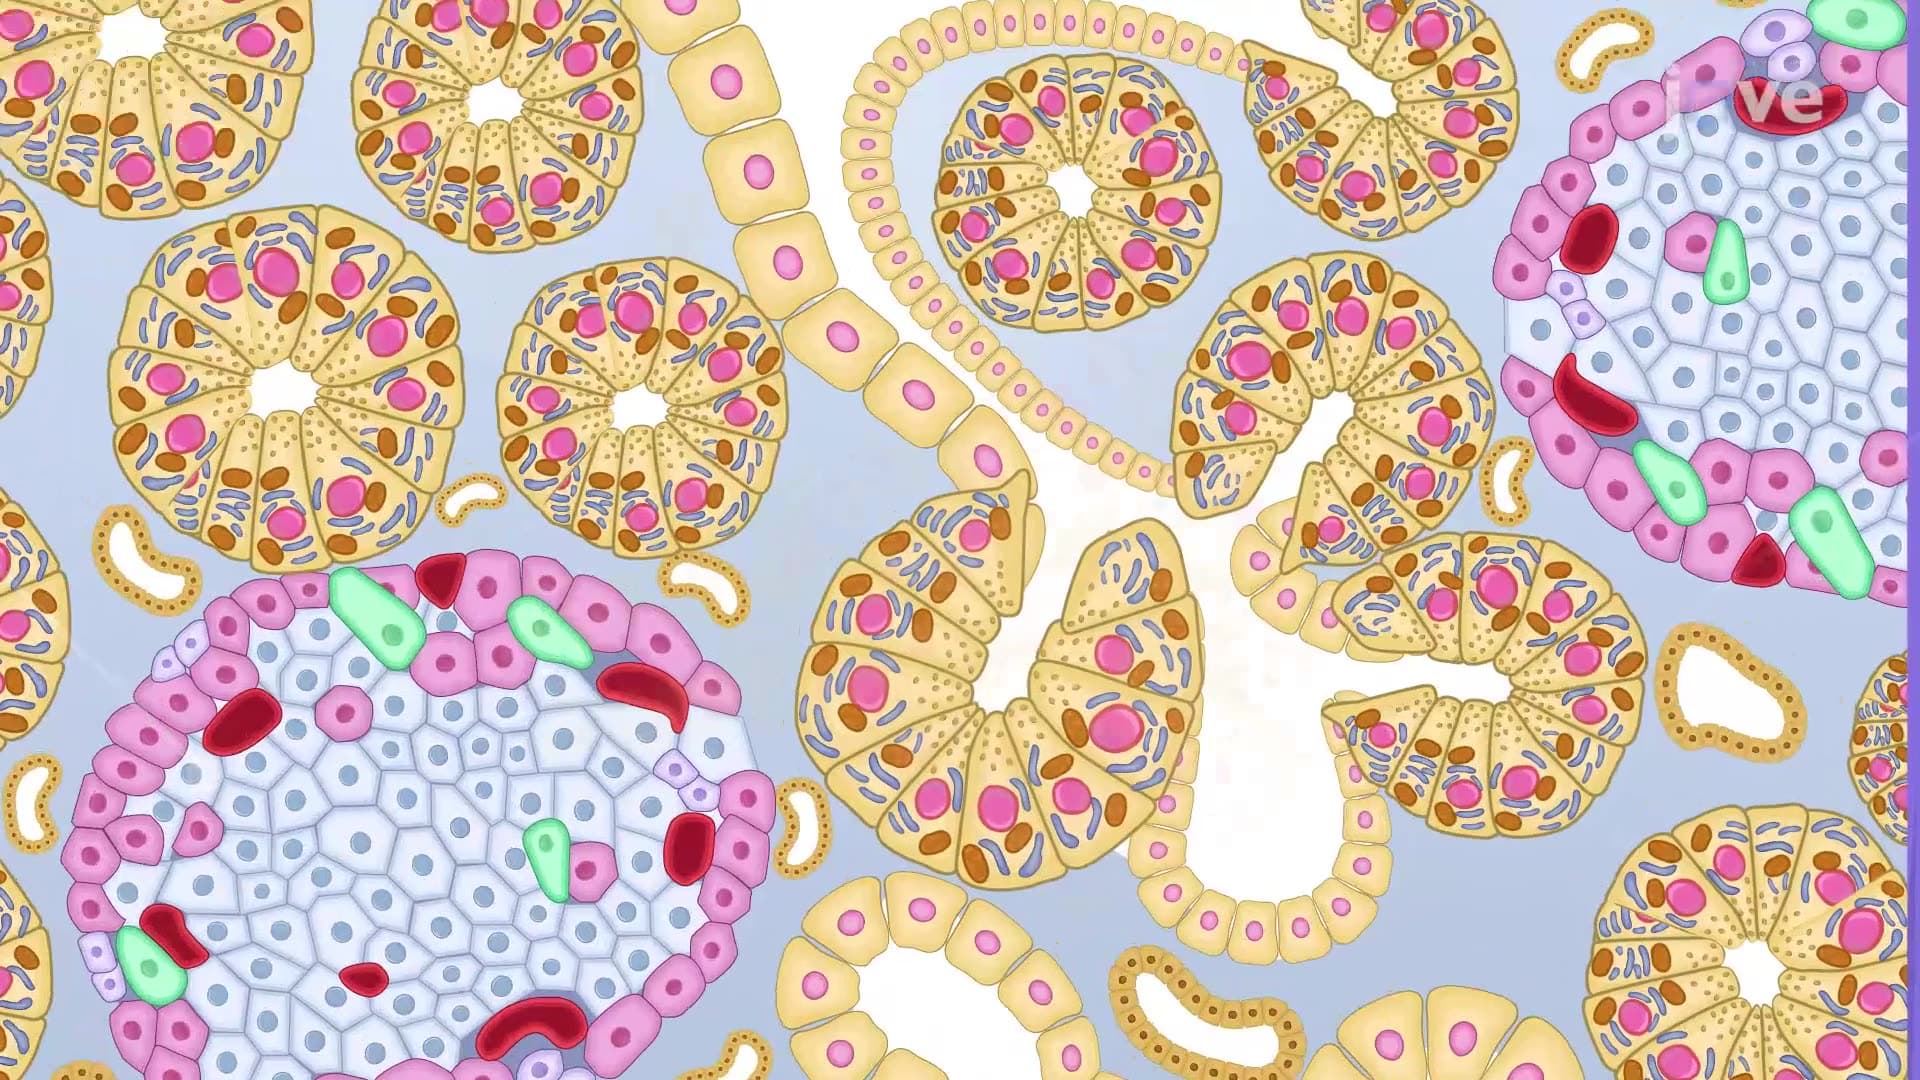
Pancreas
The broad head of the pancreas lies within the loop formed by the duodenum, while its slender body reaches towards the spleen. The tail of the pancreas is short...
 01:26
Type I Diabetes II: Pathophysiology
 01:05
Insulin Secretory Vesicles
 01:16
Hormones Regulating Blood Glucose
In addition to accelerating glucose uptake and utilization, insulin has...