Related Experiment Video
Updated: Apr 29, 2026


Isolation of Leukocytes from the Human Maternal-fetal Interface
Published on: May 21, 2015
Normal human pregnancy results in maternal immune activation in the periphery and at the uteroplacental interface
Andrea I Loewendorf1, Tina A Nguyen1, Maria N Yesayan1
1Division of Maternal-Fetal Medicine, Department of Obstetrics and Gynecology, David Geffen School of Medicine, University of California Los Angeles, Los Angeles, California, United States of America.

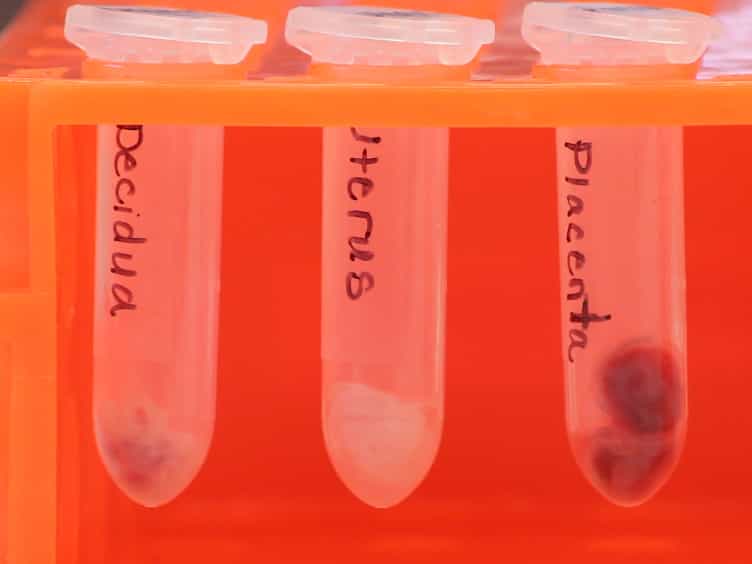
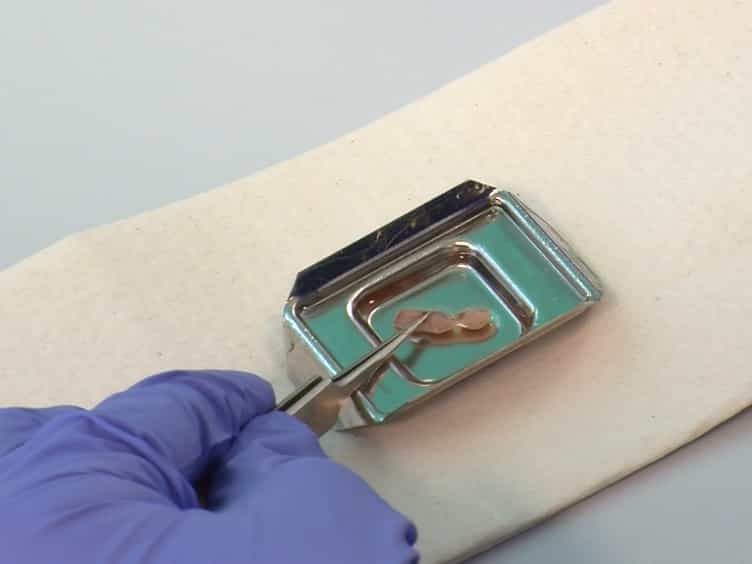
Pregnancy poses a unique challenge to the human immune system: the semi-allogeneic fetus must be protected from maternal immune attack while immunity towards pathogens is maintained. Breakdown in maternal-fetal tolerance can lead to pregnancy-specific diseases with potentially high degrees of morbidity and mortality for both the mother and her fetus. Various immune cell-types could mediate these functions, but a comprehensive evaluation of the peripheral and local maternal T cell and regulatory T cell compartments in normal human pregnancy is lacking. In this case-control study, we apply the Human Immunology Project Consortium proposed gating strategies to samples from healthy 3rd trimester human subjects compared with healthy non-pregnant controls. The proportions of HLA-DR+ and CD38+ effector- and effector memory CD8 T cells are significantly increased in the peripheral blood of pregnant women. Utilizing a novel technique that takes advantage of the standard protocol for intrauterine cleanup after cesarean section, we isolate lymphocytes resident at the uteroplacental interface (UPI). At the UPI, the CD4 and CD8 T cell compartments largely mirror the peripheral blood, except that the proportion of HLA-DR+ activated T regulatory cells is significantly increased in direct proportion to an observed increase in the number of activated CD8 T cells. We find that cryopreservation and delayed sample processing (>12 hours) decreases our ability to identify regulatory T cell subsets. Further, the Consortium proposed method for Treg identification underrepresents Resting and Cytokine Tregs compared with Activated Tregs, thus skewing the entire population. Better understanding of the changes in the immune system during pregnancy in the peripheral blood and at the uteroplacental interface are essential for progress in treatment of pregnancy diseases such as pre-eclampsia and recurrent miscarriage.
Pregnancy poses a unique challenge to the human immune system: the semi-allogeneic fetus must be protected from maternal immune attack while immunity towards pathogens is maintained. Breakdown in maternal-fetal tolerance can lead to pregnancy-specific diseases with potentially high degrees of morbidity and mortality for both the mother and her fetus. Various immune cell-types could mediate these functions, but a comprehensive evaluation of the peripheral and local maternal T cell and regulatory T cell compartments in normal human pregnancy is lacking. In this case-control study, we apply the Human Immunology Project Consortium proposed gating strategies to samples from healthy 3rd trimester human subjects compared with healthy non-pregnant controls. The proportions of HLA-DR+ and CD38+ effector- and effector memory CD8 T cells are significantly increased in the peripheral blood of pregnant women. Utilizing a novel technique that takes advantage of the standard protocol for intrauterine cleanup after cesarean section, we isolate lymphocytes resident at the uteroplacental interface (UPI). At the UPI, the CD4 and CD8 T cell compartments largely mirror the peripheral blood, except that the proportion of HLA-DR+ activated T regulatory cells is significantly increased in direct proportion to an observed increase in the number of activated CD8 T cells. We find that cryopreservation and delayed sample processing (>12 hours) decreases our ability to identify regulatory T cell subsets. Further, the Consortium proposed method for Treg identification underrepresents Resting and Cytokine Tregs compared with Activated Tregs, thus skewing the entire population. Better understanding of the changes in the immune system during pregnancy in the peripheral blood and at the uteroplacental interface are essential for progress in treatment of pregnancy diseases such as pre-eclampsia and recurrent miscarriage.
Related Concept Videos
 01:22
Development of Immunocompetence
The initial cells that migrate from the fetal thymus settle within the skin and epithelial tissues lining the mouth, digestive tract, and in females, the uterus and vagina. These cells, including skin-based dendritic cells, serve as antigen-presenting cells, playing a key role in T cell activation.
Subsequent T...
 01:15
Transcytosis of IgG
IgG molecules from a mother undergo transcytosis starting around 13 weeks of gestation. The amount of IgG transferred and entering the fetal blood circulation increases with...
 01:30
Development of Human Microbiota