Related Experiment Video
Updated: Apr 28, 2026
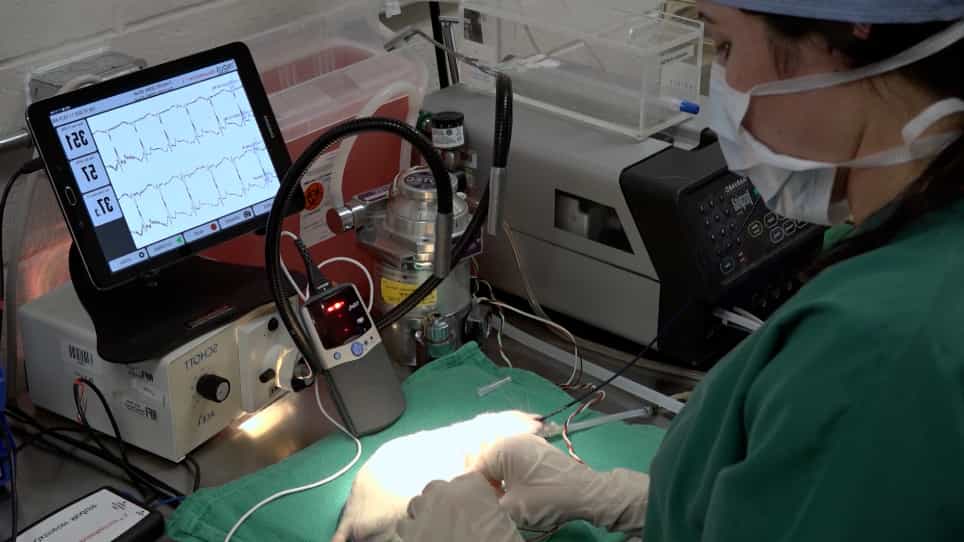

An Image Guided Transapical Mitral Valve Leaflet Puncture Model of Controlled Volume Overload from Mitral Regurgitation in the Rat
Published on: May 19, 2020
A case of ventricular septal defect and mitral insufficiency after blunt trauma
Ayumu Masuoka1, Naritaka Kimura2, Toshiyuki Katogi3
1Department of Pediatric Cardiac Surgery, Saitama Medical University International Medical Center, Saitama, Japan masuoka@saitama-med.ac.jp.

Insights
Blunt trauma caused severe heart injury in a child, including mitral regurgitation and septal defects. Surgical repair was successful, though reoperation was needed for a residual defect.
Area of Science:
- Pediatric Cardiology
- Cardiothoracic Surgery
- Pediatric Trauma
Background:
- Traumatic heart injury is rare in children.
- Blunt chest trauma can lead to complex cardiac damage.
Observation:
- A 2-year-old girl sustained acute mitral regurgitation, ventricular septal defect, and impending left ventricular free wall rupture after blunt trauma.
- Surgical intervention involved suturing the papillary muscle, patching the septal defect with pericardium, and closing a ventriculotomy with a Hemashield patch.
Findings:
- Initial surgical repair addressed the acute cardiac injuries.
- A residual defect due to pericardial patch dehiscence required reoperation 10 months post-initial surgery.
Implications:
- This case highlights the potential for severe cardiac sequelae from pediatric blunt trauma.
- Successful surgical management, even with reoperation, is crucial for pediatric traumatic heart injuries.
- Further research into optimal repair techniques for traumatic cardiac defects is warranted.
Abstract:
Few reports have described traumatic heart injury in children. We describe a case of acute mitral regurgitation associated with papillary muscle rupture, traumatic ventricular septal defect, and impending left ventricular free wall rupture due to blunt trauma in a 2-year-old girl. The papillary muscle was sutured to the left ventricular free wall. The septal defect and surrounding ruptured muscle were covered with a pericardial patch, and a Hemashield patch was used to close the ventriculotomy. A residual defect caused by dehiscence of the pericardial patch necessitated reoperation 10 months later. The patient is currently being observed on an outpatient basis.
More Related Videos


Related Concept Videos
 01:20
Mitral Regurgitation I: Introduction
 01:23
Mitral Regurgitation II: Clinical Features and Diagnostic Tests
 01:22
Mitral Stenosis I: Introduction
 01:28
Mitral Regurgitation IV: Nursing Management
 01:27
Mitral Valve Prolapse I: Introduction
 01:15
Aortic Regurgitation I: Introduction