Related Experiment Video
Updated: Apr 28, 2026
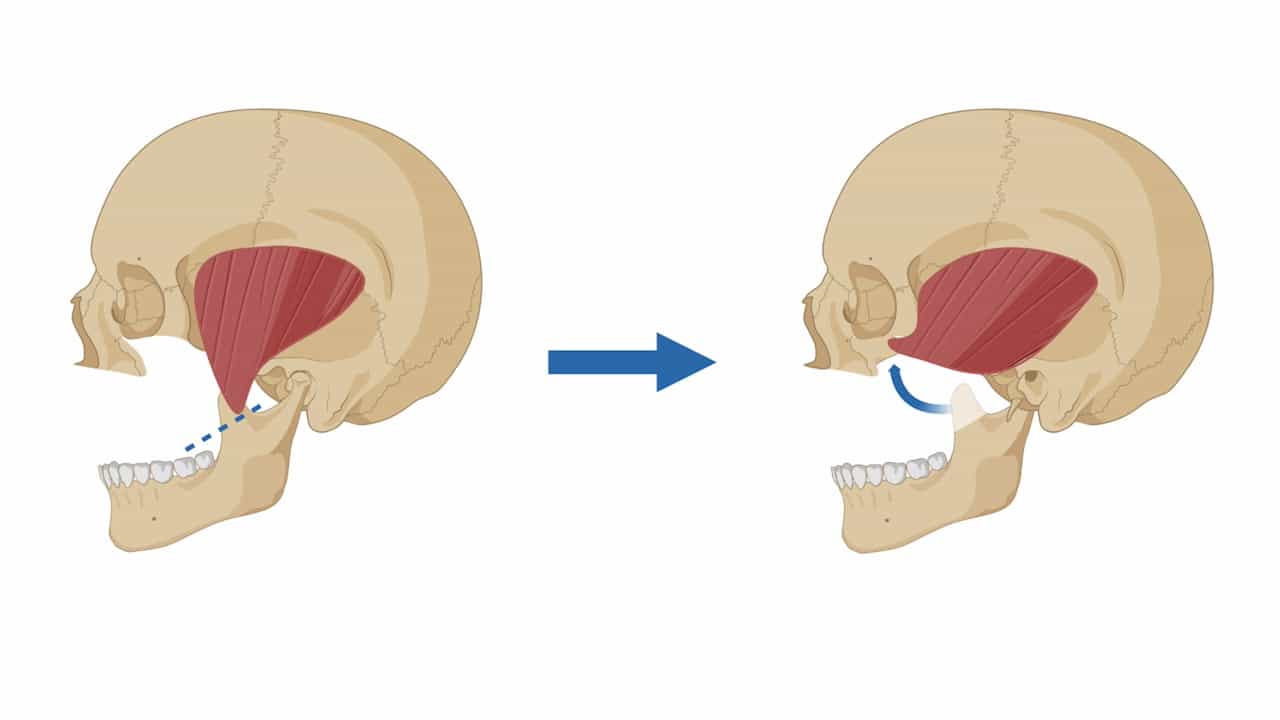
Coronoid-Temporalis Pedicled Flap for Orbital Floor Defect Reconstruction
Published on: December 5, 2025
Endocortical plating of the bandeau during fronto-orbital advancement provides safe and effective osseous
Tina M Sauerhammer1, Mitchel Seruya, Deniz Basci
1From the Division of Plastic and Reconstructive Surgery, Children's National Medical Center, Washington, DC.

Background:
Ectocortical resorbable plate fixation has become a standard method of fixation during fronto-orbital advancement (FOA) in young children. Plate hydrolysis occurs slowly and can cause visible prominences, sterile abscesses, and osseous depressions that can persist after complete resorption. Although endocortical placement avoids contour issues, the safety and effectiveness of this technique are undocumented.
Methods:
A review of our prospectively collected craniofacial database was performed. All patients undergoing FOA by a single craniofacial team at a single institution from 1997 to 2011 were examined. Inclusion criteria were as follows: (1) unicoronal, bicoronal, or metopic synostosis; (2) resorbable endocortical fixation of the bandeau; and (3) follow-up for 1 year or longer. Evaluation included patient demographic data, postoperative clinical course, and computed tomography imaging when available.
Results:
Seventy-three patients met the inclusion criteria. Fusion involved the unicoronal (n = 26), bicoronal (n = 19), and metopic (n = 28) sutures. Mean age at operation was 8.3 months (range, 2.7-35.5 mo), and follow-up was 4.5 years (range, 1.0-9.9 y). No endocortical or ectocortical sterile abscesses were documented in our series. Postoperative complications included hematoma (n = 2), infection (n = 2), wound breakdown (n = 3), cerebral contusion (n = 2), and cerebrospinal fluid leak (n = 1); none of these issues were related to endocortical absorbable fixation. Fifty-eight patients (80%) were categorized as Whitaker classification I/II; and 15 patients (20%), Whitaker classification III/IV. Postoperative computed tomography (mean follow-up, 4.6 y) was obtained in 34 patients (47%). All plates were completely resorbed, and there were no bone or soft tissue irregularities in the region where the plates were placed.
Conclusions:
Endocortical resorbable fixation is a safe and effective method of osseous stabilization during FOA for craniosynostosis in young children.

Related Concept Videos
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...
 01:27
Cranial Bones: Lateral View
The temporal bone forms the lower lateral side of the skull. The temporal bone is subdivided into several regions. The flattened upper portion is the squamous portion of the temporal bone. Below this area and projecting anteriorly is the zygomatic process of the temporal bone, which forms the posterior portion of the zygomatic arch. Posteriorly is the mastoid portion of the temporal bone. Projecting...