Related Experiment Video
Updated: Apr 28, 2026


A Method of Trigonometric Modelling of Seasonal Variation Demonstrated with Multiple Sclerosis Relapse Data
Published on: December 9, 2015
Temperature, hospital admissions and emergency room visits in Lhasa, Tibet: a time-series analysis
Li Bai1, Cirendunzhu2, Alistair Woodward3
1State Key Laboratory for Infectious Disease Prevention and Control, National Institute for Communicable Disease Control and Prevention, Chinese Center for Disease Control and Prevention, 155 Changbai Road, Changping District, Beijing 102206, PR China.

Background:
Tibet of China, with an average altitude of over 4000 m, has experienced noticeable changes in its climate over the last 50 years. The association between temperature and morbidity (most commonly represented by hospital admissions) has been documented mainly in developed countries. Little is known about patterns in China; nor have the health effects of temperature variations been closely studied in highland areas, worldwide.
Objective:
We investigated the temperature-morbidity association in Lhasa, the capital city of Tibet, using sex- and age-specific hospitalizations, excluding those due to external causes.
Methods:
A distributed lag non-linear model (DLNM) was applied to assess the nonlinear and delayed effects of temperature on morbidity (including total emergency room visits, total and cause-specific hospital admissions, sex- and age-specific non-external admissions).
Results:
High temperatures are associated with increases in morbidity, to a greater extent than low temperatures. Lag effects of high and low temperatures were cause-specific. The relative risks (RR) of high temperature for total emergency room visits and non-external hospitalizations were 1.162 (95% CI: 1.002-1.349) and 1.161 (95% CI: 1.007-1.339) respectively, for lag 0-14 days. The strongest cumulative effect of heat for lag 0-27 days was on admissions for infectious diseases (RR: 2.067, 95% CI: 1.026-4.027). Acute heat effects at lag 0 were related with increases of renal (RR: 1.478, 95% CI: 1.005-2.174) and respiratory diseases (RR: 1.119, 95% CI: 1.010-1.240), whereas immediate cold effects increased admission for digestive diseases (RR: 1.132, 95% CI: 1.002-1.282). Those ≥65 years of age and males were more vulnerable to high temperatures.
Conclusion:
We provide a first look at the temperature-morbidity relationship in Tibet. Exposure to both hot and cold temperatures resulted in increased admissions to hospital, but the immediate causes varied. We suggest that initiatives should be taken to reduce the adverse effects of temperature extremes in Tibet.

Related Concept Videos
 01:19
Assessing Body Temperature - Temporal Artery
Step 1: Perform hand hygiene and don a fresh pair of gloves to prevent cross-infection and ensure patient safety.
Step 2: Explain the procedure to the patient to establish trust. Clear communication establishes trust with the patient, ensures they understand what to expect, promotes cooperation, and enhances comfort during the procedure.
Step 3: Assess the patient's...
 00:54
Time-Series Graph
 01:26
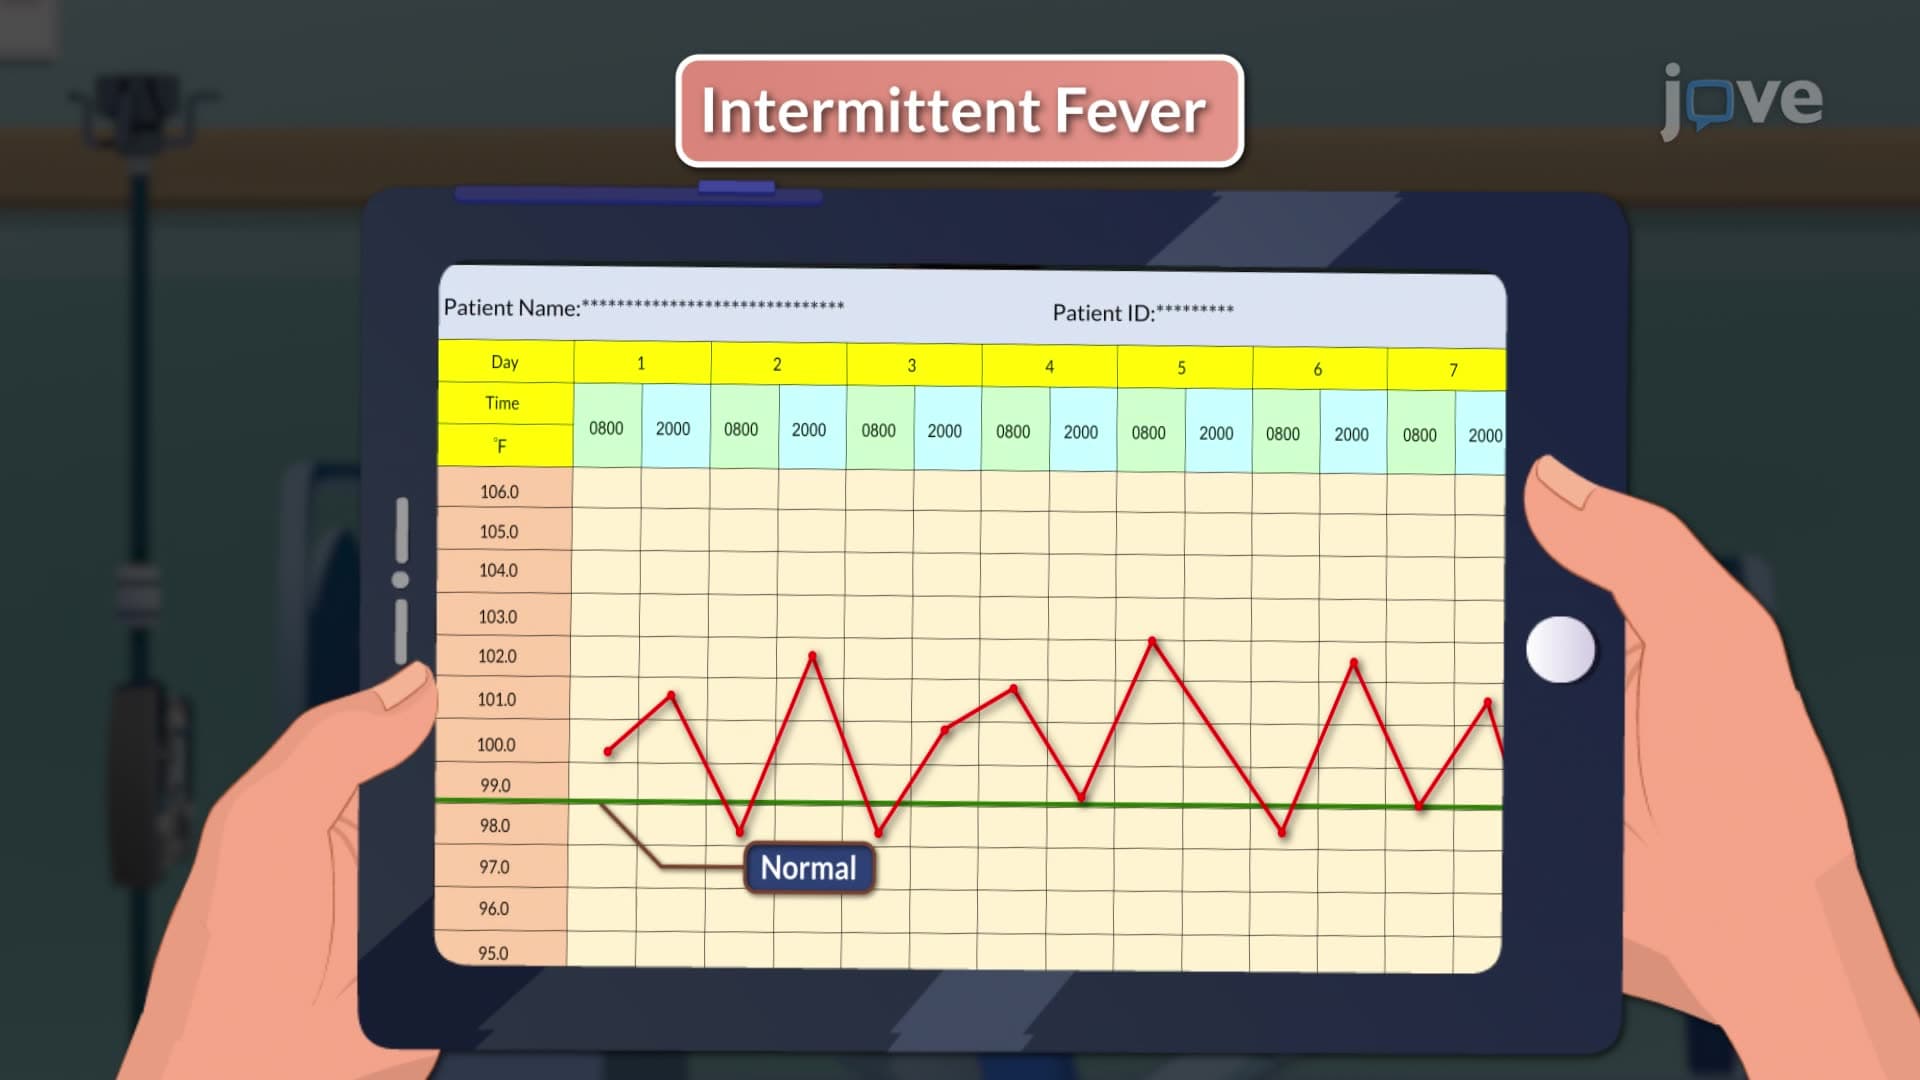
Patterns of Fever
 01:14
Temperature Measurement Sites
Oral: When assessing oral temperature, the thermometer tip should be placed under the tongue in the posterior sublingual pocket. It offers accurate readings and can be...
 01:25
Interpreting Run Charts
 01:29
Decreased Body Temperature