Related Experiment Video
Updated: Apr 28, 2026
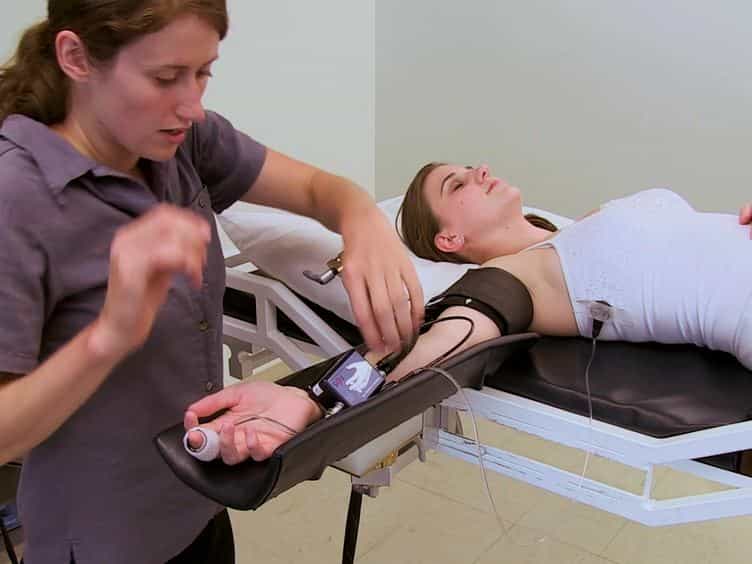

Tilt Testing with Combined Lower Body Negative Pressure: a "Gold Standard" for Measuring Orthostatic Tolerance
Published on: March 21, 2013
Physiologic variations in venous and arterial hemodynamics in response to postural changes at the thoracic outlet in
Huiting Chen1, Nichole Doornbos1, Kimberly Williams1
1Department of Surgery, Vascular Surgery Section, University of Michigan, Cardiovascular Center, Ann Arbor, MI.

Background:
Hemodynamic changes in vascular flow and waveforms measured across the thoracic outlet (TO) during positional changes may occur in normal individuals. The aim of this study was to establish the prevalence of significant arterial and venous hemodynamic variation in the limbs of normal volunteers during standardized upper extremity positional changes.
Methods:
Using Doppler ultrasound and photoplethysmography (PPG), we evaluated arterial and venous flow in 100 limbs of 50 normal volunteers in neutral position and in 5 different standardized arm positions, including 90° arm abduction (with head in neutral position, head turned ipsilaterally, and head turned contralaterally), arm extended above the head at 180°, and arm hyperextended at 200°.
Results:
There was great variability in the prevalence of abnormal venous and arterial flow changes depending on the arm position. Venous flow anomalies (loss of flow phasicity resulting in continuous, minimally continuous, or absent flow) were demonstrated in 60% of the limbs. The maneuver producing the greatest prevalence of venous flow abnormality was 90° arm abduction with contralateral head turn (34% of limbs), while arm hyperextension produced the least venous flow abnormalities (25% of limbs). In 13% of the limbs arterial flow abnormalities were found by PPG (absent tracings in 10% and dampened waveform in 5%), while 23% of the limbs showed increased arterial velocities (positional to neutral velocity ratio >2.0). The arm position producing the greatest prevalence of arterial flow anomaly was hyperextension (21% of limbs); while the arm positioning at 90° of abduction with the head in neutral position resulted in no arterial flow abnormalities.
Conclusions:
The prevalence of upper extremity venous and arterial hemodynamic changes varies substantially in different arm positions. Our data suggest that physiologic anomalies in venous flow across the TO during postural changes are very common, while the absence of finger PPG arterial tracings occur in a very small percentage of the population. Abnormal venous flow across the TO with postural changes should be considered a highly prevalent finding in the normal population, and therefore carries little value in the diagnosis of TO syndrome. On the other hand, absence of arterial waveforms measured at the fingers by PPG testing during positional changes occurs in a small percentage of the normal population, and may represent abnormal compression at the TO in patients with upper extremity symptomatology.
Related Concept Videos
 01:04
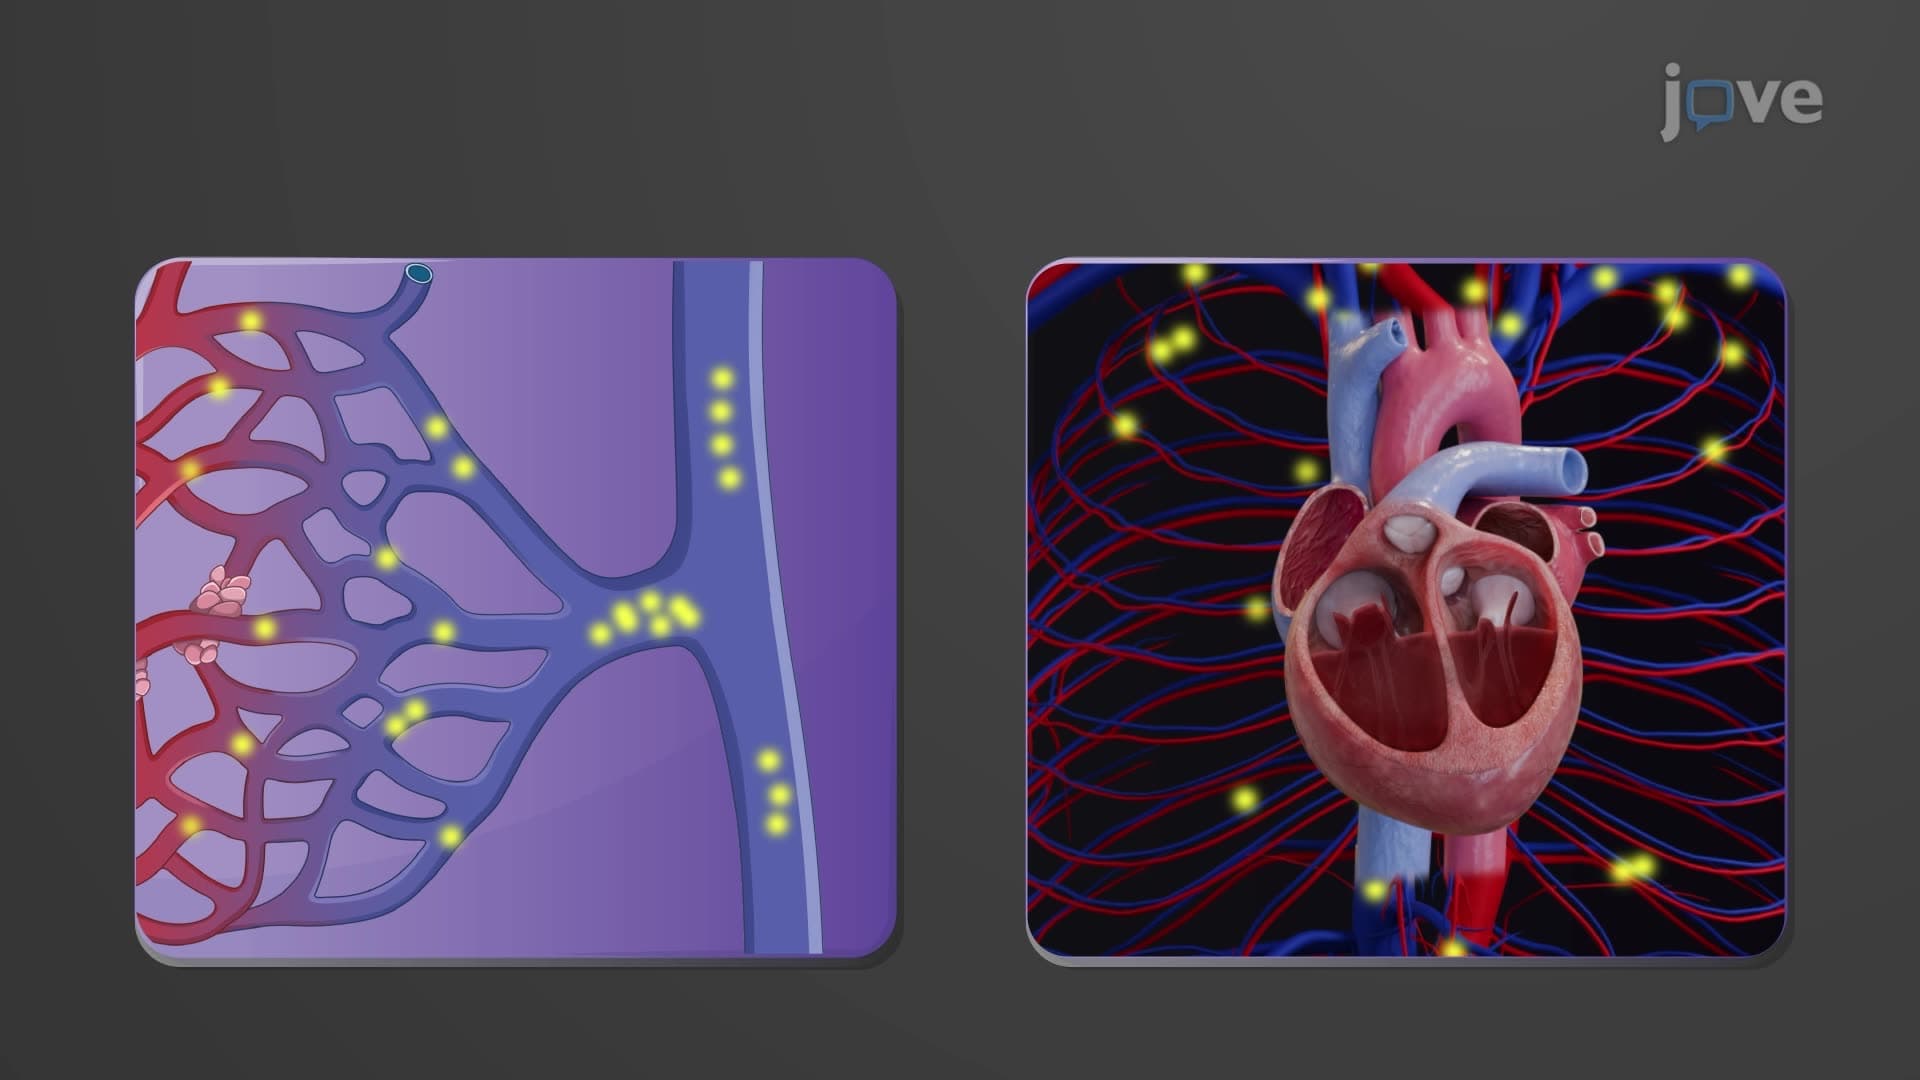
Venous Return
What is Venous Return?
Venous return refers to the rate at which blood flows back to the heart from the body's peripheral veins. It's an integral part of the circulatory system...
 01:10
Veins as Blood Reservoirs
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.
 01:21
Sites for measuring blood pressure
The Brachial Artery: Primary Site for Blood Pressure Measurement
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above...