Related Experiment Video
Updated: Apr 28, 2026
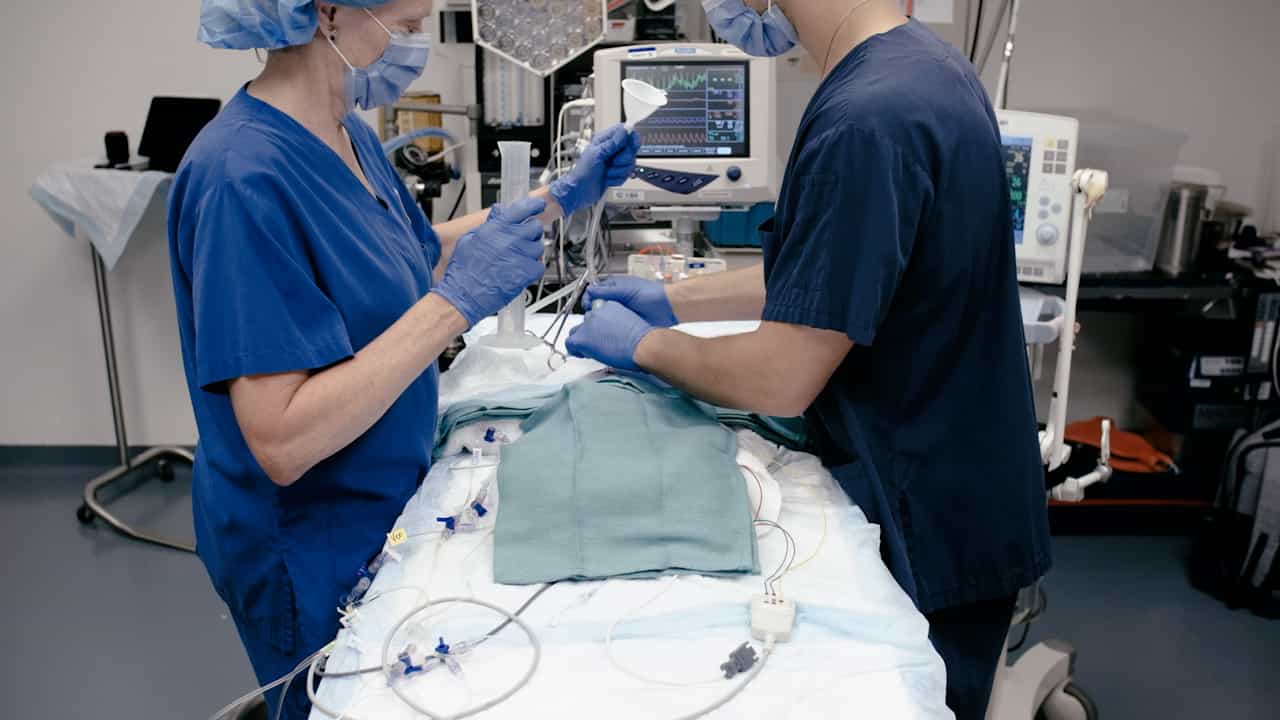
Development of a Neonatal Piglet Acute Lung Injury Model Recreating the Early Environment of Preterm Infant Lungs
Published on: October 31, 2025
Severe bronchopulmonary dysplasia is associated with higher fluid intake in very low-birth-weight infants: a
Mindy Ming-Huey Guo1, Ching-Hung Chung2, Feng-Shun Chen1
1Department of Pediatrics, Kaohsiung Chang Gung Memorial Hospital, Chang Gung University College of Medicine, Taiwan.

Insights
Very low-birth-weight infants receiving higher fluid intake in early life face increased risk of severe bronchopulmonary dysplasia. Higher fluid intake from days 2-4 is a significant risk factor for developing severe BPD.
Area of Science:
- Neonatal Medicine
- Pediatric Pulmonology
Background:
- Bronchopulmonary dysplasia (BPD) is a significant cause of morbidity in very low-birth-weight infants (VLBWI).
- Early life fluid management is crucial for VLBWI outcomes.
Purpose of the Study:
- To investigate the association between early fluid intake and the severity of bronchopulmonary dysplasia (BPD) in VLBWI.
Main Methods:
- Retrospective chart review of 75 VLBWI (gestational age < 32 weeks, birth weight < 1,500 g).
- Analysis of demographic, clinical data, maternal risk factors, and fluid intake in the first 4 days of life.
Main Results:
- Severe BPD was associated with lower gestational age, lower birth weight, surfactant use, patent ductus arteriosus (PDA), and pulmonary hemorrhage.
- Higher fluid intake from the 2nd to 4th days of life (346.44 ± 42.38 mL/kg) was significantly associated with severe BPD compared to lower intake (323.91 ± 27.62 mL/kg).
- A fluid intake cutoff of 345 mL/kg from days 2-4 was identified as a significant risk factor for severe BPD, even after logistic regression analysis.
Conclusions:
- Higher fluid intake in VLBWI during the 2nd to 4th days of life is a significant risk factor for developing severe BPD.
- This finding highlights the importance of careful fluid management in the early neonatal period for VLBWI.
Objective:
This study aims to investigate the association between fluid intake in the first 4 days of life and the subsequent severity of bronchopulmonary dysplasia (BPD) in very low-birth-weight infants (VLBWI).
Study Design:
A retrospective chart review of 75 infants with a gestational age of less than 32 weeks and a birth weight of < 1,500 g was performed. Demographic, clinical data, associated maternal risk factors, and amount of fluid received in the first 4 days of life were analyzed.
Results:
Severe BPD was associated with a lower gestational age (27.04 ± 2.073 wks vs. 28.70 ± 1.706 wks, p=0.001), lower birth weight (981.44 ± 244.54 vs. 1,199.63 ± 165.39 g, p < 0.001), use of surfactant (91.7 vs. 63%, p=0.002), patent ductus arteriousus (PDA) (70.8 vs. 37%, p=0.004), pulmonary hemorrhage (14.6 vs. 0%, p=0.045), and more fluids received from the 2nd to 4th days of life (346.44 ± 42.38 mL/kg vs. 323.91 ± 27.62 mL/kg, p=0.007). A cut off point of 345 mL/kg of fluids from the 2nd to 4th days of life was selected using receiver operating characteristic curve analysis, and remained a significant risk factor even after multiple logistic regression analysis.
Conclusion:
Our findings demonstrate that VLBWI who received higher fluid intake from the 2nd to 4th days of life are at an increased risk of developing severe BPD.
More Related Videos
 06:15
Protocol and Guidelines for Point-of-Care Lung Ultrasound in Diagnosing Neonatal Pulmonary Diseases Based on International Expert Consensus
Published on: March 6, 2019
 09:36
Halogenated Agent Delivery in Porcine Model of Acute Respiratory Distress Syndrome via an Intensive Care Unit Type Device
Published on: September 24, 2020
Related Concept Videos
 01:18
Pulmonary Edema II: Pathophysiology
 01:05
Breathing
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed....
 01:17
Pulmonary Cycle: Exhalation
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features