Related Experiment Video
Updated: Apr 28, 2026
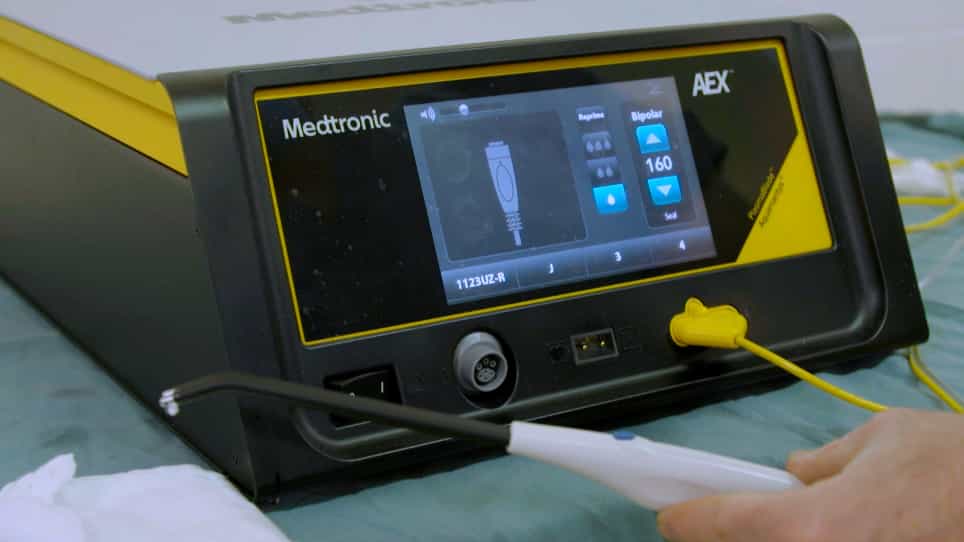

A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020
Early thromboembolic prophylaxis in patients with blunt solid abdominal organ injuries undergoing nonoperative
Bellal Joseph1, Viraj Pandit1, Caitlyn Harrison1
1Division of Trauma, Critical Care, Emergency Surgery, and Burns, Department of Surgery, The University of Arizona, 1501 N Campbell Avenue, Room 5511, Tucson, AZ 85724, USA.

Background:
The aim of this study was to compare the safety of early (≤48 hours), intermediate (48 to 72 hours), and late (≥72 hours) venous thromboembolism prophylaxis in patients with blunt abdominal solid organ injury managed nonoperatively.
Methods:
We performed a 6-year (2006 to 2011) retrospective review of all trauma patients with blunt abdominal solid organ injuries. Patients were matched using propensity score matching in a 2:1:1 (early:intermediate:late) for age, gender, systolic blood pressure, Glasgow Coma Scale, Injury Severity Score, and type and grade of organs injured. Our primary outcome measures were: hemorrhage complications and need for intervention (operative intervention and/or angioembolization).
Results:
A total of 116 patients (58 early, 29 intermediate, and 29 late) were included. There were no differences in age (P = .5), Injury Severity Score (P = .6), type (P = .1), and grade of injury of the organ (P = .6) between the 3 groups. There were 67 liver (43.2%), 63 spleen (40.6%), 49 kidney (31.6%), and 24 multiple solid organ (15.4%) injuries. There was no difference in operative intervention (P = .8) and postprophylaxis blood transfusion (P = .3) between the 3 groups.
Conclusions:
Early enoxaparin-based anticoagulation may be a safe option in trauma patients with blunt solid organ injury. This study showed no significant correlation between early anticoagulation and development of bleeding complications.
More Related Videos
 05:22
Intraoperative Strategy under Complex Vascular Adhesion for Laparoscopic Radical Resection of Bismuth-Corlette Type IIIb Perihilar Cholangiocarcinoma
Published on: February 13, 2026
 06:00
Laparoscopic Anatomic S7+S8d Resection Preserving Inferior Right Hepatic Vein and S6 with Right Hepatic Vein Transection
Published on: December 30, 2025
Related Concept Videos
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:29
Venous Thrombosis III: Interprofessional Care
 01:27
Pulmonary Embolism III: Nursing Management
 01:30
Venous Thrombosis IV: Nursing Management
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:22
Aneurysm IV: Nursing Management