

Leucocyte expression of complement C5a receptors exacerbates infarct size after myocardial reperfusion injury
Vince C De Hoog1, Leo Timmers1, Amerik Van Duijvenvoorde1
1Laboratory of Experimental Cardiology, Department of Cardiology UMC Utrecht, University Medical Center Utrecht, Heidelberglaan 100, Room G02.523, Utrecht 3584 CX, The Netherlands.

Insights
Blocking the C5a receptor (C5aR) on circulating leukocytes significantly reduced infarct size and improved cardiac function in a mouse model of myocardial ischemia-reperfusion (IR) injury. This targeted approach lessens inflammation and apoptosis, offering a promising strategy for preventing heart damage.
Area of Science:
- Cardiovascular Research
- Immunology
- Molecular Medicine
Background:
- Acute myocardial infarction requires early reperfusion, but this process can cause ischemia-reperfusion (IR) injury, leading to further myocardial damage.
- Complement activation, specifically via C5a binding to its receptor (C5aR), is implicated in the pathogenesis of IR injury.
Purpose of the Study:
- To investigate the role of C5aR in myocardial infarct size and cardiac function following IR injury.
- To determine if C5aR on circulating leukocytes mediates IR injury.
Main Methods:
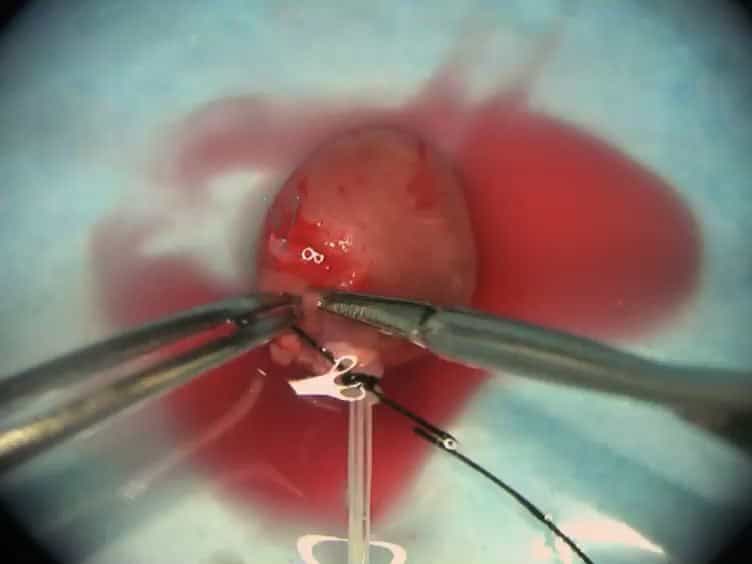
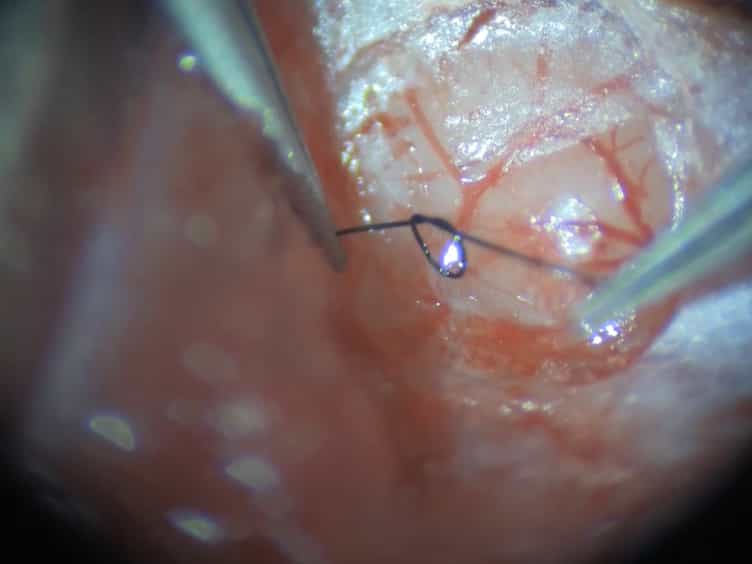
- Myocardial IR injury was induced in wild-type (WT) BALB/c mice and C5aR knockout (C5aR(-/-)) mice.
- Bone marrow chimeras were used to assess the role of C5aR on leukocytes versus resident cells.
- Infarct size, leukocyte infiltration, apoptosis markers (Caspase-3/7), and cardiac function (ejection fraction) were evaluated.
Main Results:
- C5aR(-/-) mice exhibited significantly reduced infarct size compared to WT mice (28.5% vs. 35.7%).
- Bone marrow chimeras confirmed that C5aR absence on circulating leukocytes was responsible for the reduced infarct size.
- Reduced infarct size correlated with decreased neutrophil, T cell, and macrophage infiltration, lower apoptosis, and improved ejection fraction 4 weeks post-IR.
Conclusions:
- Absence of C5aR on circulating leukocytes mitigates myocardial IR injury by reducing inflammation and apoptosis.
- Improved cardiac function was observed in mice lacking C5aR on leukocytes.
- Targeted blockade of C5aR presents a potential therapeutic strategy for preventing myocardial IR injury.
Aims:
Early reperfusion is mandatory for the treatment of acute myocardial infarction. This process, however, also induces additional loss of viable myocardium, called ischaemia-reperfusion (IR) injury. Complement activation plays an important role in IR injury, partly through binding of C5a to its major receptor (C5aR). We investigated the role of C5aR on infarct size and cardiac function in a model for myocardial IR injury.
Methods And Results:
BALB/c (WT) mice and C5aR(-/-) mice underwent coronary occlusion for 30 min, followed by reperfusion. Infarct size, determined 24 h after IR, was reduced in C5aR(-/-) mice compared with WT mice (28.5 ± 2.1 vs. 35.7 ± 2.5%, P = 0.017). Bone marrow (BM) chimaera experiments showed that this effect was due to the absence of C5aR on circulating leucocytes, since a similar reduction in infarct size was observed in WT mice with C5aR-deficient BM cells (25.3 ± 2.2 vs. 34.6 ± 2.8%, P < 0.05), but not in C5aR(-/-) mice with WT BM cells. Reduced infarct size was associated with fewer neutrophils, T cells, and macrophages in the infarcted area 24 h after IR in C5aR(-/-) mice, and also with lower levels of Caspase-3/7 indicating less inflammation and apoptosis. Echocardiography 4 weeks after IR showed an improved ejection fraction in C5aR(-/-) mice (25.8 ± 5.5 vs. 19.2 ± 5.4%, P < 0.001).
Conclusion:
The absence of C5aR on circulating leucocytes reduces infarct size, is associated with reduced leucocyte infiltration and with less apoptosis in the infarcted myocardium, and improves cardiac function in a mouse model of myocardial IR injury. Selective blocking of C5aR might be a promising strategy to prevent myocardial IR injury.
Related Concept Videos
 01:21
Myocarditis I: Introduction
 01:25
Acute Inflammation II: Local and Systemic Effects
 01:27
Complement System
 01:26
Acute Inflammation I: Cellular Phase
 01:38
Inflammation
 01:21
Cytotoxic Edema: Pathophysiology