Related Experiment Video
Updated: Apr 27, 2026

An Anatomical Study of Nerves at Risk During Minimally Invasive Hallux Valgus Surgery
Published on: February 17, 2018
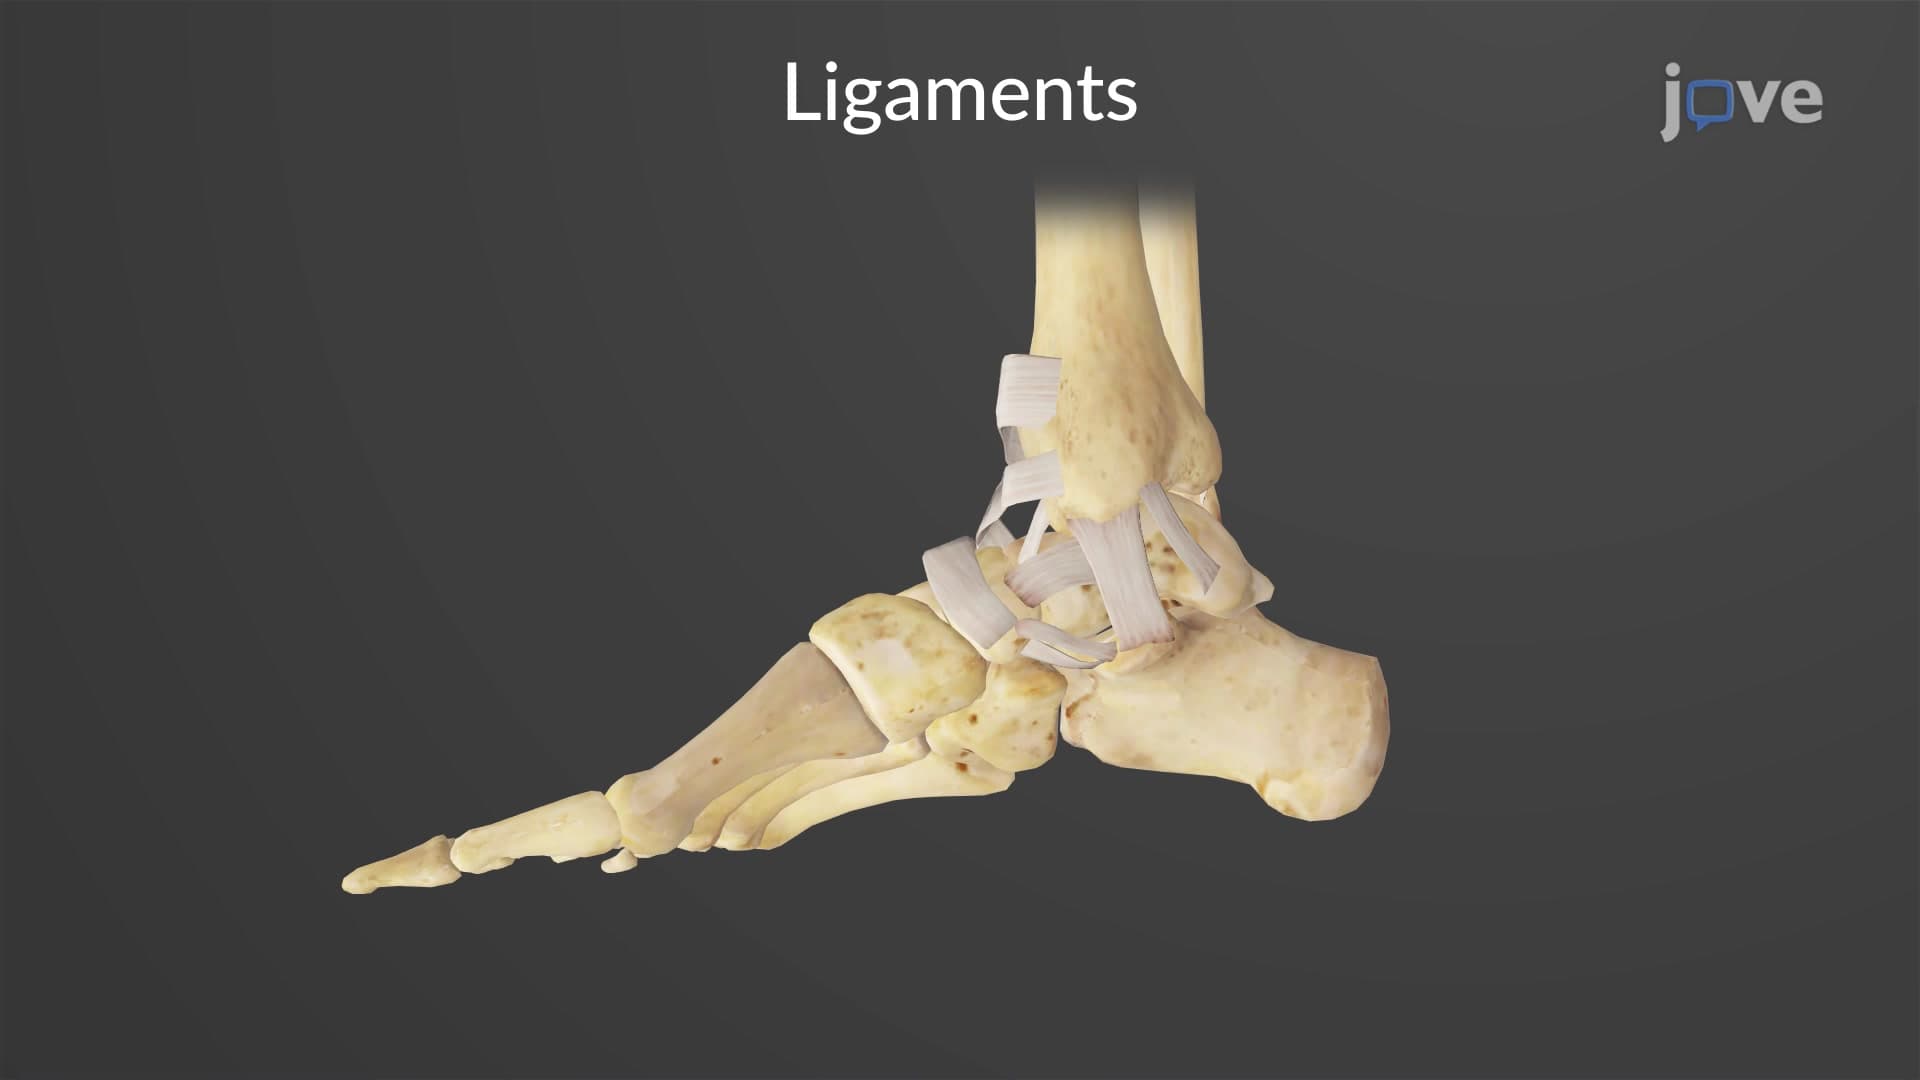
Qualitative and Quantitative Anatomic Investigation of the Lateral Ankle Ligaments for Surgical Reconstruction
Thomas O Clanton1, Kevin J Campbell1, Katharine J Wilson1
1Steadman Philippon Research Institute (T.O.C., K.J.C., K.J.W., M.P.M., M.T.G., C.A.W., and R.F.L.), Suite 1000, and The Steadman Clinic (T.O.C. and R.F.L.), Suite 400, 181 West Meadow Drive, Vail, CO 81657. E-mail address for Thomas O. Clanton: tclanton@thesteadmanclinic.com.

Background:
Lateral ankle sprains are common sports injuries that may require surgery for chronic lateral ankle instability. Anatomic repair or reconstruction is desired, yet there is a scarcity of quantitative information regarding the origins and insertions of the lateral ligaments related to surgically pertinent osseous landmarks.
Methods:
Fourteen ankle specimens were dissected to isolate the anterior talofibular ligament, calcaneofibular ligament, posterior talofibular ligament, and cervical ligament. A three-dimensional coordinate measurement device was used to determine the origins, insertions, footprint areas, orientations, and distances from osseous landmarks.
Results:
A single-banded anterior talofibular ligament was identified in seven of the fourteen specimens, and a double-banded anterior talofibular ligament was identified in the remaining seven. The single-banded anterior talofibular ligament originated an average of 13.8 mm (95% confidence interval [CI], 12.3 to 15.3) from the inferior tip of the lateral malleolus at the anterior fibular border and inserted an average of 17.8 mm (95% CI, 16.3 to 19.3) superior to the apex of the lateral talar process along the anterior border of the talar lateral articular facet. The calcaneofibular ligament originated an average of 5.3 mm (95% CI, 4.2 to 6.5) from the inferior tip of the lateral malleolus at the anterior fibular border and inserted an average of 16.3 mm (95% CI, 14.5 to 18.1) from the posterior point of the peroneal tubercle. The posterior talofibular ligament was the largest ligament and originated an average of 4.8 mm (95% CI, 3.7 to 5.9) superior to the inferior tip of the lateral malleolus in the digital fossa to insert an average of 13.2 mm (95% CI, 11.5 to 14.9) from the talar posterolateral tubercle. The cervical ligament originated on the superior part of the calcaneus and inserted at a point that was approximately 50% of the talar neck anteroposterior distance.
Conclusions:
Consistent distances from the anterior talofibular ligament, calcaneofibular ligament, posterior talofibular ligament, and cervical ligament footprint centers to osseous landmarks were identified.
Clinical Relevance:
Footprint center distances from surgically relevant osseous landmarks identified in this study can be used during reconstructive surgery of the lateral ankle ligaments and may result in more anatomically accurate placement of the reconstructed ligaments.