Related Experiment Video
Updated: Apr 27, 2026
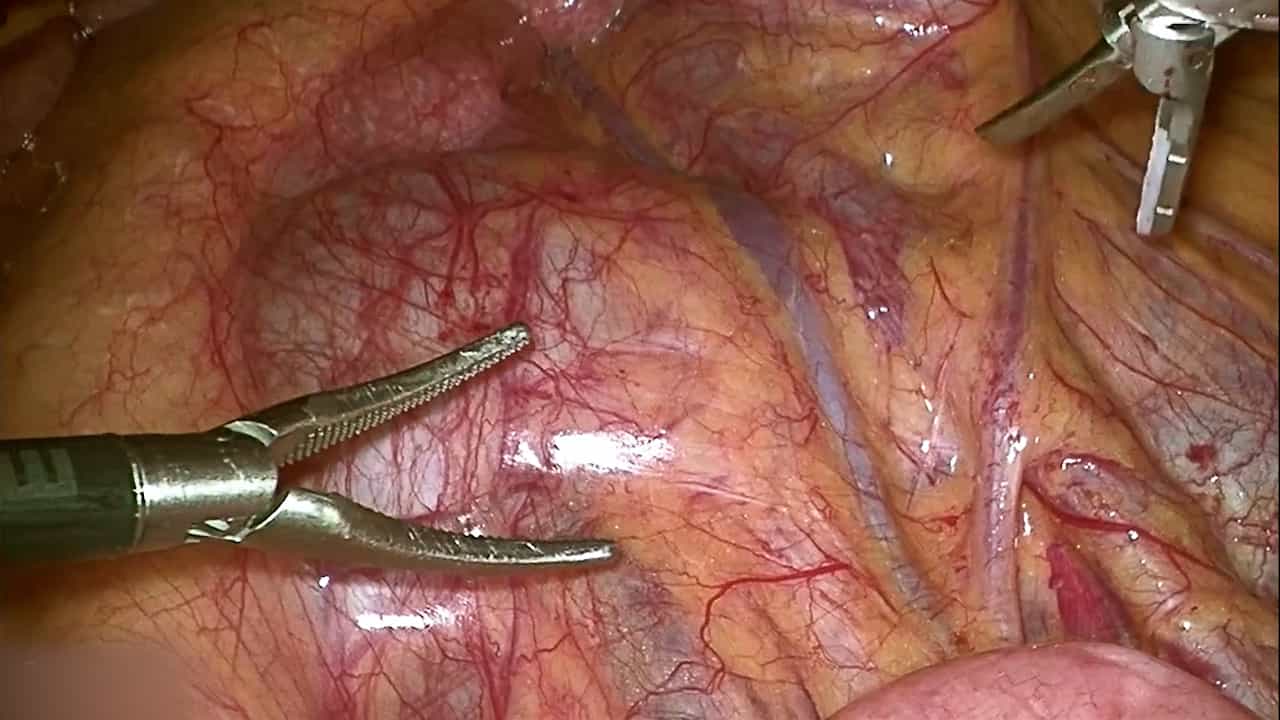
Transmesenteric Laparoscopic Pyeloplasty in Trendelenburg Position for Horseshoe Kidney with Hydronephrosis
Published on: July 8, 2025
Unstented laparoscopic pyeloplasty in young children (1-5 years old): a comparison with a repair using double-J stent
Radim Kočvara1, Josef Sedláček1, Marcel Drlík1
1Department of Urology, General Teaching Hospital in Praha and Charles University 1st Faculty of Medicine, Praha, Czech Republic.

Insights
Unstented laparoscopic pyeloplasty is feasible in select young children, avoiding secondary anesthesia and stent complications. This approach offers comparable outcomes to stented laparoscopic and open surgeries for high-grade hydronephrosis.
Area of Science:
- Pediatric Urology
- Minimally Invasive Surgery
- Pediatric Nephrology
Background:
- High-grade hydronephrosis in young children often requires pyeloplasty.
- Traditional pyeloplasty may involve stents, increasing risks of complications and repeat anesthesia.
- Laparoscopic pyeloplasty offers a minimally invasive alternative.
Purpose of the Study:
- To assess the feasibility of unstented laparoscopic pyeloplasty in children aged 1-5 years.
- To compare outcomes of unstented vs. stented laparoscopic pyeloplasty.
- To evaluate the safety and efficacy compared to open surgery.
Main Methods:
- A retrospective study of 70 children (1-5 years) with high-grade hydronephrosis undergoing laparoscopic pyeloplasty.
- Group L1: 34 unstented repairs; Group L2: 21 double-J stent repairs; Group L3: 15 uretero-pyelostomy stent repairs.
- Outcomes compared with 52 age-matched children who had open surgery.
Main Results:
- Operation times were shorter in unstented and double-J stented laparoscopic groups compared to uretero-pyelostomy stented group and open repairs.
- Complication rates were similar across all laparoscopic groups and between laparoscopic and open surgery groups.
- Specific complications included urine leakage/obstruction (unstented), obstruction/pyelonephritis (double-J), and stent displacement (uretero-pyelostomy).
Conclusions:
- Unstented laparoscopic pyeloplasty is a safe and effective option for selected young children with favorable anatomy.
- This technique avoids the need for secondary anesthesia and stent-related issues.
- It demonstrates comparable outcomes to stented laparoscopic and open pyeloplasty procedures.
Objective:
To evaluate feasibility of unstented laparoscopic pyeloplasty in young children to prevent pyelonephritis and second anaesthesia.
Patients And Methods:
During 2006-2013, 70 children (1-5 years old) underwent laparoscopic pyeloplasty for high grade hydronephrosis. Unstented repair was indicated in 34 children (GroupL1), double-J stent was placed in 21 patients (Group L2) and uretero-pyelostomy stent (Cook) in 15 patients (Group L3). Stenting was preferred in large thin-walled pelvis, thin ureter, kidney malrotation, and unfavourable course of crossing vessels. The outcome was compared with age-matched group of 52 children who had open surgery during 1996-2006 (Groups O1, O3).
Results:
Operation times were significantly shorter in Groups L1 and L2 than in Group L3; the times were shorter in open repairs. Three patients with crossing vessels from Group L1 had urine leakage and one had obstruction (11.4%). In Group L2, one patient had obstruction, one incorrect placement of the stent, and one girl had serious pyelonephritis (14.3%). In Group L3, displacement of uretero-pyelostomy occurred in one patient (6.7%). There is no statistical difference between laparoscopic groups and between laparoscopic and open groups.
Conclusion:
Unstented laparoscopic pyeloplasty is a safe procedure in selected young children with favourable anatomical conditions preventing additional anaesthesia and stent-related complications.
More Related Videos
 04:14
Laparoscopic Choledochal Cyst Excision and Roux-en-Y Choledochojejunostomy in Adults
Published on: February 28, 2025
 06:39
Technical Modification of the Terminal Ureter During Total Transperitoneal Laparoscopic Nephroureterectomy for Upper Urinary Tract Urothelial Carcinoma
Published on: November 22, 2019
Related Concept Videos
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:22
Imaging Studies V: Intravenous Urography and Retrograde Pyelography