Related Experiment Video
Updated: Apr 27, 2026

A Reversible, Non-invasive Method for Airway Resistance Measurements and Bronchoalveolar Lavage Fluid Sampling in Mice
Published on: April 13, 2010
Allergic reaction to suxamethonium during emergency caesarean section and pseudocholinesterase deficiency in the same
Gordana Brozović1, Branka Mazul Sunko, Tomislav Hafner
1Department of Anaesthesiology and Intensive Care, University Medical Center Sestre Milosrdnice, Zagreb, Croatia, gordana.brozovic@kbcsm.hr.

An allergic reaction during the caesarean section can be harmful for mother and foetus. Our patient has undergone an urgent caesarean section due to the imminent threat of foetal hypoxia. After operation, we applied prolonged mechanical ventilation. The anaesthesia was induced with thiopental and suxamethonium. Suxamethonium is associated with the highest incidence of allergic reactions but it is a neuromuscular blocking agent of choice for an emergency operation. During the operation, about 10 min. after induction, the systolic blood pressure dropped suddenly to 67 mmHg, the heart rate increased to 145 beats per minute and the oxygen saturation dropped to 60 %. A small degree of bronchospasm developed but there wasn't any kind of skin reaction. We thought of an allergic reaction, the obstetrical pulmonary embolism and an acute cardiac failure. The baby was delivered promptly in good condition. Within 10 min. all vital signs normalized. The operation continued without problems. Unexpectedly, during waking up from anaesthesia the patient became dyspnoeic, laryngospasm appeared, the oxygen saturation dropped again, strong facial and tongue oedema appeared and an urgent reintubation had to be performed. The laboratory results pointed out elevated mast cell tryptase level and significant pseudocholinesterase deficiency. About 2 months later, immunologist excluded thiopental and latex, and suggested that suxamethonium was the "trigger" factor. In our case the respiratory insufficiency was caused by two different and unrelated pathological mechanisms: biphasic allergic reaction and prolonged neuromuscular block caused by pseudocholinesterase deficiency.
An allergic reaction during the caesarean section can be harmful for mother and foetus. Our patient has undergone an urgent caesarean section due to the imminent threat of foetal hypoxia. After operation, we applied prolonged mechanical ventilation. The anaesthesia was induced with thiopental and suxamethonium. Suxamethonium is associated with the highest incidence of allergic reactions but it is a neuromuscular blocking agent of choice for an emergency operation. During the operation, about 10 min. after induction, the systolic blood pressure dropped suddenly to 67 mmHg, the heart rate increased to 145 beats per minute and the oxygen saturation dropped to 60 %. A small degree of bronchospasm developed but there wasn't any kind of skin reaction. We thought of an allergic reaction, the obstetrical pulmonary embolism and an acute cardiac failure. The baby was delivered promptly in good condition. Within 10 min. all vital signs normalized. The operation continued without problems. Unexpectedly, during waking up from anaesthesia the patient became dyspnoeic, laryngospasm appeared, the oxygen saturation dropped again, strong facial and tongue oedema appeared and an urgent reintubation had to be performed. The laboratory results pointed out elevated mast cell tryptase level and significant pseudocholinesterase deficiency. About 2 months later, immunologist excluded thiopental and latex, and suggested that suxamethonium was the "trigger" factor. In our case the respiratory insufficiency was caused by two different and unrelated pathological mechanisms: biphasic allergic reaction and prolonged neuromuscular block caused by pseudocholinesterase deficiency.

Related Concept Videos
 01:19
Depolarizing Blockers: Pharmocokinetics
 01:26
Anticholinesterase Agents: Poisoning and Treatment
Irreversible agents form a strong bond with the cholinesterase enzyme, making it inactive. The breakdown of the phosphorylated enzyme is...
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...
 01:28
Depolarizing Blockers: Mechanism of Action
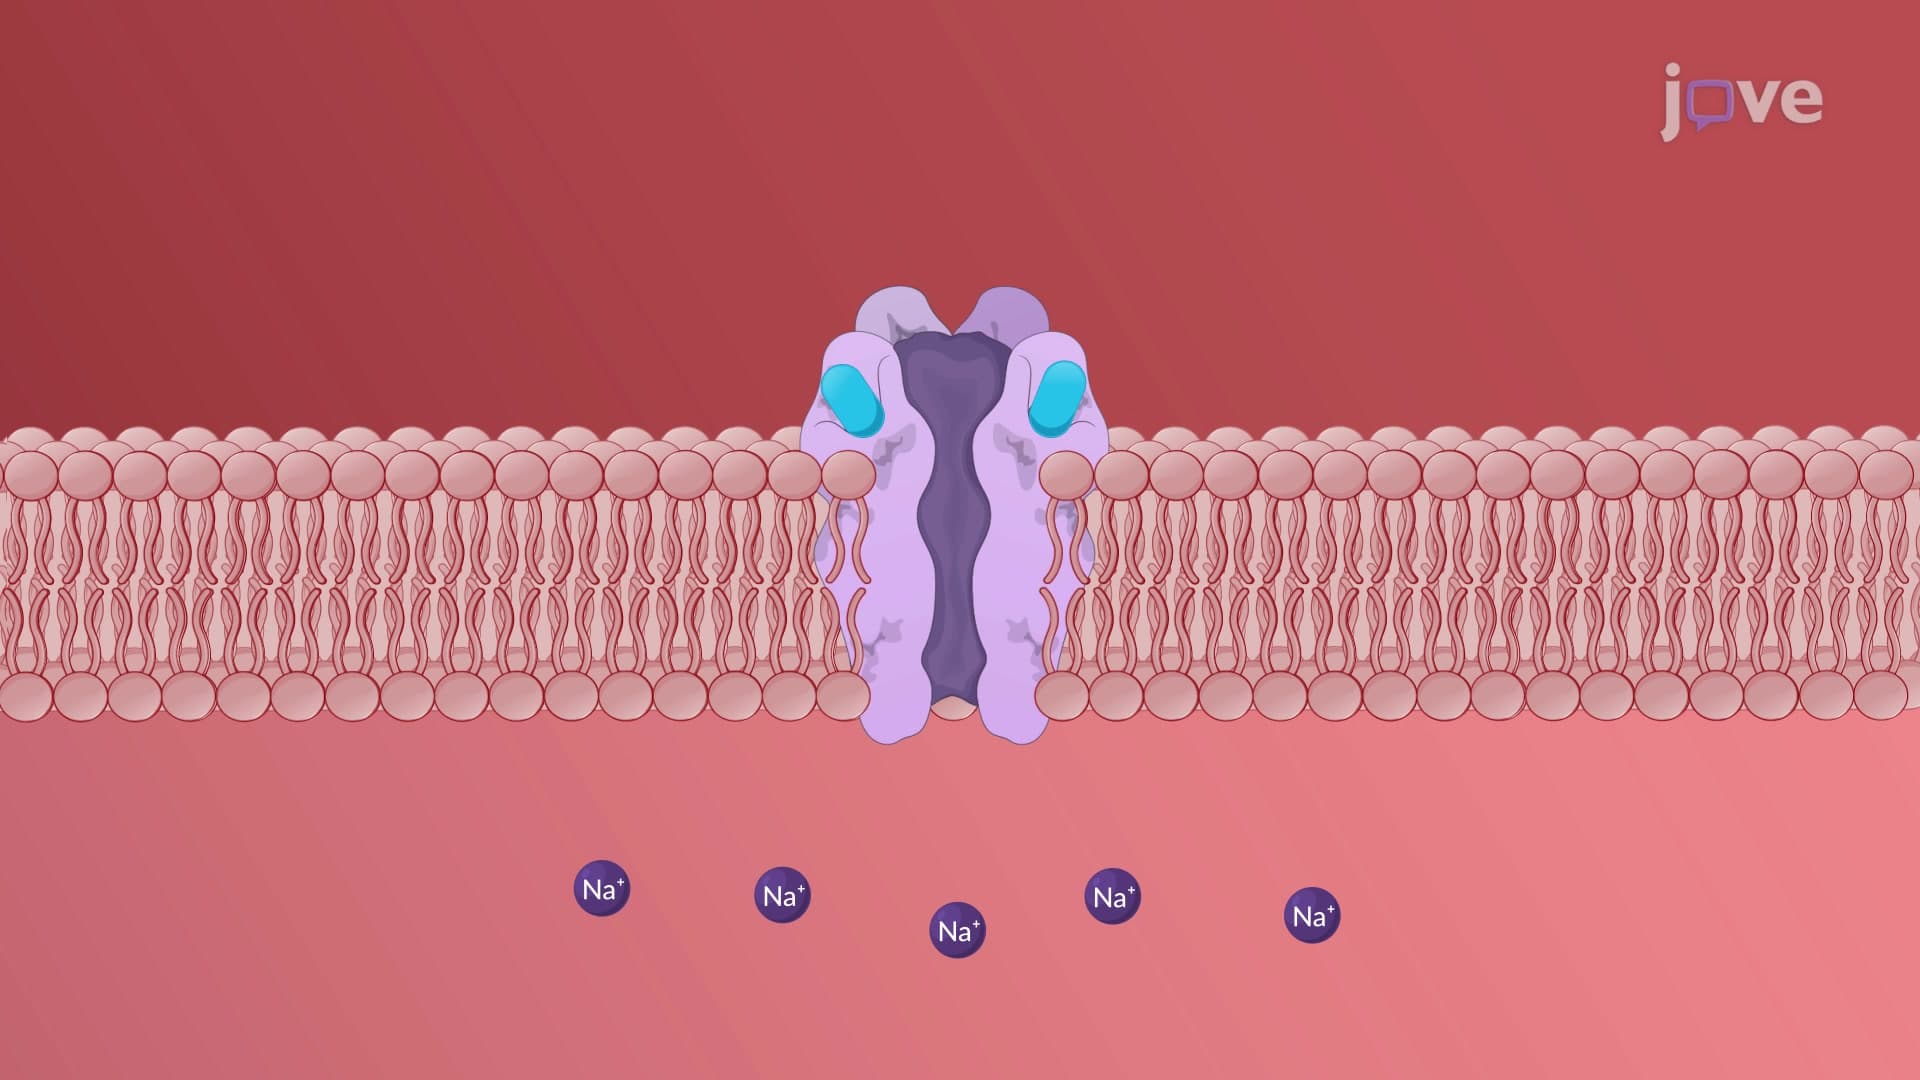
Succinylcholine is the most commonly used depolarizing blocker. Chemically, it constitutes two molecules of acetylcholine joined together by an acetate methyl group. They act on the receptors in the same way as acetylcholine. Because...
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:30
Indirect-Acting Cholinergic Agonists: Pharmacological Actions
At the neuromuscular junction, these agents work by inhibiting the breakdown of acetylcholine, allowing it to remain bound to the receptor and bind to nearby receptors. This process leads to repetitive firing of the endplate, causing muscle...