Related Experiment Video
Updated: Aug 10, 2026


Employing the Forced Oscillation Technique for the Assessment of Respiratory Mechanics in Adults
Published on: February 9, 2022
Spirometric and exhaled nitric oxide reference values in preschool children from the community of Navarra

Insights
This study developed reference equations for spirometry in preschool children, enabling better diagnosis and follow-up of respiratory conditions. Normal exhaled nitric oxide values were also established for this age group.
Area of Science:
- Pediatric Pulmonology
- Respiratory Physiology
- Clinical Diagnostics
Background:
- Spirometry use in preschool children with respiratory diseases is limited due to lack of consensus on test criteria and reference data.
- Establishing quality spirometric maneuvers and reference values is crucial for accurate diagnosis and management.
- This study addresses the absence of local reference data for preschool-aged children.
Purpose of the Study:
- To develop reference equations for spirometry in preschool children.
- To assess normal values for exhaled nitric oxide (FeNO) in this age group.
- To provide data for improved clinical practice in pediatric respiratory care.
Main Methods:
- Enrolled 114 healthy preschool children aged 3-6 years.
- Assessed spirometric maneuvers and exhaled nitric oxide (FeNO) values.
- Constructed regression equations using univariate and multivariate models based on height.
Main Results:
- 60 children (53%) met American Thoracic Society/European Respiratory Society criteria for acceptable spirometry.
- Regression equations were derived: FVC = -2.6 + 0.036 x height, FEV1 = -2.04 + 0.029 x height, FEV0.5 = -1.53 + 0.022 x height.
- Mean FeNO value was 11 (4.9) ppb in 56 children.
Conclusions:
- Preschool children can perform quality spirometry with appropriate training and equipment.
- Developed regression equations allow calculation of reference ranges for spirometry in this population.
- Established normal FeNO values provide a benchmark for clinical assessment.
Background And Objective:
Preschool children can perform quality, reproducible spirometric maneuvers, provided appropriate equipment is used and specially trained nursing staff training are available. However, use of spirometry for the diagnosis and follow-up of preschool children with respiratory diseases remains limited in clinical practice, because consensus on test quality and acceptability criteria and reference data are lacking. We initiated the present study with the aim of developing reference equations, since tables of normal values for this age group are not available in our area.
Patients And Methods:
The study population comprised healthy preschool children in our community. Normal values for exhaled nitric oxide in this age range were assessed. Regression equations were constructed using univariate and multivariate models.
Results:
A total of 114 healthy preschool children aged 3 to 6 years were enrolled. According to the criteria of the American Thoracic Society/European Respiratory Society, 60 children were able to perform acceptable and reproducible spirometric maneuvers. The best correlations were observed for the untransformed linear regression model that included height. The correlation coefficients for forced vital capacity (FVC), forced expiratory volume in the first second (FEV1), and FEV0.5 were 0.89, 0.88, and 0.86, respectively. The regression equations for the calculation of reference values were as follows: FVC = -2.6 + 0.036 x height, cm FEV1 = -2.04 + 0.029 x height, cm FEV0.5 = -1.53 + 0.022 x height, cm. We obtained fraction of inhaled nitric oxygen (FeNO) values for 56 children. The mean (SD) value was 11 (4.9) ppb.
Conclusions:
Most preschool children in our area were able to perform quality spirometry maneuvers. We obtained regression equations that allowed us to calculate the reference ranges in our population and the distribution of normal FeNO values.


Related Concept Videos
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:26
Respiratory Volumes and Capacities I
 01:15
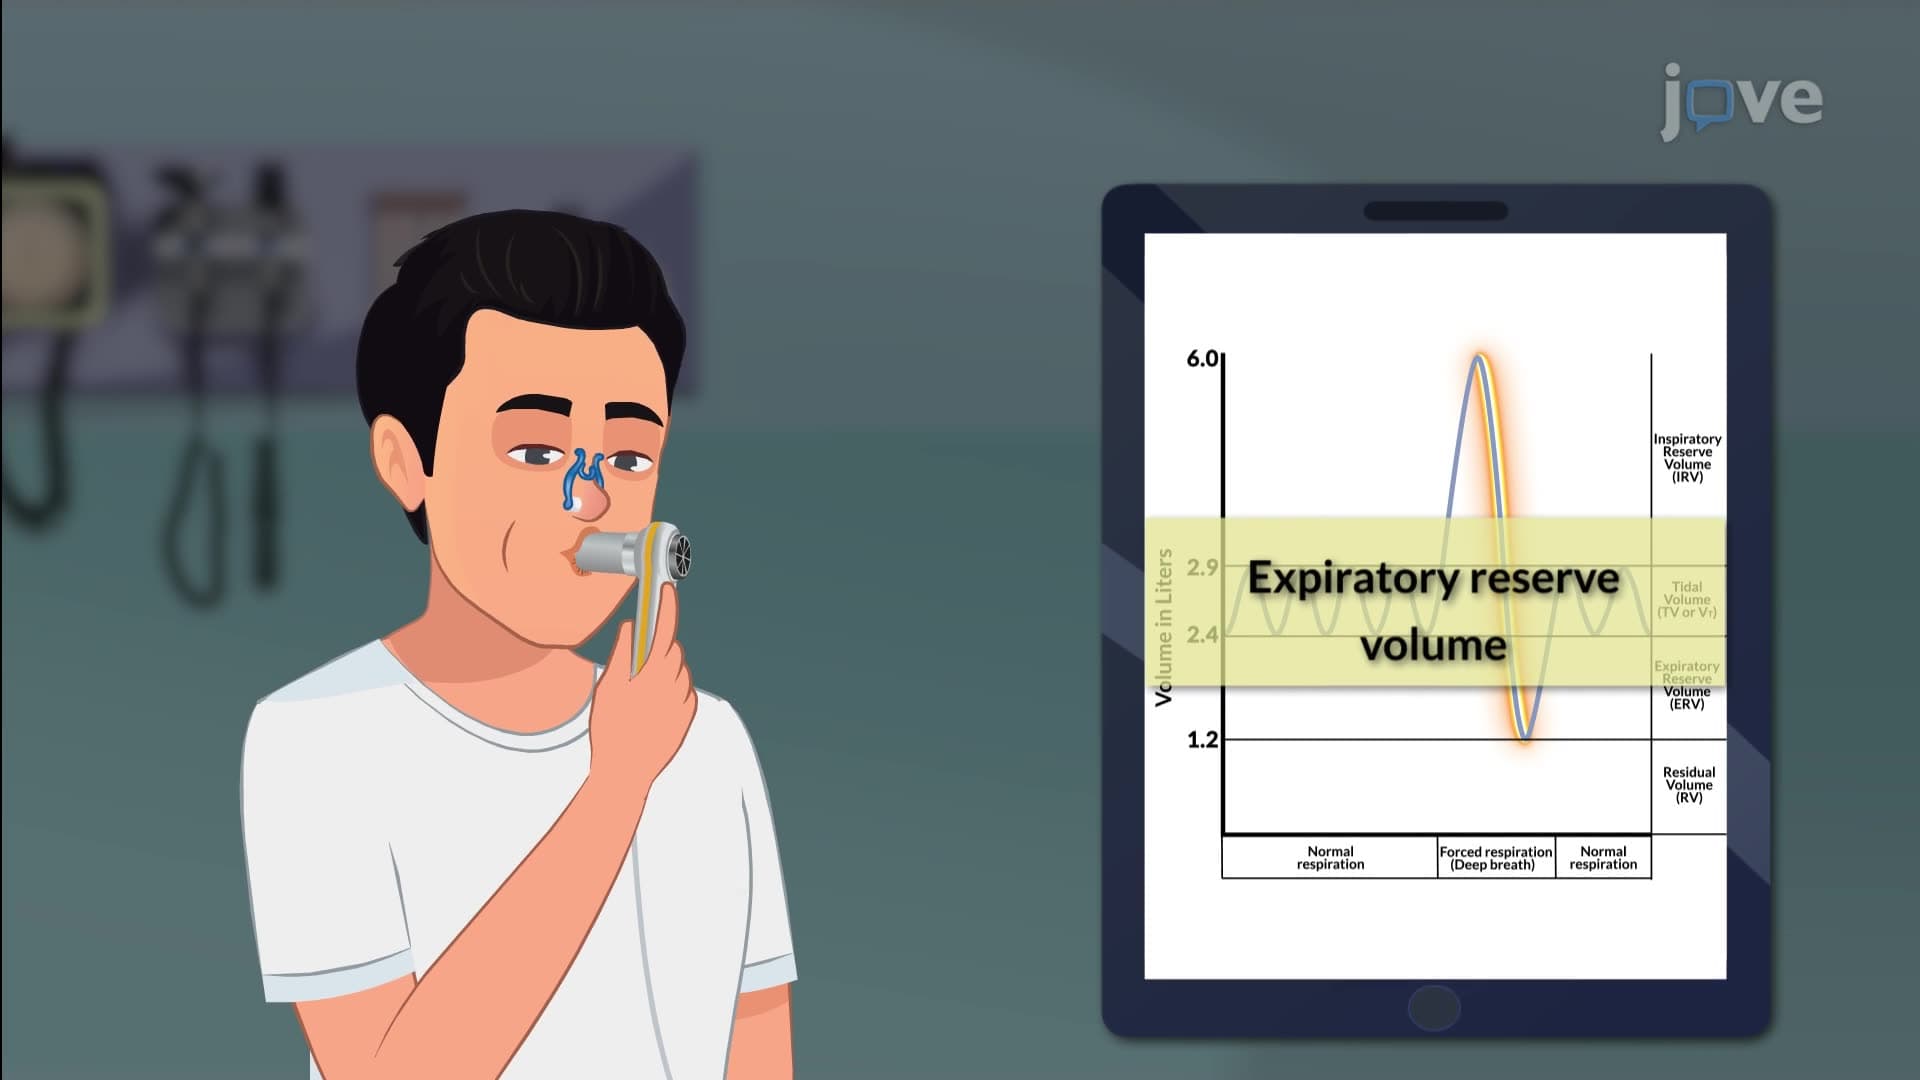
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...
 01:22
Respiratory Volumes and Capacities
 01:25
Pulmonary Function Tests
Pulmonary Function Tests are crucial diagnostic tools for assessing respiratory function, particularly in patients with chronic respiratory disorders. They comprehensively evaluate lung volumes, ventilatory function, breathing mechanics, diffusion, and gas exchange. These tests help diagnose pulmonary diseases and play a significant role in monitoring disease progression, evaluating disability, and assessing response to therapy.
PFTs involve using a spirometer, a...