Related Experiment Video
Updated: Apr 27, 2026
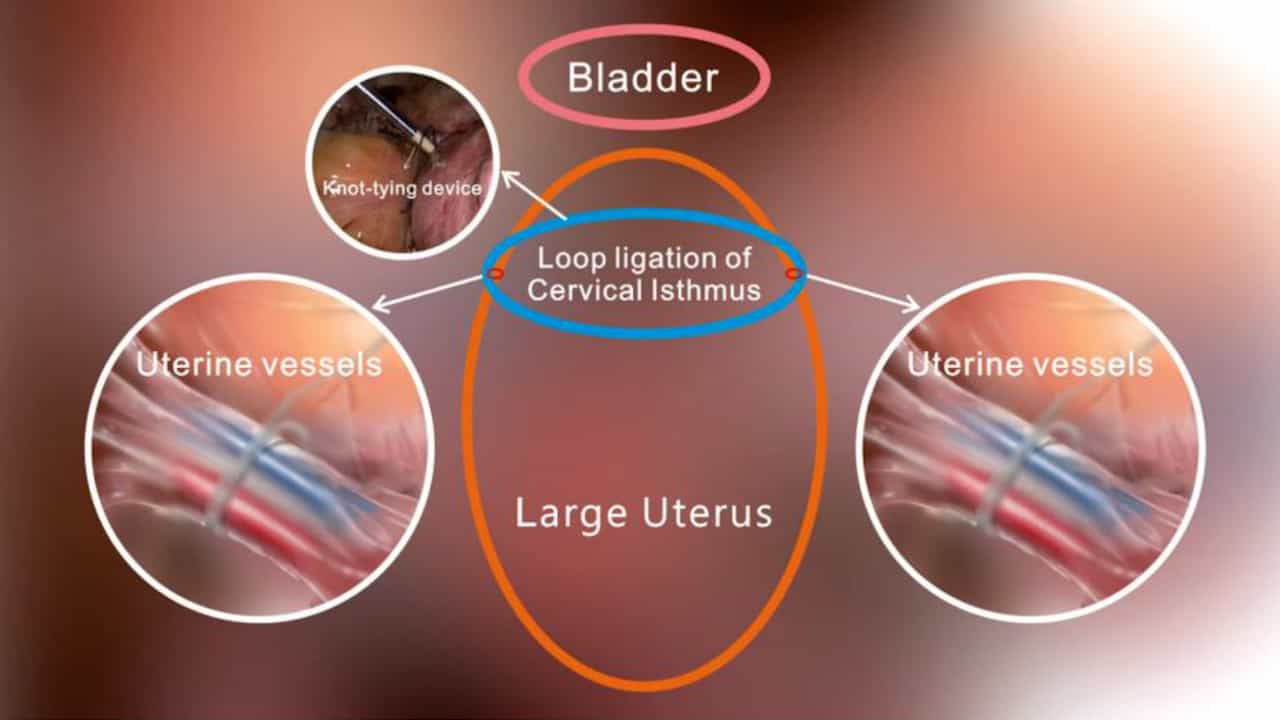

Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Predictive value of volume of cervical tissue removed during LLETZ on subsequent preterm delivery: a cohort study
Sarah J Kitson1, Emma Greig1, Enid Michael1
1Department of Obstetrics and Gynaecology, Royal Lancaster Infirmary, Ashton Road, Lancaster LA1 4RP, United Kingdom; Department of Obstetrics and Gynaecology, Royal Victoria Hospital, Newcastle-upon-Tyne, United Kingdom.

Objective:
To evaluate the impact of volume of tissue removed during large loop excision of transformation zone on subsequent preterm birth rates.
Study Design:
A retrospective cohort study was carried out in a single, large tertiary referral unit in UK. A total of 556 women who delivered between January 2008 and December 2011 following a previous large loop excision of transformation zone procedure or punch biopsy were identified from the maternity and colposcopy databases. Demographic data, gestational age at delivery, birthweight, neonatal outcome and dimensions of excised cervical specimen were collected. Pregnancy outcomes for women who had a previous loop excision were compared to a matched control group who had undergone punch biopsies only.
Results:
There was a significant increase in preterm birth rate in the large loop excision group compared to the control group (9.0% vs. 3.6%, respectively, RR 2.5, 95% CI 1.224-5.107). Women who had undergone at least one previous loop excision had more than a threefold increased risk of spontaneous preterm birth compared with their matched controls. However, no relationship between volume or depth of cervical tissue excised and subsequent gestation at delivery could be demonstrated.
Conclusions:
Whilst LLETZ is associated with an increased rate of preterm birth, the volume of tissue removed does not appear to influence the subsequent gestational age at delivery. This should reassure clinicians who should continue to perform LLETZ with adequate tissue margins to ensure complete resection of disease.