Related Experiment Video
Updated: Apr 27, 2026

Single-stage Dynamic Reanimation of the Smile in Irreversible Facial Paralysis by Free Functional Muscle Transfer
Published on: March 1, 2015
[Principles of orthopedic treatment of flaccid paralysis]
1Orthopädische Kinderklinik am Behandlungszentrum Aschau, Bernauer Str.18, 83229, Aschau, Deutschland, l.doederlein@bz-aschau.de.

Background:
Flaccid paralysis is the result of many different causes presenting with a multitude of symptoms ranging from affecting only the efferent pathways up to involvement of both the afferent and efferent loops of the peripheral neuoromotor system. The peripheral distribution corresponds to the damage.
Objectives:
The functional limitations of flaccid paralysis are the result of a permanent or progressive muscular weakness and ensuing contractures, deformities and instabilities which require compensatory and adaptive mechanisms from the patient to cope with these impairments.
Material And Methods:
Compensatory mechanisms are required for gait problems as well as for impaired standing, sitting ability and to optimize the use of the upper extremities. For setting therapeutic indications as well as for the treatment of the patients the causes of the functional deficits and the compensatory efforts from the patient must be considered. A list of the more common problems helps in this respect.
Results:
Every treatment should be subdivided into preventive and therapeutic measures. Preventive options mostly consist of conservative methods while manifest deformities and instabilities are usually treated by combined therapeutic approaches, i.e. surgical and conservative. The correct straightening of the leg axes and joints, balancing and support of the musculature by tendon transfers and bony stabilizations followed by appropriate orthotic devices are the essential therapeutic principles.
Conclusion:
The basis of any management of functional problems in flaccid paralysis has to consider the pathomechanics of the primary deformities and the weakness as well as the compensatory mechanisms which allow the patient to achieve the functional goals. Neither surgery nor orthotic devices alone can fulfil the detailed requirements of a functional improvement. Instead a combination of both will succeed in most cases and is known as surgical-orthotic integration.
Related Concept Videos
 01:28
Classification of Skeletal Muscle Relaxants
Peripherally acting skeletal muscle relaxants interfere with the neurotransmission at the neuromuscular end plate to induce paralysis during...
 01:25
Secondary Spinal Cord Injury llI: Pathophysiology
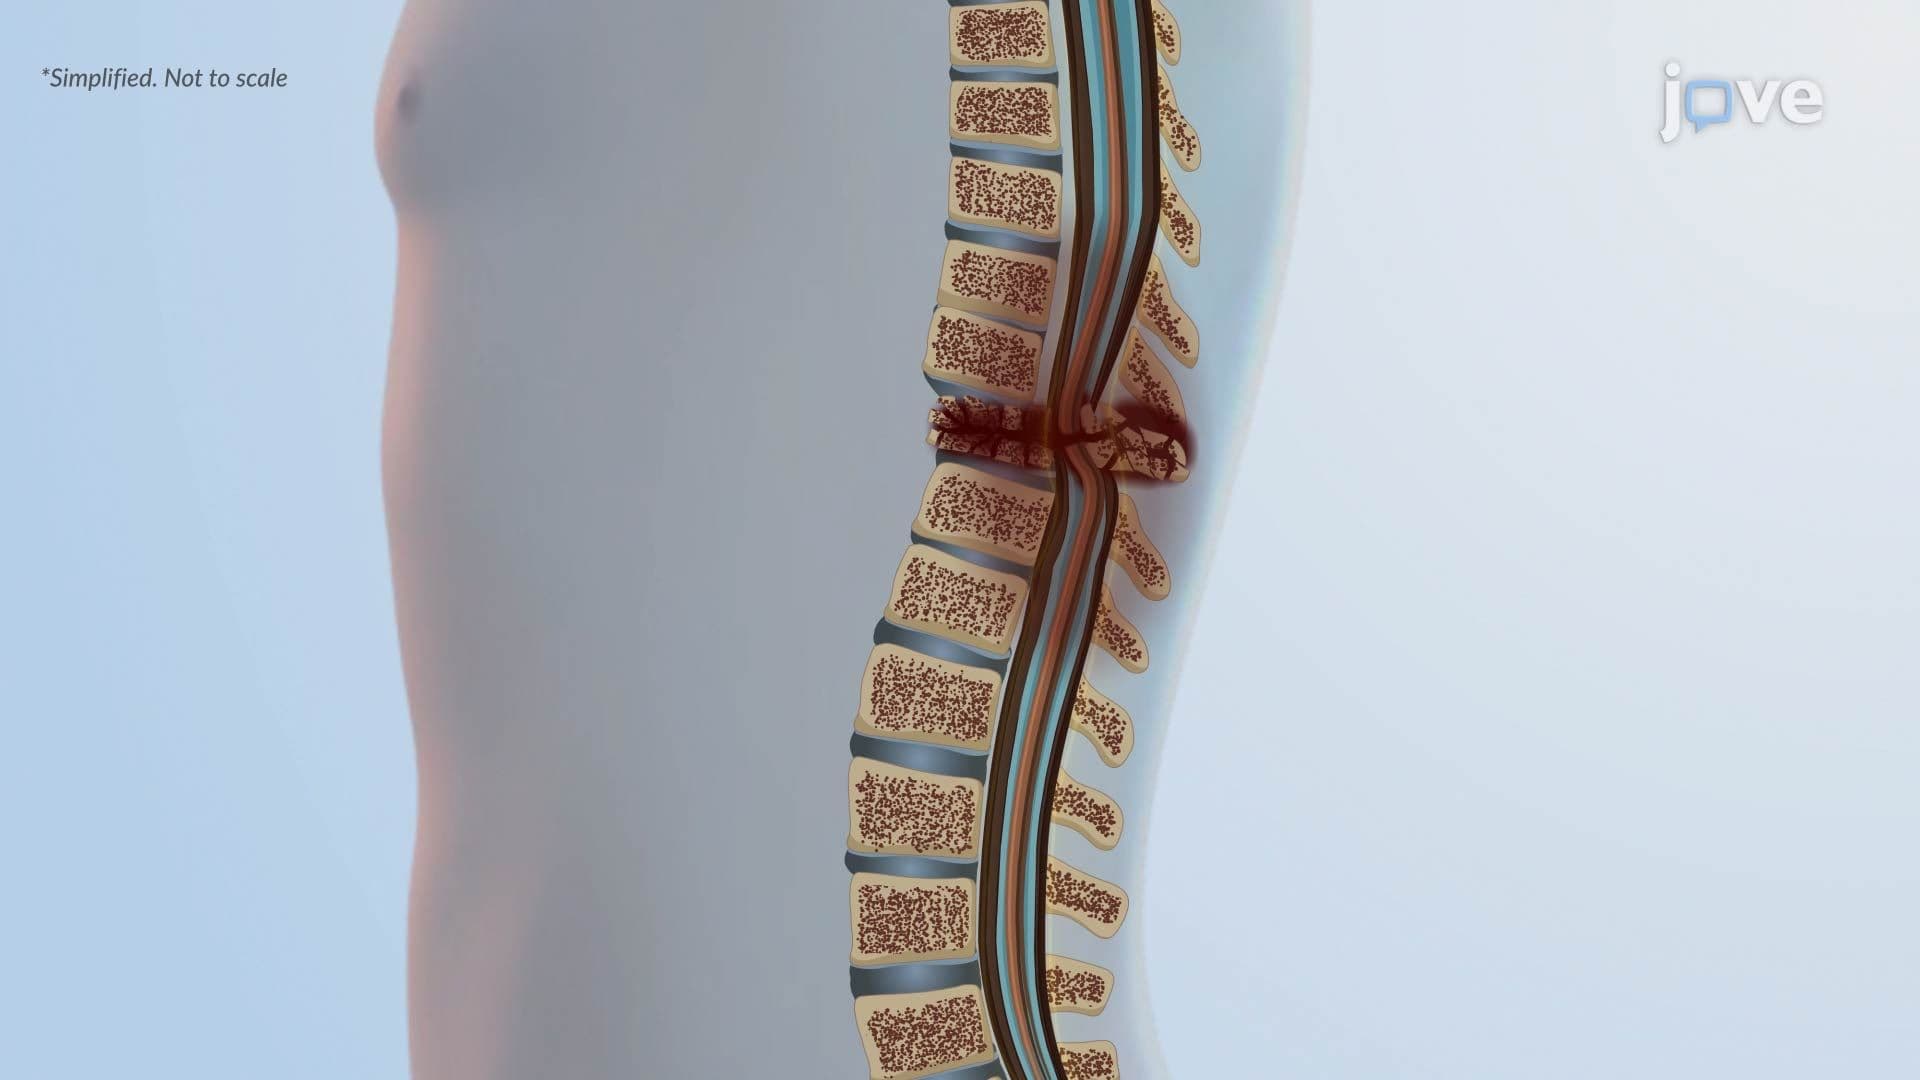 01:14
Spinal Cord Injury ll: Pathophysiology
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History: