Related Experiment Video
Updated: Apr 26, 2026
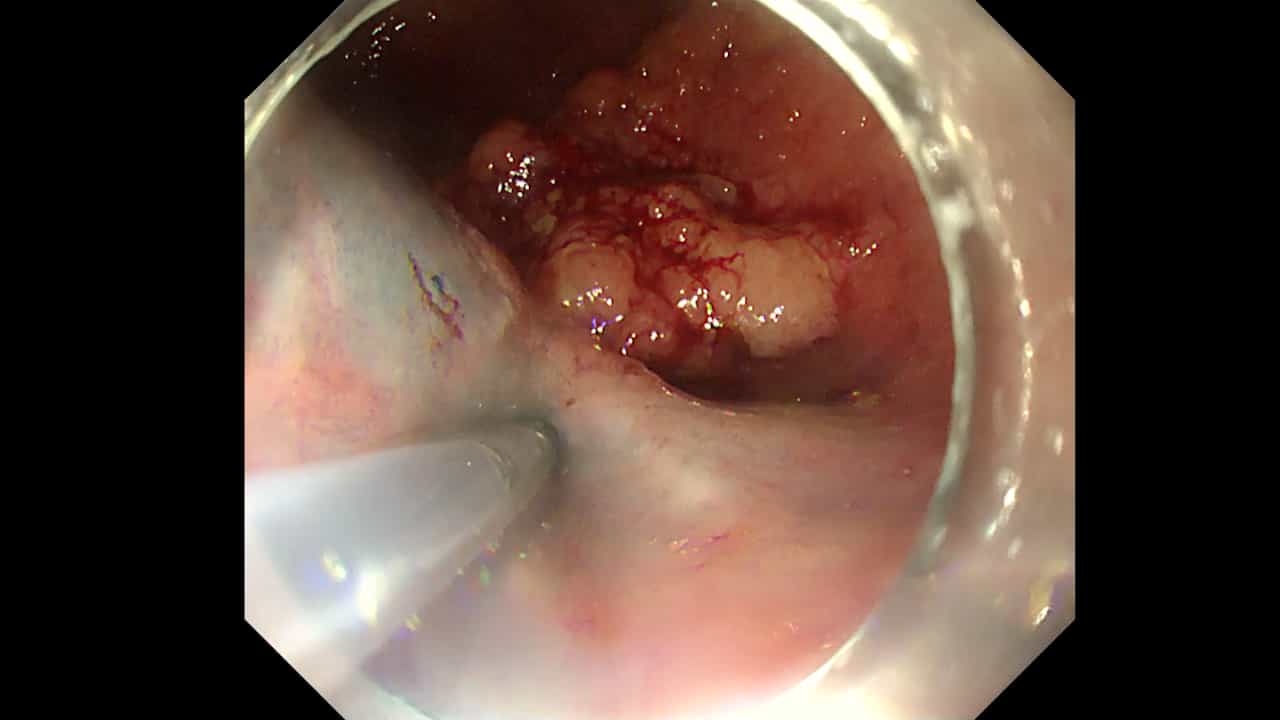

The Pocket-Creation Procedure of Endoscopic Submucosal Dissection for Large Rectal Laterally Spreading Tumors
Published on: February 13, 2026
Potential perioperative advantage of colorectal endoscopic submucosal dissection versus laparoscopy-assisted
Fumihiko Nakamura1, Yutaka Saito, Taku Sakamoto
1Endoscopy Division, National Cancer Center Hospital, 5-1-1 Tsukiji, Chuo-ku, Tokyo, 104-0045, Japan, jymxg256@ybb.ne.jp.

Background:
Endoscopic submucosal dissection (ESD) has recently provided a new treatment strategy for large colorectal neoplasms, as an alternative to laparoscopy-assisted colectomy (LAC). Prospective comparative data on the perioperative course of ESD vis-à-vis LAC are scarce.
Methods:
We prospectively evaluated the perioperative course of colorectal ESD in 300 patients. We evaluated en bloc and curative resection, procedure duration, postoperative parameters [white blood cell count (WBC), C-reactive protein (CRP), and hemoglobin], pain, recovery duration (time to achieve full mobilization, normal diet, and length of hospitalization), and complications. We also prospectively evaluated 190 patients undergoing LAC as a control group.
Results:
The median size of the lesions was 30 mm for ESDs (LACs: 20 mm). The median procedure time was 90 min for ESDs (LACs: 185 min). Postoperative pyrexia was reported in 4 % of ESDs (LACs: 54 %). Only 4 % of ESDs required analgesia (LACs: 61 %). Between the preoperative period and postoperative day 1, the mean difference in WBC and CRP was +1,300/μl for ESDs (LACs: +3,100/μl), and +0.91 mg/dl for ESDs (LACs: +3.96 mg/dl), respectively. A ≥2 g/dl decrease in hemoglobin was observed in 5 % of ESDs (LACs: 30.0 %). Complications were seen in 7 % of ESDs (LACs: 15 %). The rate of delayed bleeding and perforation was 5 and 1.7 % of ESDs, respectively. Although only one of them required laparotomy for peritonitis caused by delayed perforation, others could be managed endoscopically. Additional LAC was required in 16 ESDs due to redefined risk for lymph node metastases. The median hospital stay was 5 days for ESDs (LACs: 10 days). These were consecutive patients with prospective data collection.
Conclusions:
Colorectal ESD is effective, minimally invasive and safe in terms of periperative clinical course. Colorectal ESD provides advantages for treatment of large adenomas and early cancers with no risk of lymph node metastasis.
More Related Videos
 08:26
Clinical Application of Single-Surgeon, Three-Port, Laparoscopic Resection for Colorectal Cancer with Natural Orifice Specimen Extraction
Published on: March 24, 2023
 07:22
Surgical Robot-Assisted Transanal Specimen Extraction Radical Sigmoidectomy Without an Auxiliary Abdominal Incision
Published on: June 13, 2025
