Related Experiment Video
Updated: Apr 26, 2026


Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
Laparoscopic dissection and anatomy of sacral nerve roots and pelvic splanchnic nerves
Alysson Zanatta1, Mateus M Rosin2, Ricardo L Machado2
1Pelvi Urogynecology and Gynecological Surgery, Brasilia, Brazil.

Study Objective:
To demonstrate the technique of laparoscopic dissection for identification of sacral nerve roots and pelvic splanchnic nerves.
Design:
Case report (Canadian Task Force classification III).
Setting:
Private practice hospital in São Paulo, Brazil.
Patient:
A 31-year-old woman with suspected iatrogenic and/or compression of sacral nerve roots. She reported debilitating pelvic, gluteal, and perineal unilateral left-sided pain (score 8 on a pain scale of 0-10), and had primary infertility with 1 previous failed attempt at in vitro fertilization. Surgical history included laparoscopic excision of endometriosis 10 months before the procedure and left oophoroplasty during adolescence because of a benign neoplasm.
Interventions:
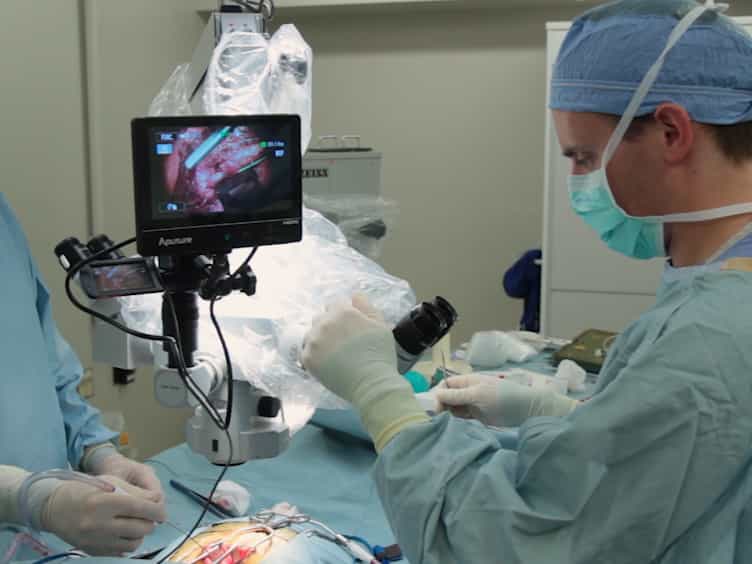
Standard 4-puncture laparoscopy was performed. The peritoneum of the left pelvic sidewall was resected to preclude eventual residual endometriosis. This also enabled identification of uterine vessels including the deep uterine vein, which is the limit between the pars vascularis superiorly and the pars nervosa inferiorly in the uterine broad ligament. Surgery was using the laparoscopic neuro-navigation (LANN) technique, previously described by one of us (M. P.). For identification of the sacral roots, dissection was begun medial to the ureter and lateral to the uterosacral ligament. The Okabayashi pararectal space was entered as deep as possible via blunt dissection in avascular spaces. Hemostasis was performed using 5-mm bipolar forceps, and harmonic energy was not used. The hypogastric fascia was entered from medial to lateral, and the piriformis muscle was identified. The sacral nerve root S1 was identified lying over it. Dissection then proceeded caudally, and sacral roots S2 and S3 were sequentially identified. Small and delicate fibers forming the pelvic splanchnic nerves were isolated emerging from sacral roots S2 and S3. Other nerve fibers were identified caudally, probably representing pelvic splanchnic nerves emerging from S4.
Measurements And Main Results:
The surgical operative time was 70 minutes, and bleeding was minimal. No suspected compression or iatrogenic injury was identified. The patient was discharged on the day after the procedure. At 8-month follow-up, she had partial resolution of pain (score 5, pain scale 0-10), and another failed attempt at in vitro fertilization was attributed to unsatisfactory quality of the embryos. There were no symptoms or dysfunctions attributable to manipulation of the nerves.
Conclusion:
Laparoscopy is a useful tool for identification of sacral roots and pelvic splanchnic nerves in suspected diseases. Its application in the field of neuropelveology can be expanded with proper knowledge and training.

Related Concept Videos
 01:21
Spinal Nerves: Plexus II
The Lumbar Plexus
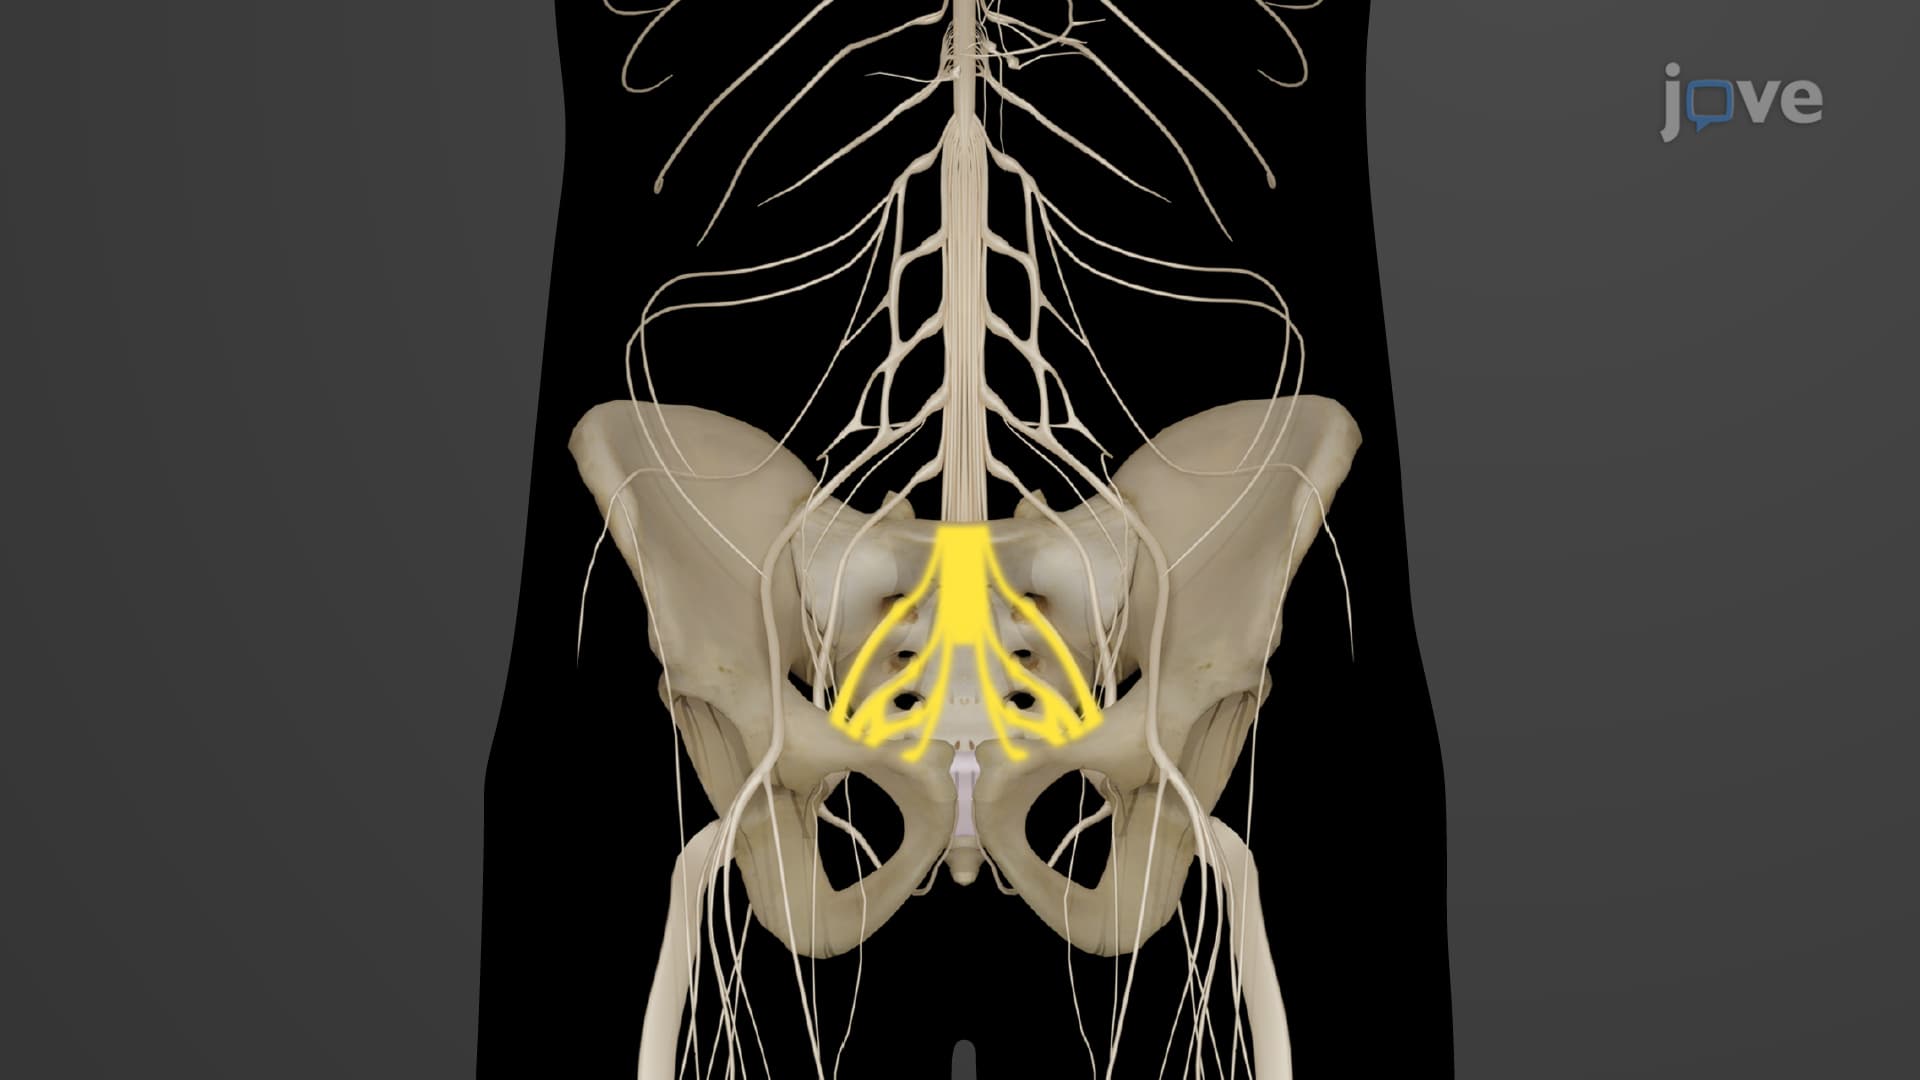
The lumbar plexus is situated within the lumbar region of the back and is primarily formed by the first four lumbar spinal nerves (L1 to L4). This plexus extends its branches into several nerves, including the...
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...