Related Experiment Video
Updated: Apr 26, 2026


A Detailed Protocol for Physiological Parameters Acquisition and Analysis in Neurosurgical Critical Patients
Published on: October 17, 2017
The effect of baseline pressure errors on an intracranial pressure-derived index: results of a prospective
Per Kristian Eide1, Angelika Sorteberg, Torstein R Meling
1Department of Neurosurgery, Oslo University Hospital, Rikshospitalet, Oslo, Norway. p.k.eide@medisin.uio.no.

Background:
In order to characterize the intracranial pressure-volume reserve capacity, the correlation coefficient (R) between the ICP wave amplitude (A) and the mean ICP level (P), the RAP index, has been used to improve the diagnostic value of ICP monitoring. Baseline pressure errors (BPEs), caused by spontaneous shifts or drifts in baseline pressure, cause erroneous readings of mean ICP. Consequently, BPEs could also affect ICP indices such as the RAP where in the mean ICP is incorporated.
Methods:
A prospective, observational study was carried out on patients with aneurysmal subarachnoid hemorrhage (aSAH) undergoing ICP monitoring as part of their surveillance. Via the same burr hole in the scull, two separate ICP sensors were placed close to each other. For each consecutive 6-sec time window, the dynamic mean ICP wave amplitude (MWA; measure of the amplitude of the single pressure waves) and the static mean ICP, were computed. The RAP index was computed as the Pearson correlation coefficient between the MWA and the mean ICP for 40 6-sec time windows, i.e. every subsequent 4-min period (method 1). We compared this approach with a method of calculating RAP using a 4-min moving window updated every 6 seconds (method 2).
Results:
The study included 16 aSAH patients. We compared 43,653 4-min RAP observations of signals 1 and 2 (method 1), and 1,727,000 6-sec RAP observations (method 2). The two methods of calculating RAP produced similar results. Differences in RAP ≥ 0.4 in at least 7% of observations were seen in 5/16 (31%) patients. Moreover, the combination of a RAP of ≥ 0.6 in one signal and <0.6 in the other was seen in ≥ 13% of RAP-observations in 4/16 (25%) patients, and in ≥ 8% in another 4/16 (25%) patients. The frequency of differences in RAP >0.2 was significantly associated with the frequency of BPEs (5 mmHg ≤ BPE <10 mmHg).
Conclusions:
Simultaneous monitoring from two separate, close-by ICP sensors reveals significant differences in RAP that correspond to the occurrence of BPEs. As differences in RAP are of magnitudes that may alter patient management, we do not advocate the use of RAP in the management of neurosurgical patients.


Related Concept Videos
 01:14
Increased Intracranial Pressure l: Introduction
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:25
Errors occurring during blood pressure monitoring
Several factors...
 01:24
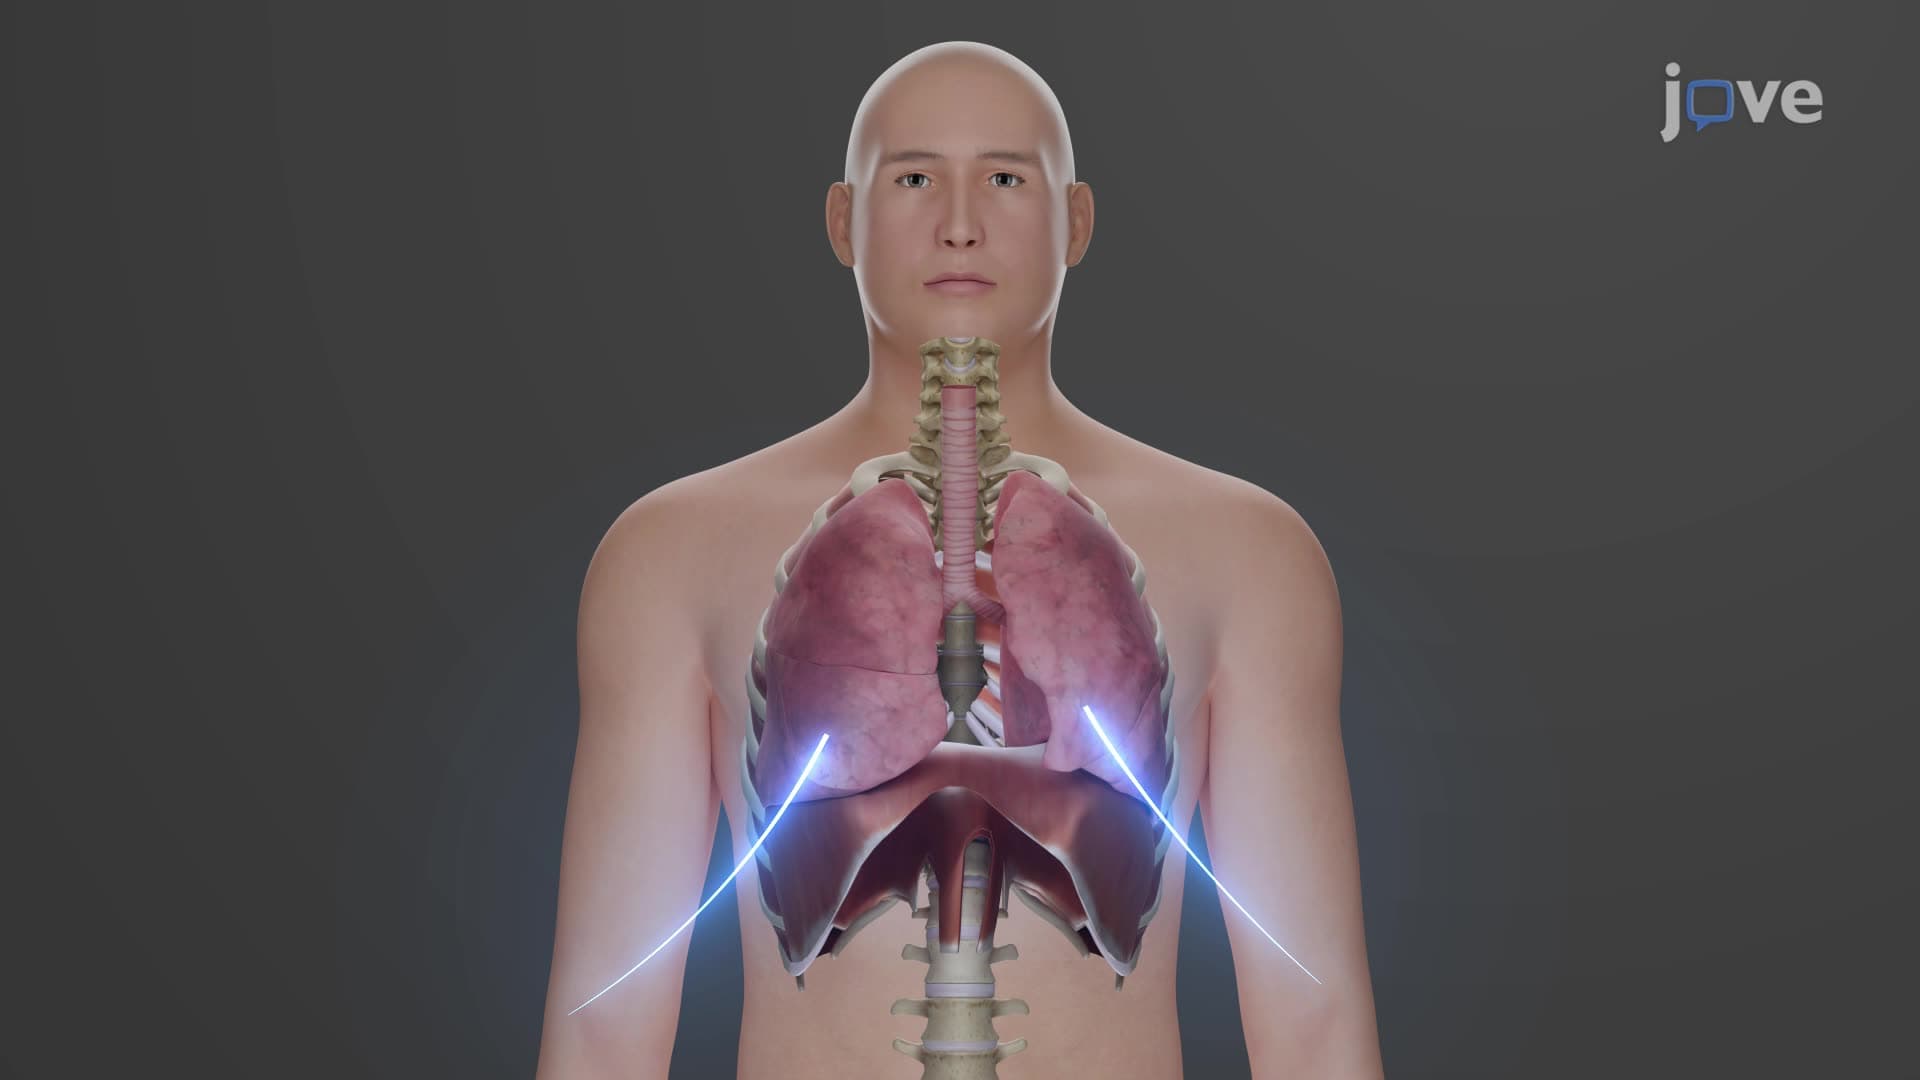
Pulmonary Ventilation: Inhalation
Boyle's law becomes particularly pertinent when examining respiratory...
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.
 01:24
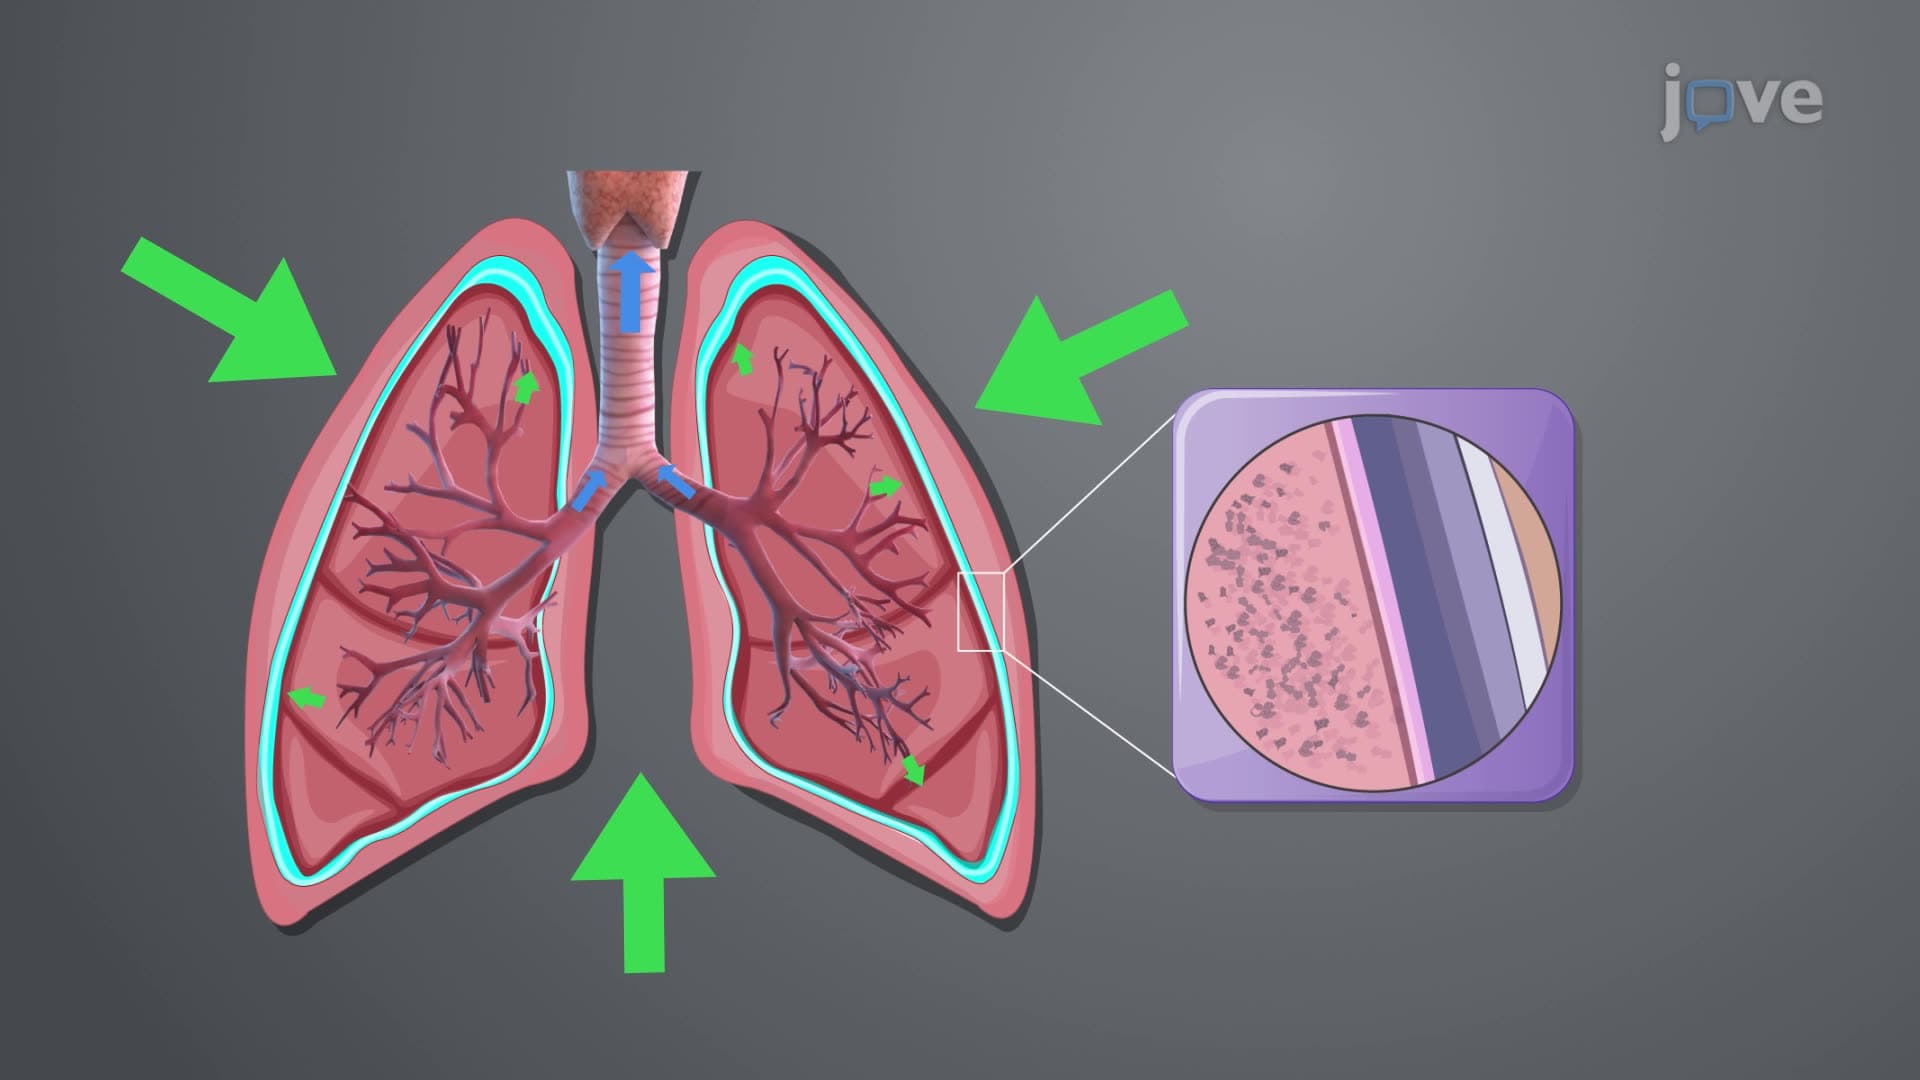
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...