Related Experiment Video
Updated: Apr 26, 2026
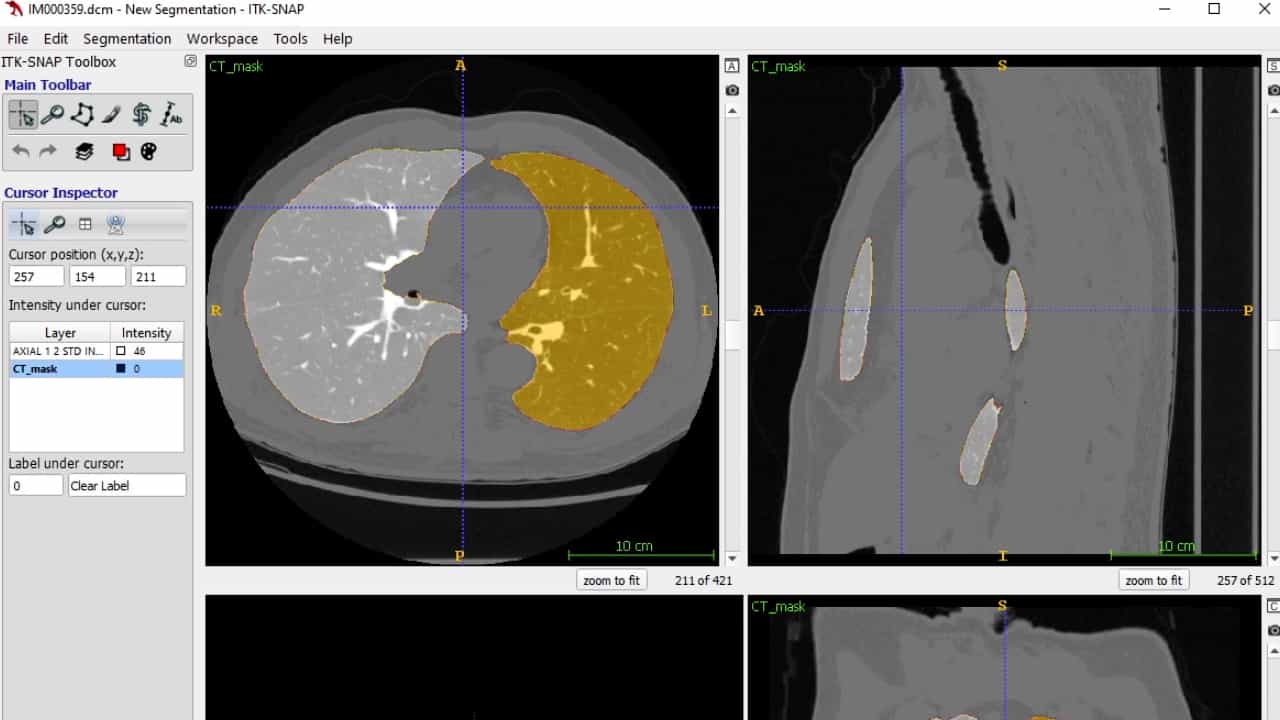

Multi-modal Pulmonary Imaging: Using Complementary Information from CT and Hyperpolarized 129Xe MRI to Evaluate Lung Structure-Function
Published on: April 12, 2024
Disproportionate contribution of right middle lobe to emphysema and gas trapping on computed tomography
Surya P Bhatt1, Jessica C Sieren2, John D Newell2
1Division of Pulmonary and Critical Care Medicine, University of Iowa, Iowa City, Iowa, United States of America.

Rationale:
Given that the diagnosis of chronic obstructive pulmonary disease (COPD) relies on demonstrating airflow limitation by spirometry, which is known to be poorly sensitive to early disease, and to regional differences in emphysema, we sought to evaluate individual lobar contributions to global spirometric measures.
Methods:
Subjects with COPD were compared with smokers without airflow obstruction, and non-smokers. Emphysema (% low attenuation area, LAAinsp<-950 HU, at end-inspiration) and gas trapping (%LAAexp<-856 HU at end-expiration) on CT were quantified using density mask analyses for the whole lung and for individual lobes, and distribution across lobes and strength of correlation with spirometry were compared.
Results:
The right middle lobe had the highest %LAAinsp<-950 HU in smokers and controls, and the highest %LAAexp<-856 HU in all three groups. While RML contributed to emphysema and gas trapping disproportionately to its relatively small size, it also showed the least correlation with spirometry. There was no change in correlation of whole lung CT metrics with spirometry when the middle lobe was excluded from analyses. Similarly, RML had the highest %LAAexp<-856 HU while having the least correlation with spirometry.
Conclusions:
Because of the right middle lobe's disproportionate contribution to CT-based emphysema measurements, and low contribution to spirometry, longitudinal studies of emphysema progression may benefit from independent analysis of the middle lobe in whole lung quantitative CT assessments. Our findings may also have implications for heterogeneity assessments and target lobe selection for lung volume reduction.
Clinical Trial Registration:
ClinicalTrials.gov NCT00608764.


Related Concept Videos
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:10
Atelectasis II: Pathophysiology
 01:24
External and Internal Respiration
 01:17
Gross Anatomy of the Lungs
 01:23
Chronic Obstructive Pulmonary Disease I: Introduction