Related Experiment Video
Updated: Apr 26, 2026


In vitro Measurements of Tracheal Constriction Using Mice
Published on: June 25, 2012
Ultrastructure of human tracheal smooth muscle from subjects with asthma and nonasthmatic subjects. Standardized
Harley T Syyong1, Chris D Pascoe, Jenny Zhang
1Departments of 1 Pathology and Laboratory Medicine.

Abstract:
A characteristic feature of asthma is exaggerated airway narrowing, termed airway hyper-responsiveness (AHR) due to contraction of airway smooth muscle (ASM). Although smooth muscle (SM)-specific asthma susceptibility genes have been identified, it is not known whether asthmatic ASM is phenotypically different from nonasthmatic ASM in terms of subcellular structure or mechanical function. The present study is the first to systematically quantify, using electron microscopy, the ultrastructure of tracheal SM from subjects with asthma and nonasthmatic subjects. Methodological details concerning tissue sample preparation, ultrastructural quantification, and normalization of isometric force by appropriate morphometric parameters are described. We reasoned that genetic and/or acquired differences in the ultrastructure of asthmatic ASM could be associated with functional changes. We recently reported that asthmatic ASM is better able to maintain and recover active force generation after length oscillations simulating deep inspirations. The present study was designed to seek structural evidence to account for this observation. Contrary to our hypotheses, no significant qualitative or quantitative differences were found in the subcellular structure of asthmatic versus nonasthmatic tracheal SM. Specifically, there were no differences in average SM cell cross-sectional area; fraction of the cell area occupied by nonfilamentous area; amounts of mitochondria, dense bodies, and dense plaques; myosin and actin filament densities; basal lamina thickness; and the number of microtubules. These results indicate that functional differences in ASM do not necessarily translate into observable structural changes.
More Related Videos
 08:59
Utilizing the Precision-Cut Lung Slice to Study the Contractile Regulation of Airway and Intrapulmonary Arterial Smooth Muscle
Published on: May 5, 2022
 09:58
A Reversible, Non-invasive Method for Airway Resistance Measurements and Bronchoalveolar Lavage Fluid Sampling in Mice
Published on: April 13, 2010
Related Concept Videos
 01:28
Asthma I: Introduction
 01:23
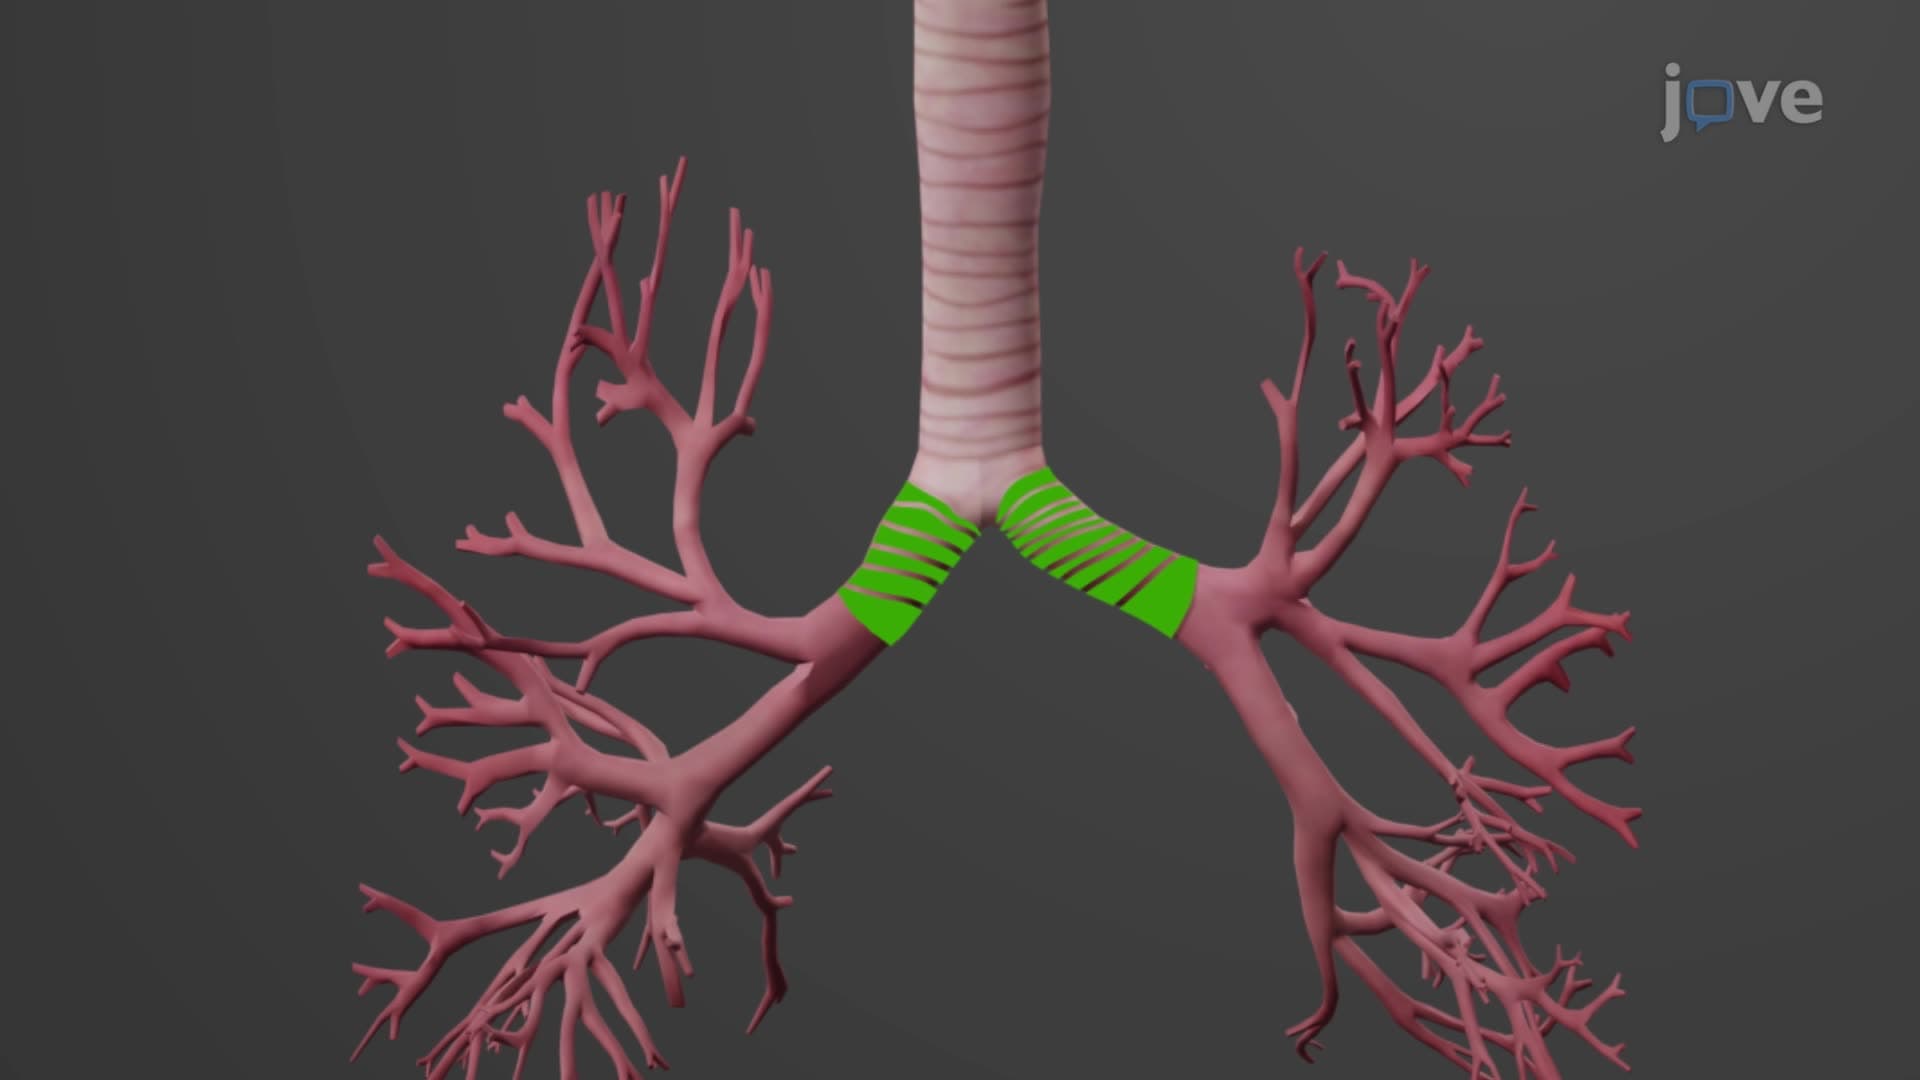
The Bronchial Tree
The trachea, commonly known as the windpipe, is a tube that connects the larynx (voice box) to the bronchi. At a point called the carina, it bifurcates into two primary bronchi. The right primary bronchus is wider, shorter, and more vertical than the left primary...
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include:
 01:31
Anatomy of Respiratory System II: Lower Respiratory Tract
The Larynx
It is located between the pharynx and the trachea, acts as a passageway for air, and hosts several critical structures, such as the epiglottis, vocal cords, and glottis. The epiglottis acts as a gateway, guiding food to the...
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of...