Related Experiment Video
Updated: Apr 26, 2026

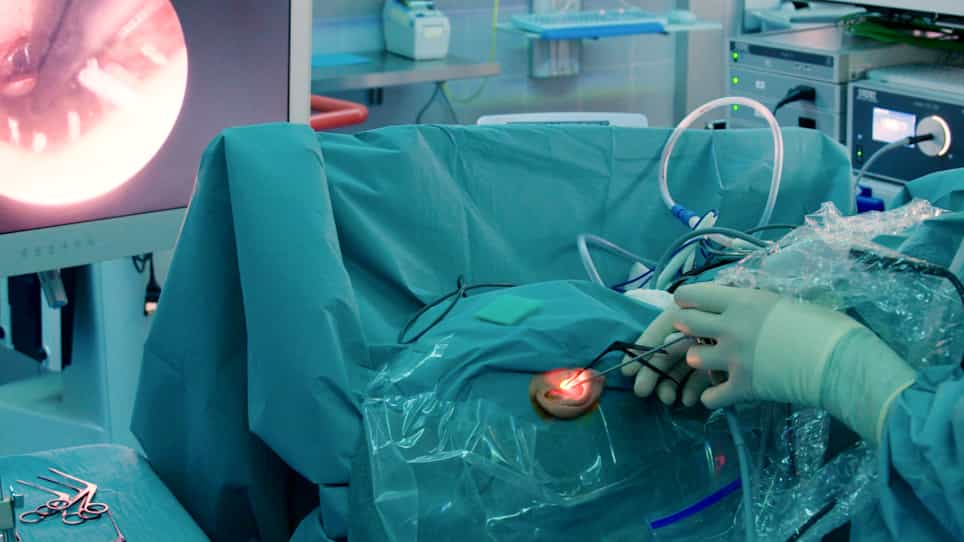
Endaural Endoscopic Atticoantrotomy Retrograde Mastoidectomy using a Constant Suction Bone-drilling Technique
Published on: May 23, 2021
Long-term results of canal wall reconstruction tympanomastoidectomy

Objectives:
This study was designed to evaluate the long-term results using the technique of canal wall reconstruction (CWR) tympanomastoidectomy with mastoid obliteration in the treatment of chronic otitis media with cholesteatoma.
Study Design:
Institutional review board-approved retrospective case review.
Setting:
Tertiary referral center.
Patients:
Retrospective review was performed on consecutive patients undergoing CWR tympanomastoidectomy with mastoid obliteration at a single institution from 1997 to 2011.
Main Outcome Measures:
Status of tympanic membrane and ear canal anatomy, preoperative and postoperative audiometry,residual cholesteatoma at second look surgery, postoperative complications, recurrence rate, and location.
Results:
Two hundred eighty-five ears in 273 patients underwent CWR tympanomastoidectomy with a mean age of 35 years with average follow-up of 4.29 years (median, 3.16 yr).A second-look ossiculoplasty was performed in 253 (89%). Recurrent retraction pocket formation occurred in 34 ears (13%). A secondary endaural atticotomy only was required to improve access for debridement in 16 of these 34 ears (5.8% of total ears).Only 7 ears (2.6%) required a revision open cavity mastoidectomy(n = 5) or subtotal petrosectomy (n = 2) for recurrent cholesteatoma. Those undergoing second-look ossiculoplasty demonstrated a small improvement in preoperative versus postoperative air-bone gap (ABG), 28 dB versus 23 dB, respectively.Postoperative infection occurred in 16 patients(5.6%) with 1 patient requiring conversion to open cavity mastoidectomy.
Conclusion:
A CWR tympanomastoidectomy provides excellent intraoperative exposure of the middle ear and mastoid without the long-term disadvantages of a canal wall down mastoidectomy. Long-term follow-up demonstrates that there were only 2.6% failures requiring conversion to an open cavity or subtotal petrosectomy.