Related Experiment Video
Updated: Apr 26, 2026
Colon Ascendens Stent Peritonitis CASP - a Standardized Model for Polymicrobial Abdominal Sepsis
Published on: December 18, 2010
Assessing the risk of decompensation by ascites and spontaneous bacterial peritonitis in cirrhosis

Aim:
The current trend is to analyze predictive factors of transition from compensated to decompensated stage by the onset of ascites and later of spontaneous bacterial peritonitis (SBP), which would make possible an early diagnosis of liver cirrhosis at the compensated stage. The aim of the study is to evaluate patients with liver cirrhosis, assessing the rate and the risk factors of decompensation by ascites and SBP.
Material And Methods:
The prospective study included patients with cirrhosis of different etiologies admitted to a ward of the Institute of Gastroenterology and Hepatology of Iaşi in the period 1st January 2010-31st December 2010, which were reassessed clinically and in laboratory for 2 years. The essential criteria for the diagnosis of SBP were the presence of > 250 PMN/mm3. Compensated cirrhosis was defined as the absence of ascites. The presence of ascites and/or upper gastrointestinal hemorrhage (UGH) marks the state of decompensated cirrhosis. To assess the severity of liver cirrhosis there were used Child-Pugh score and MELD score. Diagnostic paracentesis and ascitic fluid sampling were performed at admission to hospital and during hospitalization, in the event of signs and symptoms of SBP, after antibiotic treatment. Macroscopic, biochemical (albumin, protein), cytological (cellularity) and bacteriological (smear and culture) investigations of the ascetic fluid were performed. Lack of response to empirical treatment was considered in cases of general condition deterioration and decreased PMN < 25% of baseline.
Results:
By comparing the mean values of patients with and without SBP, it is noted that bilirubin and creatinine were significantly higher in patients with SBP, and total protein, albumin and prothrombin time were significantly lower in patients with SBP, these biochemical parameters correlate with the degree of hepatic impairment and may be considered risk factors for SBP. In relation to the mentioned elements, the most important predictors of PBS risk are low protein concentration in ascitic fluid under 1g/dl, increased levels of serum bilirubin and low platelet count. Impaired liver function, infectious complications, and previous episodes of SBP, UGH are risk factors for an episode of SBP. Empirical therapy of nosocomial SBP with third-generation cephalosporins is often inefficient due to the high prevalence of multiresistant (MR) bacteria.
Conclusions:
Assessment of clinically significant portal hypertension (PHT) and the degree of hepatic impairment may stratify patients with cirrhosis according to the risk of decompensation, making possible the identification of high risk patients. The knowledge of the risk factors in SBP is important not only to identify patients who could benefit from preventive therapy, but also in understanding the pathogenesis of the disease.
More Related Videos
 07:03
Standardized Colon Ascendens Stent Peritonitis in Rats - a Simple, Feasible Animal Model to Induce Septic Acute Kidney Injury
Published on: February 15, 2022
 04:00
Laparoscopic Splenectomy with Pericardial Devascularization for Hypersplenism and Esophageal Variceal Hemorrhage Due to Portal Hypertension
Published on: November 15, 2024
Related Concept Videos
 01:19
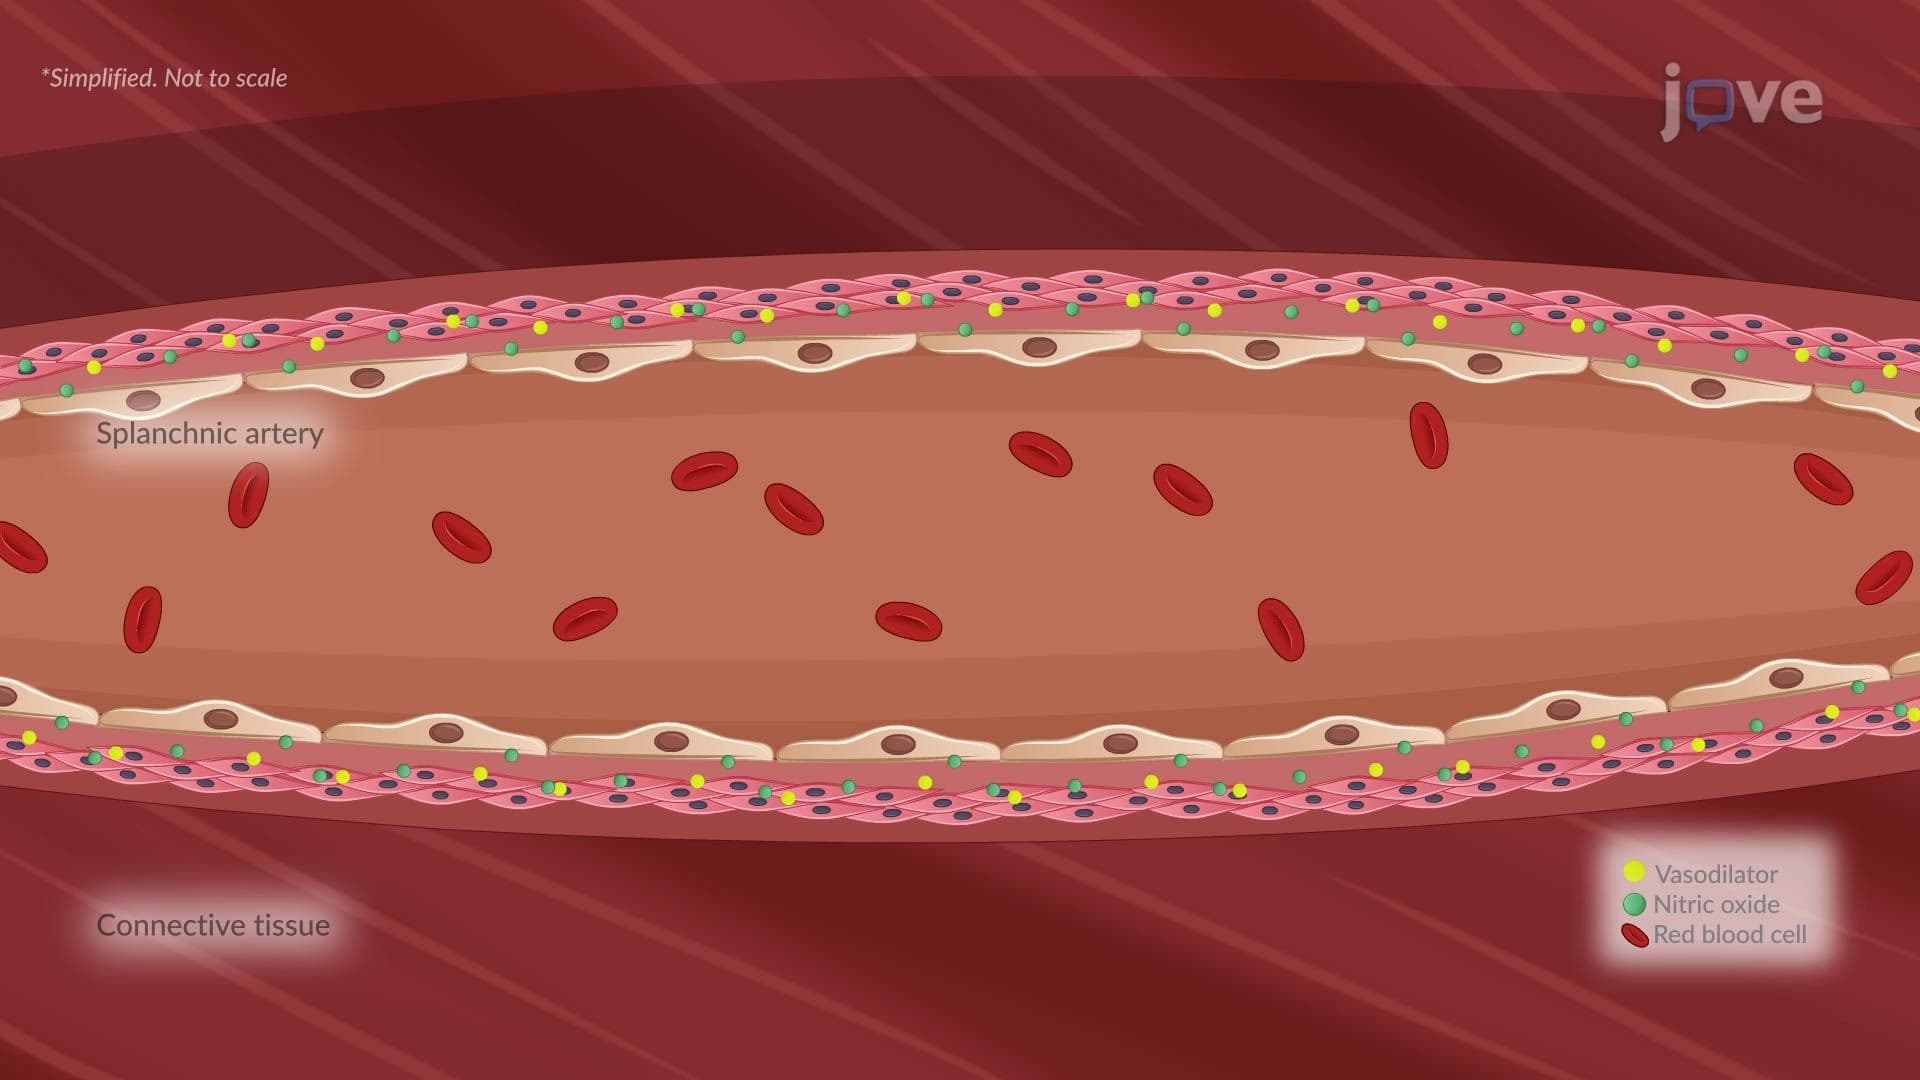
Ascites
 01:25
Peritoneal Dialysis II: Peritoneal Dialysis Systems and Complications
 01:24
Cirrhosis II: Pathophysiology
 01:21
Acute Pancreatitis II: Pathophysiology
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:21
Chronic Pancreatitis II: Pathophysiology