Related Experiment Video
Updated: Apr 26, 2026
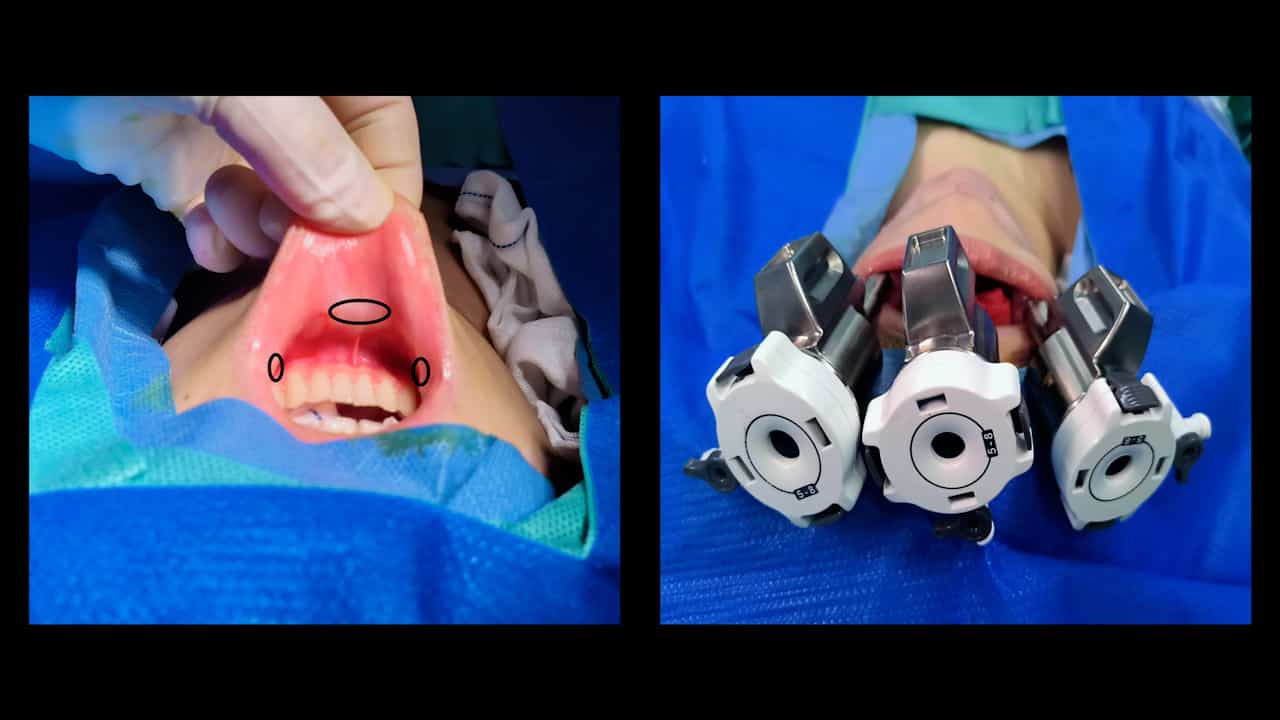

Identification and Protection of the Recurrent Laryngeal Nerve during Transoral Robotic Thyroidectomy
Published on: October 24, 2025
Neurological complications in thyroid surgery: a surgical point of view on laryngeal nerves
Emanuela Varaldo1, Gian Luca Ansaldo2, Matteo Mascherini2
1U.O. Chirurgia 1, Department of Surgery, IRCCS AOU San Martino - IST , Genoa , Italy ; Department of Surgical Sciences (DISC), University of Genoa , Genoa , Italy.

Abstract:
THE CERVICAL BRANCHES OF THE VAGUS NERVE THAT ARE PERTINENT TO ENDOCRINE SURGERY ARE THE SUPERIOR AND THE INFERIOR LARYNGEAL NERVES: their anatomical course in the neck places them at risk during thyroid surgery. The external branch of the superior laryngeal nerve (EB) is at risk during thyroid surgery because of its close anatomical relationship with the superior thyroid vessels and the superior thyroid pole region. The rate of EB injury (which leads to the paralysis of the cricothyroid muscle) varies from 0 to 58%. The identification of the EB during surgery helps avoiding both an accidental transection and an excessive stretching. When the nerve is not identified, the ligation of superior thyroid artery branches close to the thyroid gland is suggested, as well as the abstention from an indiscriminate use of energy-based devices that might damage it. The inferior laryngeal nerve (RLN) runs in the tracheoesophageal groove toward the larynx, close to the posterior aspect of the thyroid. It is the main motor nerve of the intrinsic laryngeal muscles, and also provides sensory innervation to the larynx. Its injury finally causes the paralysis of the omolateral vocal cord and various sensory alterations: the symptoms range from mild to severe hoarseness, to acute airway obstruction, and swallowing impairment. Permanent lesions of the RNL occur from 0.3 to 7% of cases, according to different factors. The surgeon must be aware of the possible anatomical variations of the nerve, which should be actively searched for and identified. Visual control and gentle dissection of RLN are imperative. The use of intraoperative nerve monitoring has been safely applied but, at the moment, its impact in the incidence of RLN injuries has not been clarified. In conclusion, despite a thorough surgical technique and the use of intraoperative neuromonitoring, the incidence of neurological complications after thyroid surgery cannot be suppressed, but should be maintained in a low range.
More Related Videos
 08:16
Intra-Operative Neural Monitoring of Thyroid Surgery in a Porcine Model
Published on: February 11, 2019
 11:46
Investigation of the Electrophysiological and Thermographic Safety Parameters of Surgical Energy Devices During Thyroid and Parathyroid Surgery in a Porcine Model
Published on: October 13, 2022
Related Concept Videos
 01:21
Larynx
Anatomy of the Larynx
The larynx consists of various components, including cartilage, muscles, and vocal cords. Its structure includes three large unpaired cartilages—the thyroid, cricoid, and epiglottis—and three smaller paired cartilages—the arytenoids,...
 01:23
The Thyroid Gland
The follicles have a central cavity lined by simple cuboidal to squamous epithelial cells called follicular cells. These cells produce the glycoprotein...
 01:27
Hyperthyroidism II: Pathophysiology
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:22
Cranial Nerves: Types Part II
Facial Nerve (Cranial Nerve VII)
Cranial nerve VII, or the facial nerve,...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...