Related Experiment Video
Updated: Apr 26, 2026
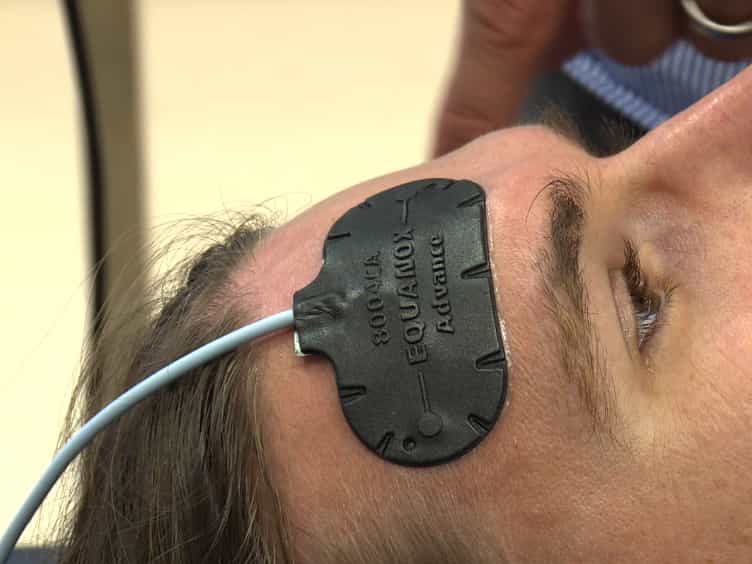

A Model to Simulate Clinically Relevant Hypoxia in Humans
Published on: December 22, 2016
Effects of hyperoxia and hypoxia on the physiological traits responsible for obstructive sleep apnoea
Bradley A Edwards1, Scott A Sands2, Robert L Owens2
1Division of Sleep Medicine, Brigham and Women's Hospital, Harvard Medical School, Boston, MA, USA baedwards@partners.org.

Abstract:
Oxygen therapy is known to reduce loop gain (LG) in patients with obstructive sleep apnoea (OSA), yet its effects on the other traits responsible for OSA remain unknown. Therefore, we assessed how hyperoxia and hypoxia alter four physiological traits in OSA patients. Eleven OSA subjects underwent a night of polysomnography during which the physiological traits were measured using multiple 3-min 'drops' from therapeutic continuous positive airway pressure (CPAP) levels. LG was defined as the ratio of the ventilatory overshoot to the preceding reduction in ventilation. Pharyngeal collapsibility was quantified as the ventilation at CPAP of 0 cmH2O. Upper airway responsiveness was defined as the ratio of the increase in ventilation to the increase in ventilatory drive across the drop. Arousal threshold was estimated as the level of ventilatory drive associated with arousal. On separate nights, subjects were submitted to hyperoxia (n = 9; FiO2 ∼0.5) or hypoxia (n = 10; FiO2 ∼0.15) and the four traits were reassessed. Hyperoxia lowered LG from a median of 3.4 [interquartile range (IQR): 2.6-4.1] to 2.1 (IQR: 1.3-2.5) (P < 0.01), but did not alter the remaining traits. By contrast, hypoxia increased LG [median: 3.3 (IQR: 2.3-4.0) vs. 6.4 (IQR: 4.5-9.7); P < 0.005]. Hypoxia additionally increased the arousal threshold (mean ± s.d. 10.9 ± 2.1 l min(-1) vs. 13.3 ± 4.3 l min(-1); P < 0.05) and improved pharyngeal collapsibility (mean ± s.d. 3.4 ± 1.4 l min(-1) vs. 4.9 ± 1.3 l min(-1); P < 0.05), but did not alter upper airway responsiveness (P = 0.7). This study demonstrates that the beneficial effect of hyperoxia on the severity of OSA is primarily based on its ability to reduce LG. The effects of hypoxia described above may explain the disappearance of OSA and the emergence of central sleep apnoea in conditions such as high altitude.
More Related Videos
 05:45
Delivery of In Vivo Acute Intermittent Hypoxia in Neonatal Rodents to Prime Subventricular Zone-derived Neural Progenitor Cell Cultures
Published on: November 2, 2015
 04:53
Author Spotlight: Traditional Chinese Medicine for Sleep Disorders in Acute COPD — A Safe, Cost-Effective Approach
Published on: October 18, 2024
Related Concept Videos
 01:21
Sleep Apnea
The condition is more prevalent among...
 01:23
Hypoxia
Types of Hypoxia
There are four primary types of hypoxia, each resulting from a different cause:
1. Anemic hypoxia: This type occurs due to insufficient oxygen delivery caused by a lack of red blood cells (RBCs) or RBCs with abnormal or...
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:25
Hyperpnea and Hyperventilation
 01:19
Respiratory Assessment: Purpose and Indications
Objectives and Importance:
The primary goal of respiratory assessment is to evaluate patients at early risk of clinical deterioration. Since respiratory distress often precedes other signs of declining health, breathing patterns and sounds become a...