Related Experiment Video
Updated: Apr 26, 2026

Isolation of Glomeruli and In Vivo Labeling of Glomerular Cell Surface Proteins
Published on: January 18, 2019
Comparison of double filtration plasmapheresis with immunoadsorption therapy in patients with anti-glomerular
Yi-yan Zhang, Zheng Tang1, Dong-mei Chen
1National Clinical Research Center of Kidney Diseases, Jinling Hospital, Nanjing University School of Medicine, Nanjing 210002, P, R, China. tang_dr@163.com.

Background:
Double filtration plasmapheresis (DFPP) and (IA) are both used to clear antibody. However, the clinical efficacy and safety of DFPP in patients with anti-glomerular basement membrane (anti-GBM) disease are unclear.
Methods:
The 28 enrolled patients diagnosed serologically and pathologically with anti-GBM disease from 2003 to 2013 included 16 treated with DFPP and 12 with IA, with all patients administered immunosuppressive agents. DFPP consisted of an EC50W filter for plasma separation and an EC20W filter for plasma fractionation. A double volume of plasma was processed, and each patient received a 30-40 g human albumin supplement during each session. IA consisted of 10 cycles per session, with 8-10 sessions performed daily or every other day and each session regenerating 30-60 L of plasma. Serum anti-GBM antibodies and IgG were measured, and urinary and blood tests were performed, before and after each procedure. Renal function and outcome were determined.
Results:
The 28 patients consisted of 13 males and 15 females, of median age 44.5 years (range, 22.5-57 years). Six patients had pulmonary hemorrhage and 18 had serum creatinine concentrations >500 umol/L. The average serum creatinine concentration at early onset of disease was 525 umol/L while the peak concentration was 813 umol/L. All patients showed progressive increases in serum creatinine and required CRRT during the course of disease. Pathological examination showed an average 73.9% of crescents (range, 54.6-95.4%).The clinical and pathological features of the DPPP and IA groups were similar. Efficacy of clearing anti-GBM antibody was similar in the two groups (59.0 vs. 71.2%, P = 1.00), although fewer patients in the DFPP group experienced reduced IgG (62.7 vs. 83.5%, p = 0.002). One patient each had a pulmonary hemorrhage and a subcutaneous hemorrhage during treatment, but there were no other serious complications. At the end of follow-up, patient survival and renal survival were similar in the DFPP and IA groups.
Conclusion:
DPPP plus immunosuppressive therapy efficiently and safely removed anti-GBM antibodies. The fewer plasma-associated side effects and reduced loss of IgG suggest that DFPP may be a better treatment choice for anti-GBM disease, especially in patients with insufficient plasma.


Related Concept Videos
 01:25
Extracorporeal Removal of Drugs: Hemoperfusion and Hemofiltration
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:15
Glomerular Filtration
Components of the Filtration Membrane
The filtration process involves three key layers: the glomerular endothelial cells, the basement membrane, and the podocyte-formed filtration slits.
 01:02
Renal Drug Excretion: Glomerular Filtration
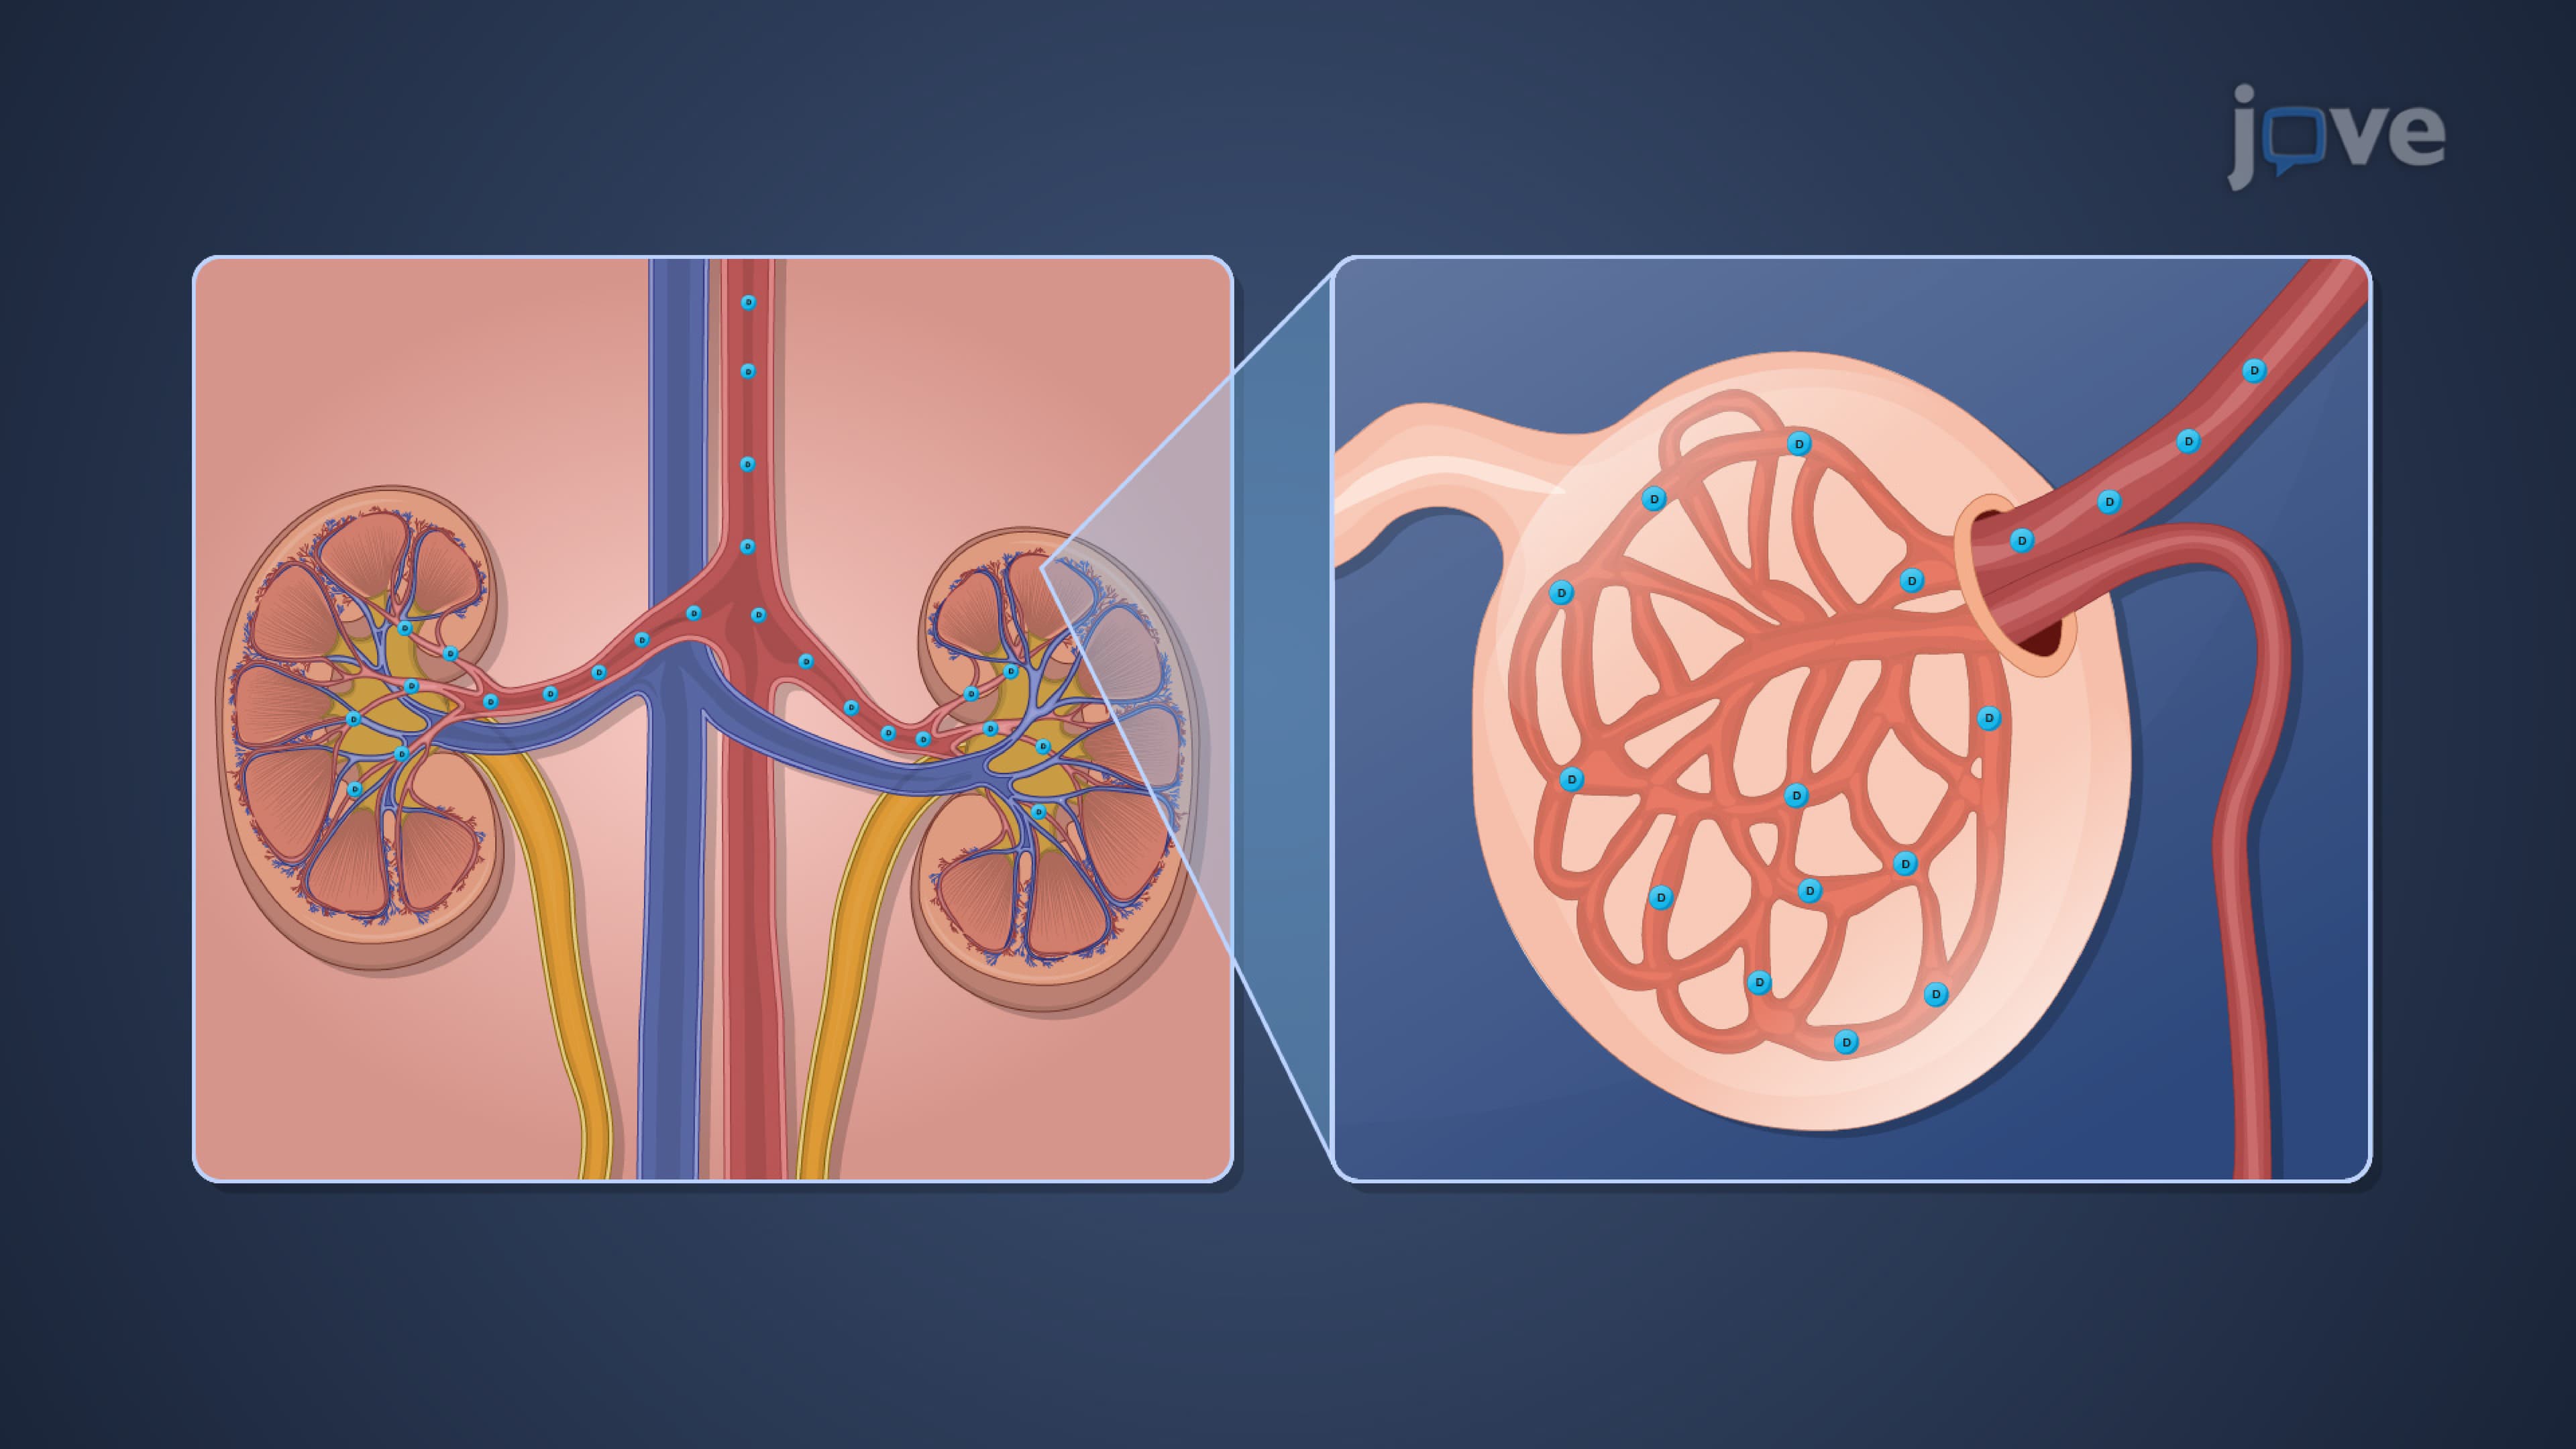
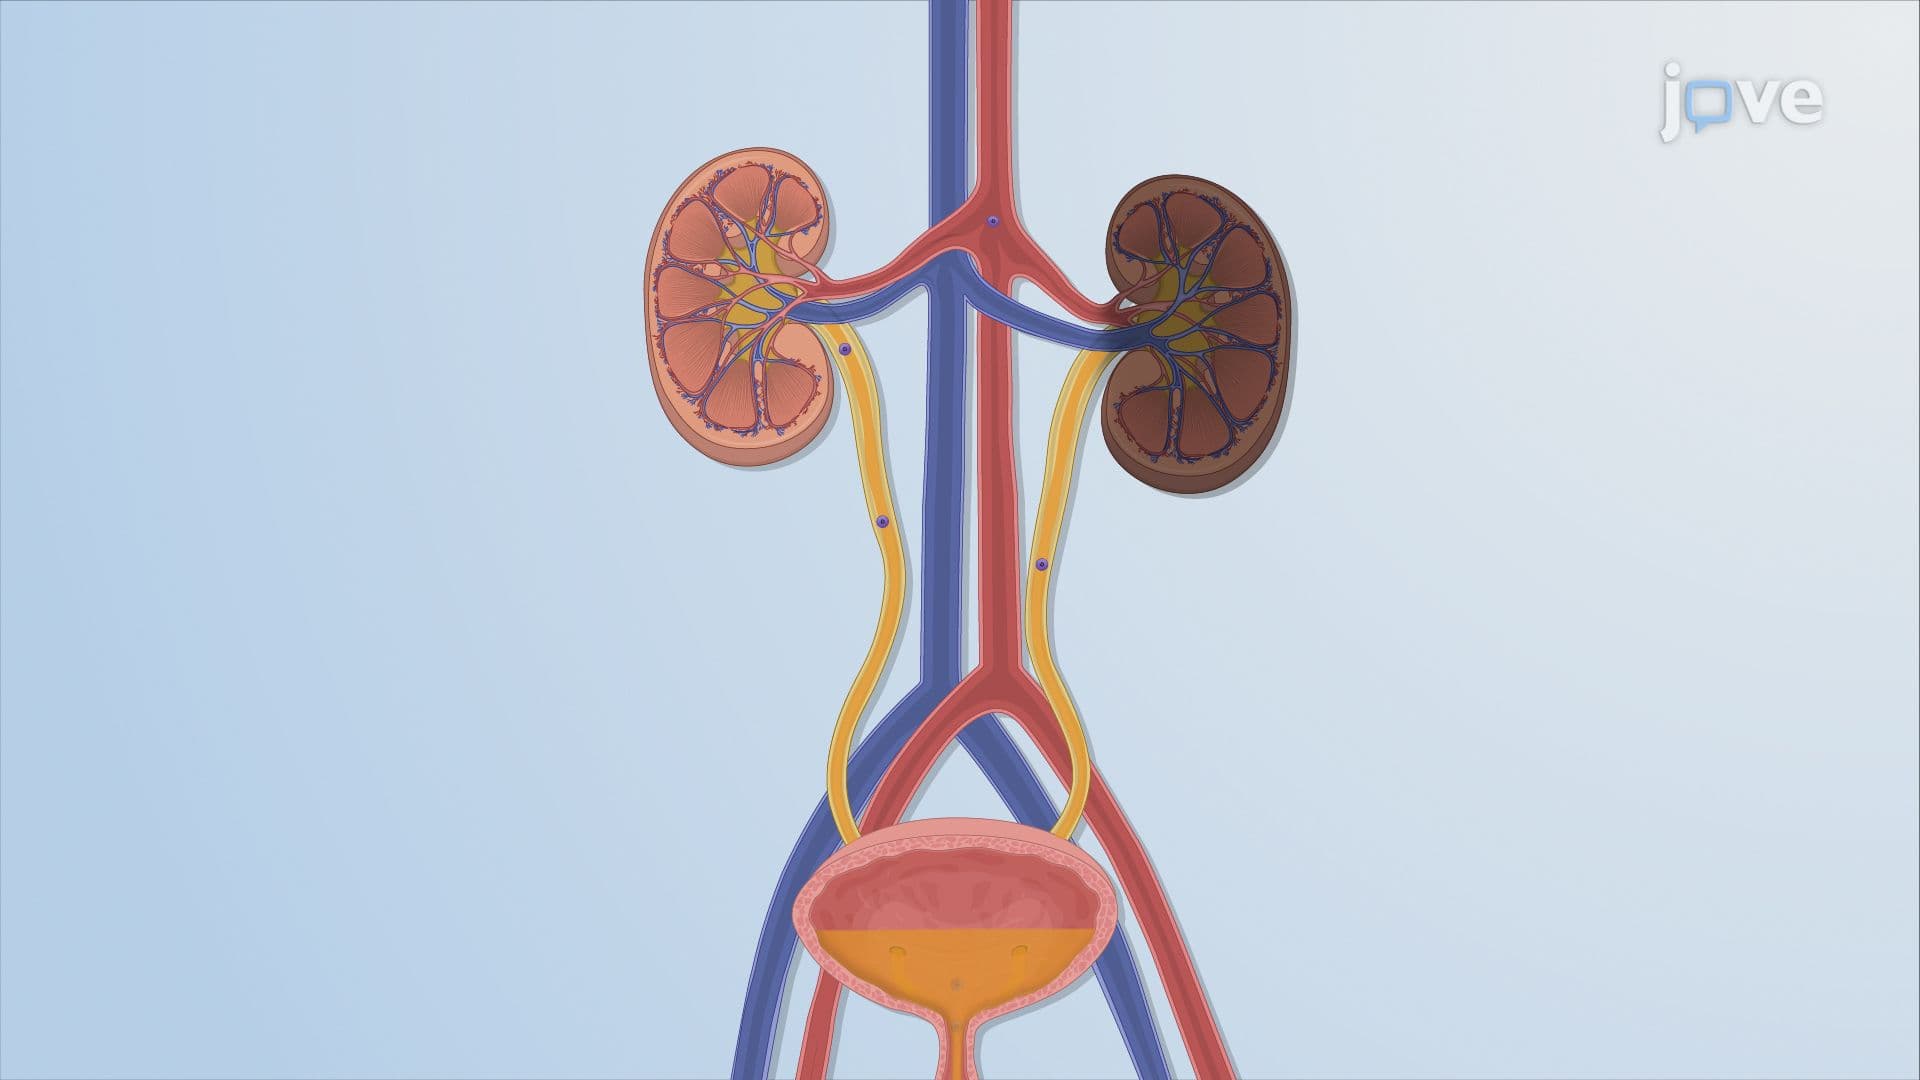
Drugs gain access to the kidney via the renal artery, which progressively branches off into afferent arterioles....
 01:25
Drug Dosing in Renal Diseases: Measurement of Glomerular Filtration Rate
 01:08
Renal Drug Clearance: Comparison Between Renal Excretion Methods
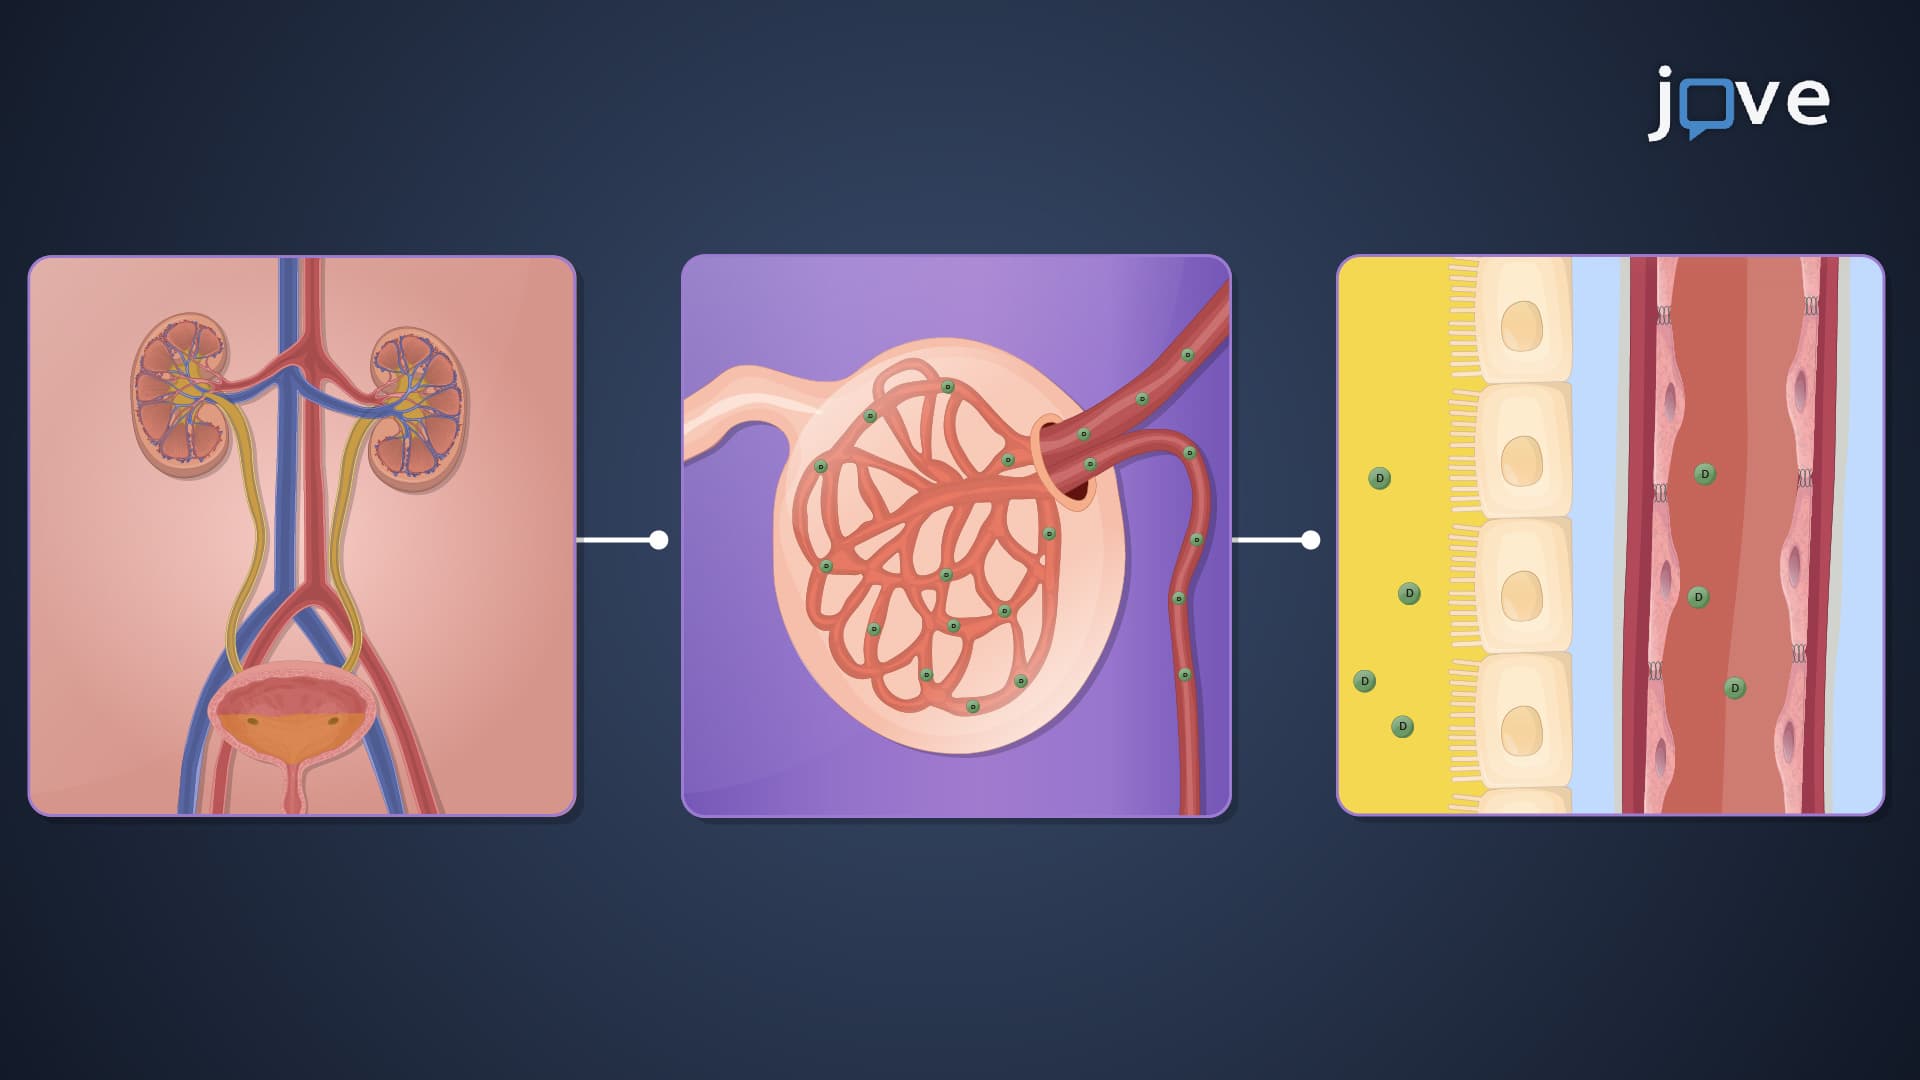
Renal clearance is often associated with the renal glomerular filtration rate (GFR), which represents the rate at which plasma is filtered through the glomeruli in the kidney. When drug reabsorption is minimal and there is no active secretion, renal clearance is closely related to the...