Related Experiment Video
Updated: Apr 26, 2026


Assessment of Vascular Function in Patients With Chronic Kidney Disease
Published on: June 16, 2014
Observational modeling of strict vs conventional blood pressure control in patients with chronic kidney disease
Csaba P Kovesdy1, Jun L Lu2, Miklos Z Molnar2
1Division of Nephrology, Memphis VA Medical Center, Memphis, Tennessee2Division of Nephrology, University of Tennessee Health Science Center, Memphis.

Insights
Strictly controlling systolic blood pressure (SBP) below 120 mm Hg in patients with chronic kidney disease (CKD) was linked to increased mortality. Current guidelines recommend SBP below 140 mm Hg for CKD patients.
Area of Science:
- Nephrology
- Cardiology
- Public Health
Background:
- The optimal systolic blood pressure (SBP) target for patients with chronic kidney disease (CKD) remains a critical clinical question.
- Current guidelines suggest a target SBP below 140 mm Hg, but the impact of stricter control is not fully understood.
Purpose of the Study:
- To investigate the association between a treated SBP target of less than 120 mm Hg versus less than 140 mm Hg and clinical outcomes in US veterans with CKD.
- To evaluate the impact of intensive blood pressure management on all-cause mortality in this population.
Main Methods:
- A historical cohort study was conducted using a national database of US veterans diagnosed with CKD and uncontrolled hypertension.
- Propensity scores were utilized to adjust for confounding factors in comparing outcomes between patients with SBP < 120 mm Hg and those with SBP 120-139 mm Hg.
- All-cause mortality was assessed using log-rank tests and propensity score-adjusted Cox models.
Main Results:
- The study included 77,765 CKD patients, with 5,760 achieving SBP < 120 mm Hg and 72,005 having SBP 120-139 mm Hg.
- Over a median follow-up of 6.0 years, a significantly higher all-cause mortality rate was observed in the SBP < 120 mm Hg group (80.9/1000 patient-years) compared to the SBP 120-139 mm Hg group (41.8/1000 patient-years).
- The adjusted hazard ratio for mortality in the SBP < 120 mm Hg group was 1.70 (95% CI, 1.63-1.78), indicating a 70% increased risk.
Conclusions:
- Stricter systolic blood pressure control (SBP < 120 mm Hg) is associated with increased all-cause mortality in patients with chronic kidney disease.
- These findings underscore the need for careful consideration of blood pressure targets in CKD management.
- Further validation through ongoing clinical trials is recommended to confirm these observational findings and inform treatment strategies.
Importance:
The effect of strict blood pressure control on clinical outcomes in patients with chronic kidney disease (CKD) is unclear.
Objective:
To compare the outcomes associated with a treated systolic blood pressure (SBP) of less than 120 mm Hg vs those associated with the currently recommended SBP of less than 140 mm Hg in a national CKD database of US veterans.
Design, Setting, And Participants:
Historical cohort study using a nationwide cohort of US veterans with prevalent CKD, estimated glomerular filtration rate less than 60 mL/min/1.73 m(2), and uncontrolled hypertension, who then received 1 or more additional blood pressure medications with evidence of a decrease in SBP. Propensity scores were calculated to reflect each individual's probability for future SBP less than 120 vs 120 to 139 mm Hg.
Main Outcomes And Measures:
The effect of SBP on all-cause mortality was evaluated by the log-rank test, and in Cox models adjusted for propensity scores.
Results:
Using a database of 651,749 patients with CKD, we identified 77,765 individuals meeting the inclusion criteria. A total of 5760 patients experienced follow-up treated SBP of less than 120 mm Hg and 72,005 patients had SBP of 120 to 139 mm Hg. During a median follow-up of 6.0 years, 19,517 patients died, with 2380 deaths in the SBP less than 120 mm Hg group (death rate, 80.9/1000 patient-years [95% CI, 77.7-84.2/1000 patient-years]) and 17,137 deaths in the SBP 120 to 139 mm Hg group (death rate, 41.8/1000 patient-years [95% CI, 41.2-42.4/1000 patient-years]; P < .001). The mortality hazard ratio (95% CI) associated with follow-up SBP less than 120 vs 120 to 139 mm Hg was 1.70 (1.63-1.78) after adjustment for propensity scores.
Conclusions And Relevance:
Our results suggest that stricter SBP control is associated with higher all-cause mortality in patients with CKD. Confirmation of these findings by ongoing clinical trials would suggest that modeling of therapeutic interventions in observational cohorts may offer useful guidance for the treatment of conditions that lack clinical trial data.
More Related Videos

Related Concept Videos
 01:18
Hypertension and Regulation of Blood Pressure
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:18
Chronic Kidney Disease IV: Nursing Management
 01:25
Chronic Kidney Disease I: Introduction
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:30
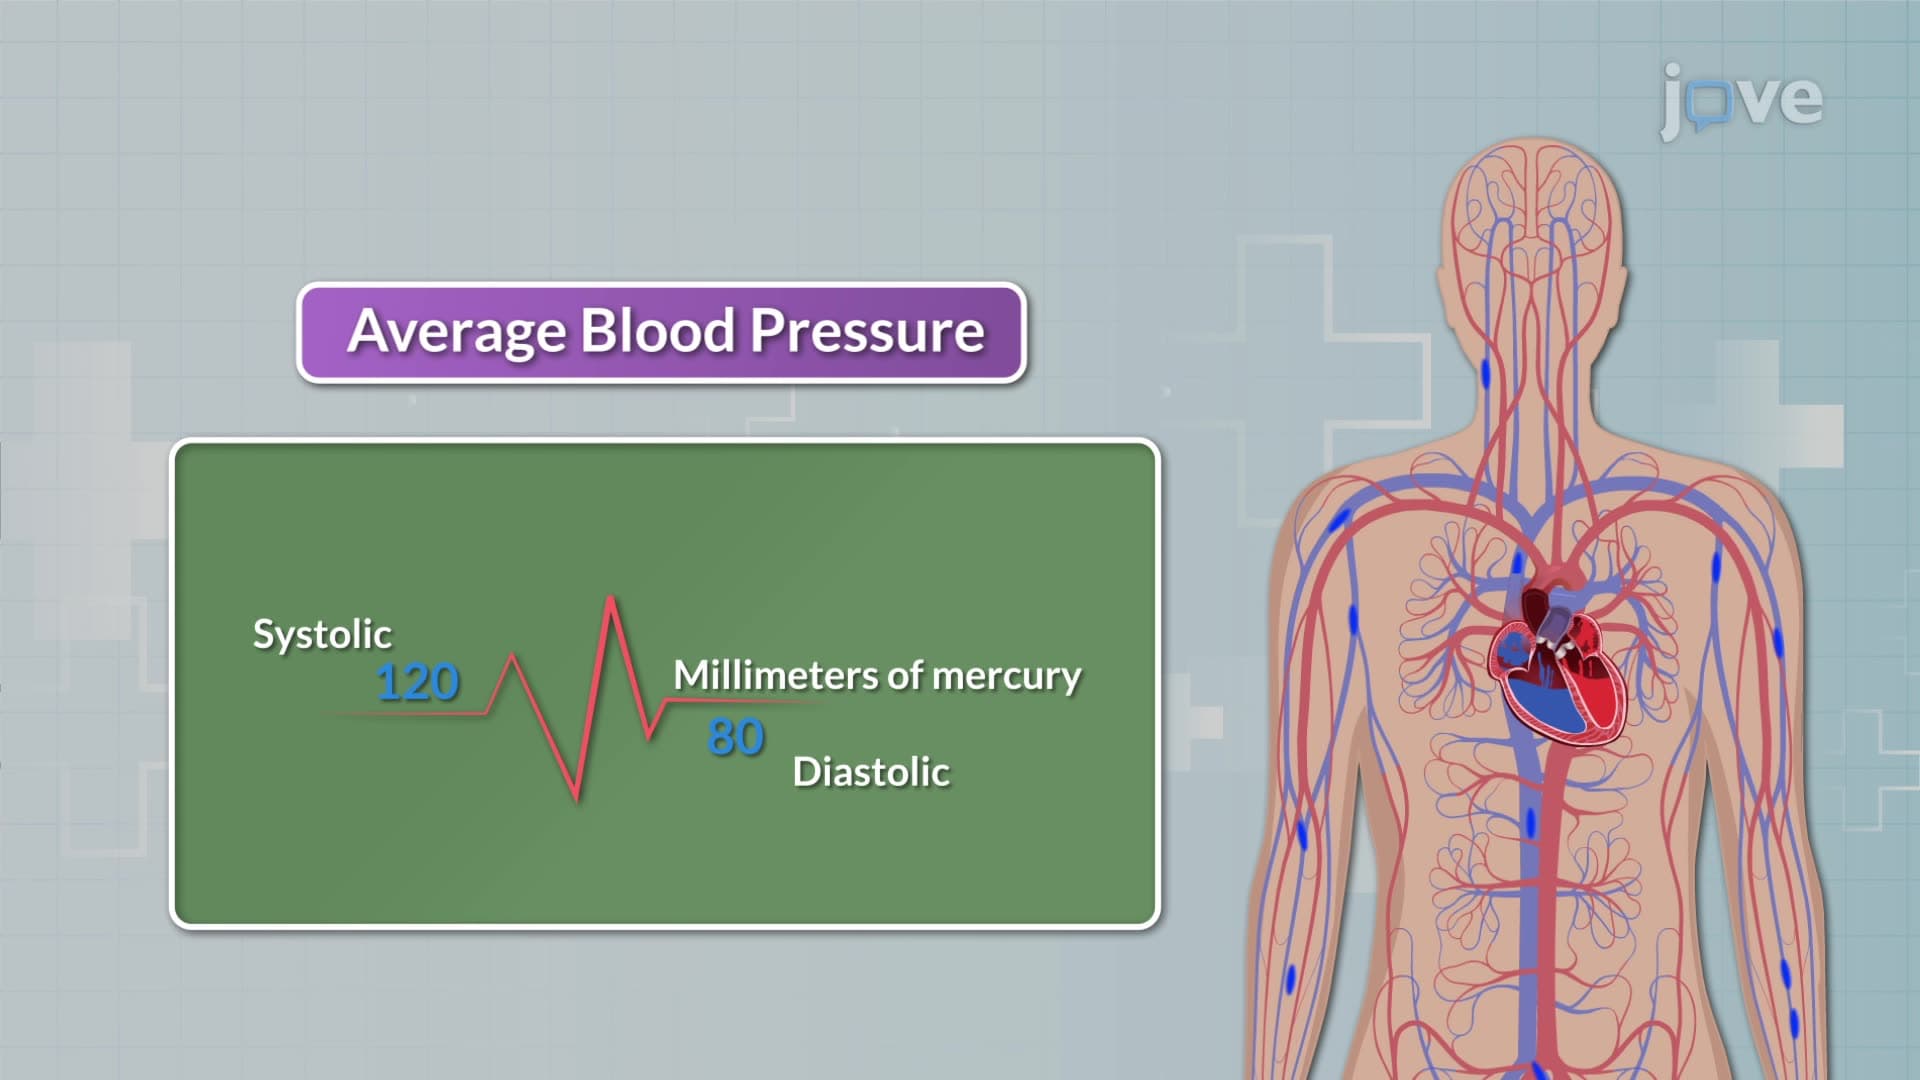
Blood Pressure
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the...