Related Experiment Video
Updated: Apr 26, 2026

Murine Fetal Echocardiography
Published on: February 15, 2013
Fetal syringomyelia

Insights
Fetal syringomyelia, often seen in Chiari II malformations and other spinal dysraphisms, can develop early in gestation. It results from primary malformations and secondary in-utero injury, differing from post-natal cases.
Area of Science:
- Neuroscience
- Developmental Biology
- Pediatric Pathology
Background:
- Syringomyelia is a complex spinal cord condition.
- Fetal spinal dysraphism and hindbrain crowding are associated with neurological abnormalities.
- Understanding the origins of fetal syringomyelia is crucial for diagnosis and management.
Purpose of the Study:
- To determine the prevalence of syringomyelia in fetuses with dysraphism and hindbrain crowding.
- To characterize the anatomical features and potential causes of fetal syringomyelia.
- To differentiate fetal syringomyelia from post-natal forms.
Main Methods:
- Retrospective analysis of 113 fetal cases (17.5–34 weeks gestation).
- Examination of cases with Chiari II malformations, OEIS, Meckel Gruber syndrome, and conjoined twins.
- Histopathological assessment for secondary injury markers like vernicomyelia and hemorrhage.
Main Results:
- Syringomyelia was identified in 13 cases of Chiari II malformations, 5 OEIS cases, 2 Meckel Gruber syndrome cases, and 1 conjoined twin pair.
- Secondary injuries (vernicomyelia, infarct-like histology, hemorrhage) were observed in 8 cases.
- Syringes were typically distinct from the central canal, located dorsally/paramedially, and extended proximally or distally from dysraphic sites.
Conclusions:
- Fetal syringomyelia in Chiari II malformations and dysraphic states often forms before midgestation.
- Both primary malformation and secondary in-utero injury contribute to its development.
- Fetal syringomyelia is anatomically and pathophysiologically distinct from post-natal syringomyelia secondary to hindbrain crowding.
Abstract:
We explored the prevalence of syringomyelia in a series of 113 cases of fetal dysraphism and hindbrain crowding, of gestational age ranging from 17.5 to 34 weeks with the vast majority less than 26 weeks gestational age. We found syringomyelia in 13 cases of Chiari II malformations, 5 cases of Omphalocele/Exostrophy/Imperforate anus/Spinal abnormality (OEIS), 2 cases of Meckel Gruber syndrome and in a single pair of pyopagus conjoined twins. Secondary injury was not uncommon, with vernicomyelia in Chiari malformations, infarct like histology, or old hemorrhage in 8 cases of syringomyelia. Vernicomyelia did not occur in the absence of syrinx formation. The syringes extended from the sites of dysraphism, in ascending or descending patterns. The syringes were usually in a major proportion anatomically distinct from a dilated or denuded central canal and tended to be dorsal and paramedian or median. We suggest that fetal syringomyelia in Chiari II malformation and other dysraphic states is often established prior to midgestation, has contributions from the primary malformation as well as from secondary in utero injury and is anatomically and pathophysiologically distinct from post natal syringomyelia secondary to hindbrain crowding.


Related Concept Videos
 01:07
Teratogenicity
 01:30
Neurulation
 01:14
Fetal Circulation
Two umbilical arteries transport blood from the fetus to the placenta. At the placenta, the blood absorbs oxygen and nutrients while simultaneously eliminating waste products. This oxygen-enriched and nutrient-rich blood then returns to the fetus through one...
 02:57
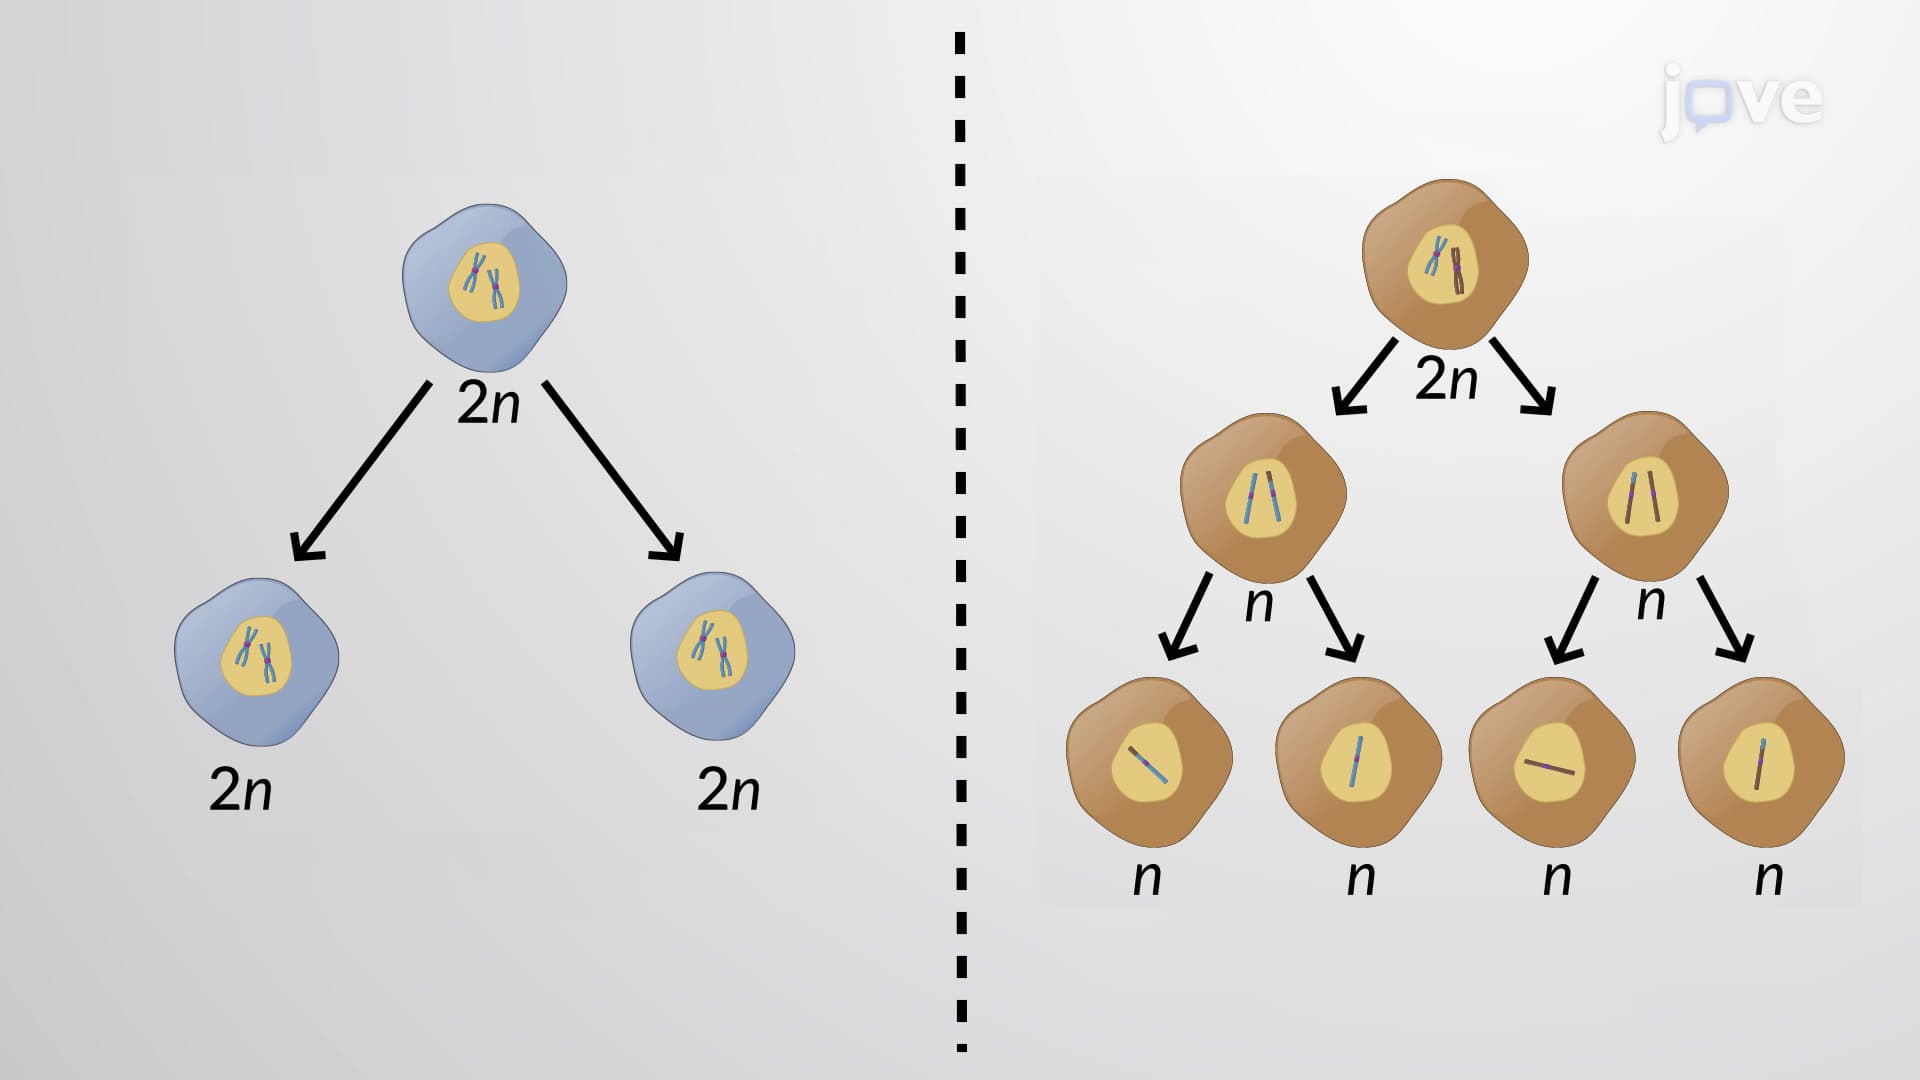
Meiosis vs. Mitosis
Before the start of mitosis and meiosis I, the cell synthesizes DNA, resulting in two homologous copies of each chromosome. DNA synthesis is...
 01:19
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...