Increased neutrophil elastase and proteinase 3 and augmented NETosis are closely associated with β-cell autoimmunity in patients with type 1 diabetes
Related Experiment Video
Updated: Apr 26, 2026
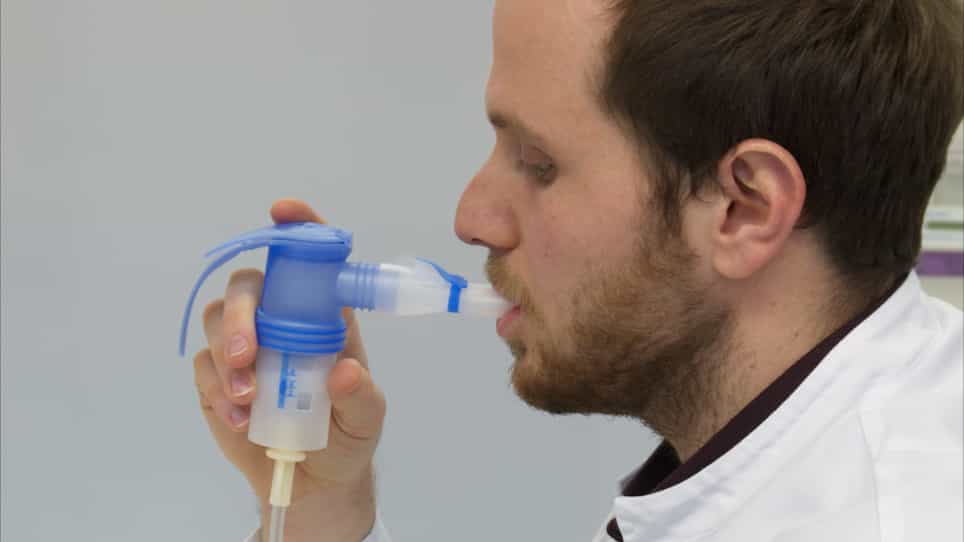
Monitoring Neutrophil Elastase and Cathepsin G Activity in Human Sputum Samples
Published on: May 21, 2021
Yudong Wang1, Yang Xiao2, Ling Zhong1
1State Key Laboratory of Pharmaceutical Biotechnology, The University of Hong Kong, Hong Kong, China Department of Medicine, The University of Hong Kong, Hong Kong, China.

Abstract:
Type 1 diabetes (T1D) is an autoimmune disease resulting from the self-destruction of insulin-producing β-cells. Reduced neutrophil counts have been observed in patients with T1D. However, the pathological roles of neutrophils in the development of T1D remain unknown. Here we show that circulating protein levels and enzymatic activities of neutrophil elastase (NE) and proteinase 3 (PR3), both of which are neutrophil serine proteases stored in neutrophil primary granules, were markedly elevated in patients with T1D, especially those with disease duration of less than 1 year. Furthermore, circulating NE and PR3 levels increased progressively with the increase of the positive numbers and titers of the autoantibodies against β-cell antigens. An obvious elevation of NE and PR3 was detected even in those autoantibody-negative patients. Increased NE and PR3 in T1D patients are closely associated with elevated formation of neutrophil extracellular traps. By contrast, the circulating levels of α1-antitrypsin, an endogenous inhibitor of neutrophil serine proteases, are decreased in T1D patients. These findings support an early role of neutrophil activation and augmented neutrophil serine proteases activities in the pathogenesis of β-cell autoimmunity and also suggest that circulating NE and PR3 may serve as sensitive biomarkers for the diagnosis of T1D.

Related Concept Videos
 01:26
Type I Diabetes II: Pathophysiology
 01:12
Type I Diabetes I: Introduction
 01:21
Acute Pancreatitis II: Pathophysiology
 01:19
Type I Diabetes III: Clinical Manifestations
 01:05
Insulin Secretory Vesicles
 01:26
Type II Diabetes I: Introduction