Related Experiment Video
Updated: Apr 26, 2026

Vessel-sparing Excision and Primary Anastomosis
Published on: January 7, 2019
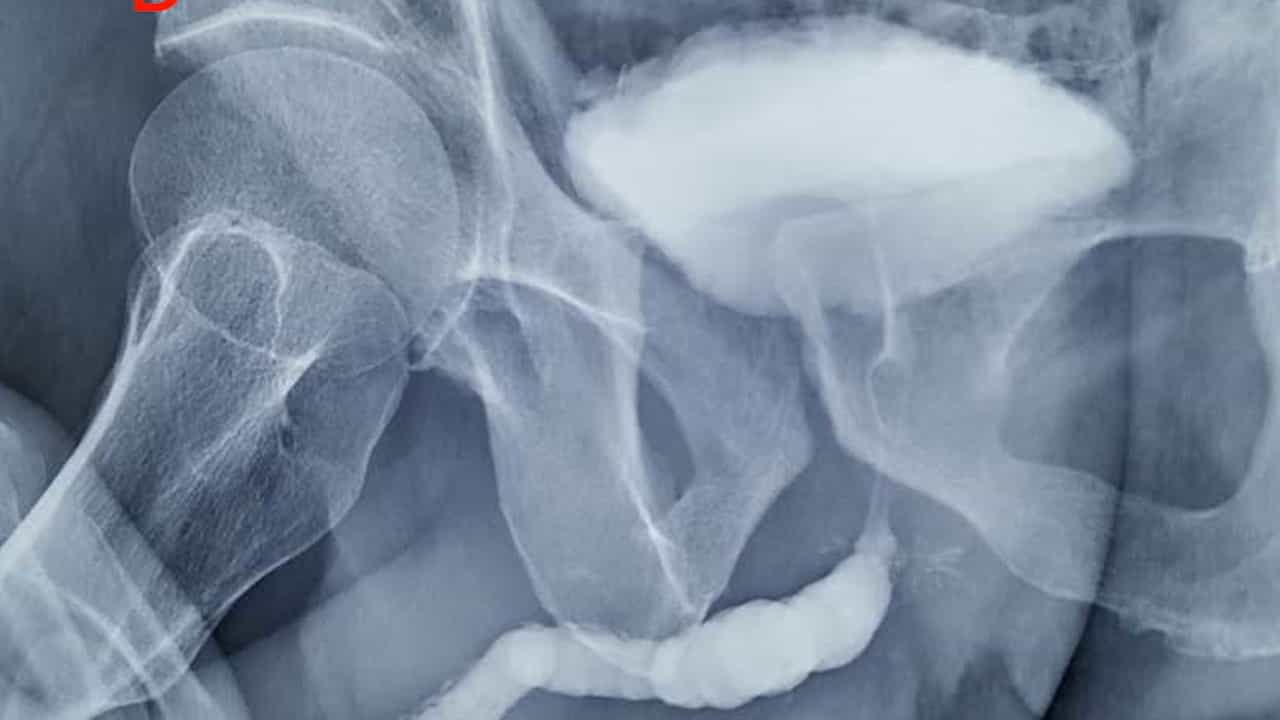
Surgical management of complex rectourethral fistulas in irradiated and nonirradiated patients
Jennifer M Hanna1, Ryan Turley, Anthony Castleberry
11Department of Surgery, Section of Colon and Rectal Surgery, Duke University Medical Center, Durham, North Carolina 2Department of Anesthesiology, Duke University Medical Center, Durham, North Carolina 3Division of Urology, Duke University Medical Center, Durham, North Carolina.

Background:
Rectourethral fistulas are an uncommon, yet devastating occurrence after treatment for prostate cancer or trauma, and their surgical management has historically been nonstandardized. Anecdotally, irradiated rectourethral fistulas portend a worse prognosis.
Objective:
To review outcomes after surgical treatment of rectourethral fistulas in radiated and nonirradiated patients to construct a logical surgical algorithm.
Design And Setting:
A retrospective review was undertaken of all patients presenting to Duke University with the diagnosis of rectourethral fistula from 1996 to 2012.
Patients:
Thirty-seven patients presented with and were treated for rectourethral fistulas: 21 received radiation, and a rectourethral fistula from trauma or iatrogenic injury developed in 16.
Main Outcome Measures:
The groups were compared regarding their functional outcomes, including healing, time to healing, continence, and recurrence.
Results:
There were no significant differences in patient characteristics between groups. Patients who had irradiated rectourethral fistulas had a significantly higher rate of passage of urine through the rectum and wound infections, a higher rate of crystalloid infusion and blood transfusion requirements, and a longer time to ostomy reversal than nonirradiated patients. Patients who had irradiated rectourethral fistulas underwent more complex operative repairs, including gracilis interposition flaps (38%) and pelvic exenterations (19%), whereas nonirradiated patients most commonly underwent a York-Mason repair (50%). There were no statistically significant differences in rectourethral fistula healing or in postoperative and functional outcomes. Only 55% of irradiated patients had their ostomy reversed versus 91% in the nonirradiated group.
Limitations:
This study was limited by the small sample size and the retrospective nature of the review.
Conclusions:
Repair of rectourethral fistulas caused by radiation has a significantly higher wound infection rate and median time to healing, and lower overall stomal reversal rate than nonradiation-induced rectourethral fistulas. Patients who had irradiated rectourethral fistulas required significantly more complex operations, likely contributing to the higher morbidity, mortality, and lower fistula closure rate. We propose an algorithm for approaching rectourethral fistulas based on etiology.
More Related Videos
 05:09
Urethral Stricture Induction Followed by Buccal Mucosa Graft Urethroplasty in a Rat Model
Published on: April 28, 2023
 03:55
Urethroplasty with Pedicled Tunica Vaginalis for the Treatment of Long-segment Anterior Urethral Stricture Caused by Lichen Sclerosus of Glans Penis
Published on: October 18, 2024
Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:26
Aneurysm III: Interprofessional Care