Related Experiment Video
Updated: Apr 26, 2026

Biosensor-based High Throughput Biopanning and Bioinformatics Analysis Strategy for the Global Validation of Drug-protein Interactions
Published on: December 1, 2020
Physiologically based pharmacokinetic modeling of impaired carboxylesterase-1 activity: effects on oseltamivir
Zhe-Yi Hu1, Andrea N Edginton, S Casey Laizure
1Department of Clinical Pharmacy, University of Tennessee Health Science Center, College of Pharmacy, 881 Madison Ave., Room 346, Memphis, TN, 38163, USA.

Background And Objective:
Human carboxylesterase-1 (CES1) is an enzyme that is primarily expressed in the liver, where it plays an important role in the metabolism of many commonly used medications. Ethanol (alcohol)-mediated inhibition of CES1 and loss-of-function polymorphisms in the CES1 gene can markedly reduce this enzyme's function. Such alterations in CES1 activity may have important effects on the disposition of substrate drugs. The aim of this study is to develop a physiologically based pharmacokinetic (PBPK) model to predict changes in CES1 substrate drug exposure in humans with CES1 activity impaired by ethanol or loss-of-function CES1 genetic polymorphisms.
Methods:
The antiviral drug oseltamivir, an ethyl ester prodrug that is rapidly converted in vivo to the active metabolite oseltamivir carboxylate (OSC) by CES1 was used as a probe drug for CES1 activity. Oseltamivir PBPK models integrating in vitro and in vivo data were developed and refined. Then the changes in oseltamivir and OSC exposure in humans with CES1 impaired by ethanol or polymorphisms were simulated using a PBPK model incorporating in vitro inhibition and enzyme kinetic data. Model assumptions were verified by comparison of simulations with observed and published data. A sensitivity analysis was performed to gain a mechanistic understanding of the exposure changes of oseltamivir and OSC.
Results:
The simulated changes in oseltamivir and OSC exposures in humans with CES1 impaired by ethanol or polymorphism were similar to the observed data. The observed exposures to oseltamivir were increased by 46 and 37 % for the area under the plasma concentration-time curve from time zero to 6 h (AUC6) and from time zero to 24 h (AUC24), respectively, with co-administration of ethanol 0.6 g/kg. In contrast, only a slight change was observed in OSC exposure. The simulated data show the same trend as evidenced by greater change in exposures to oseltamivir (27 and 26 % for AUC(6) and AUC(24), [corrected] respectively) than OSC (≤6 %).
Conclusions:
The PBPK model of impaired CES1 activity correctly predicts observed human data. This model can be extended to predict the effects of drug interactions and other factors affecting the pharmacokinetics of other CES1 substrate drugs.
Related Concept Videos
 01:07
Physiological Pharmacokinetic Models: Incorporating Hepatic Transporter-Mediated Clearance
A recent model describes pravastatin's hepatobiliary excretion,...
 01:15
Impact of Pharmacokinetic–Pharmacodynamic Models: Regulatory Decisions
 01:14
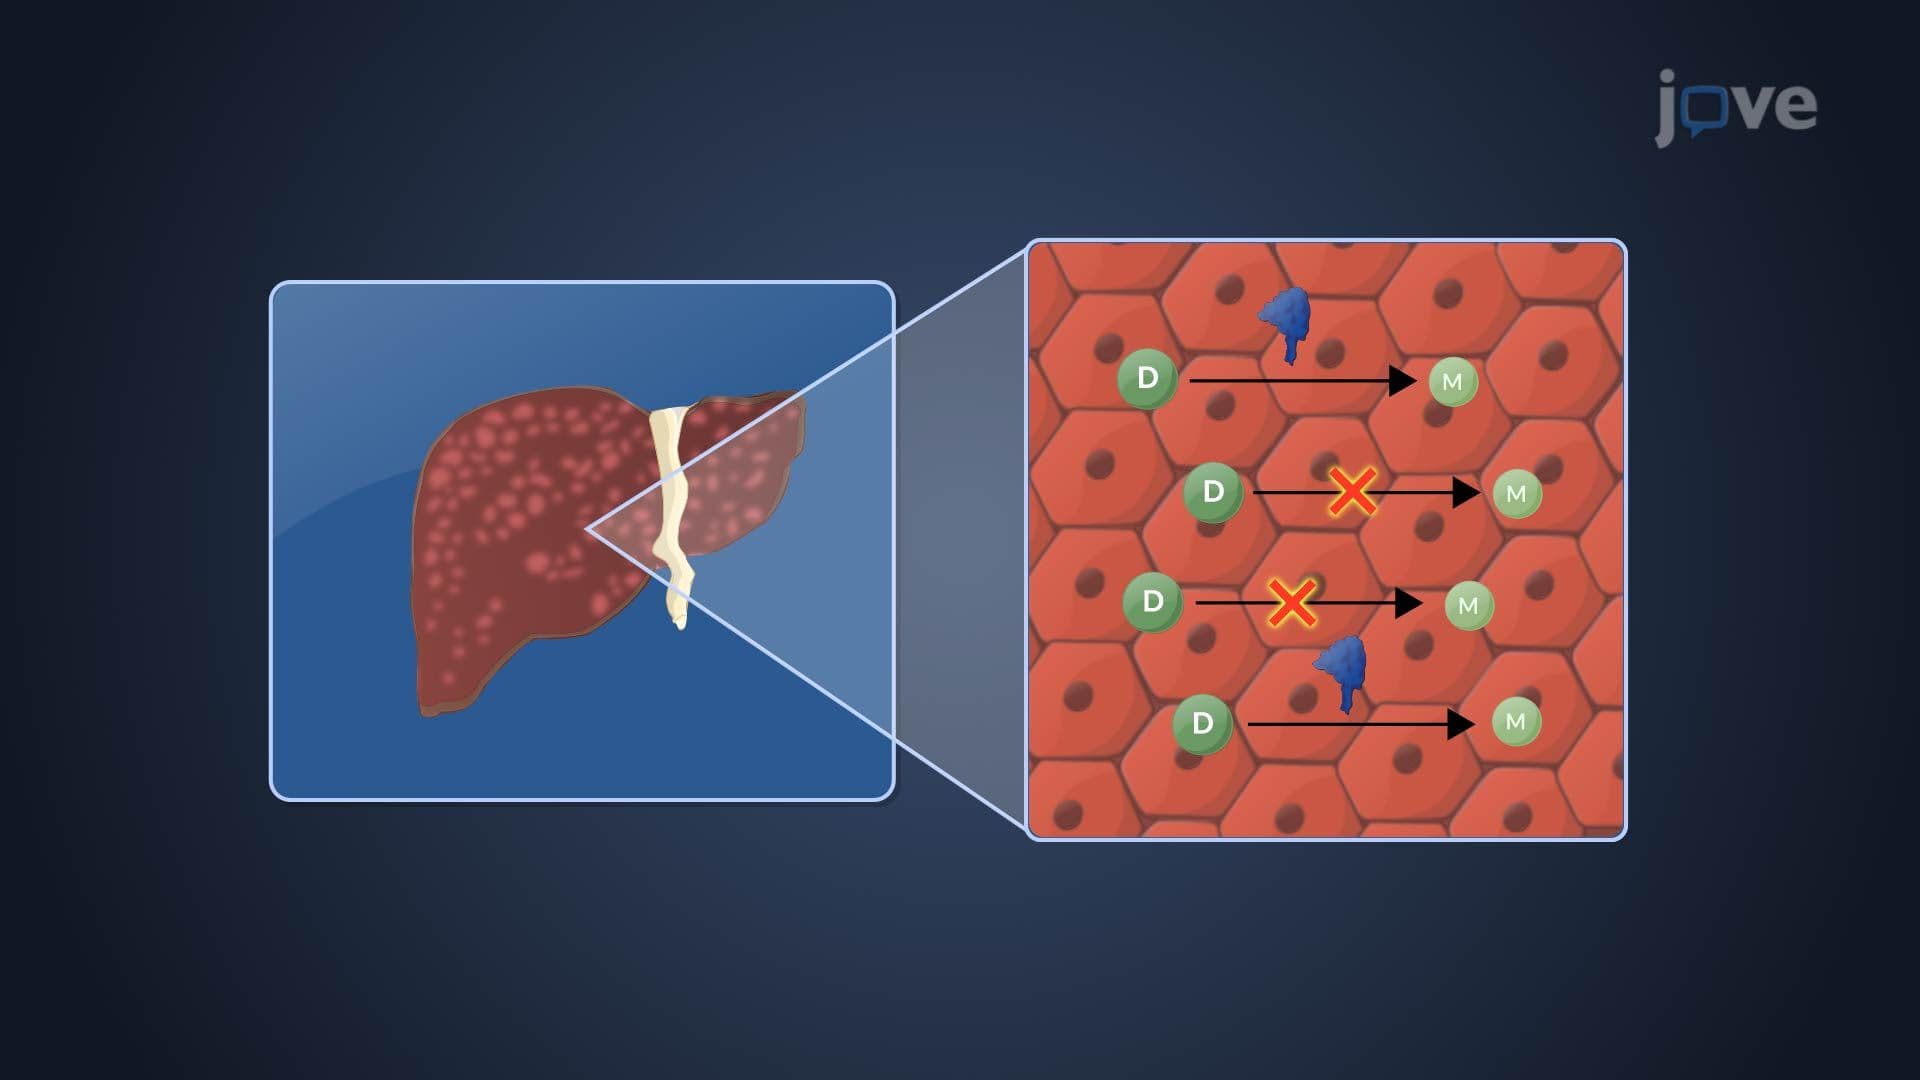
Effect of Hepatic Disease on Pharmacokinetics: Active Drug, Metabolite and Fraction of Metabolized Drug
 01:15
Pharmacodynamic Models: Linear Concentration–Effect Model
 01:18
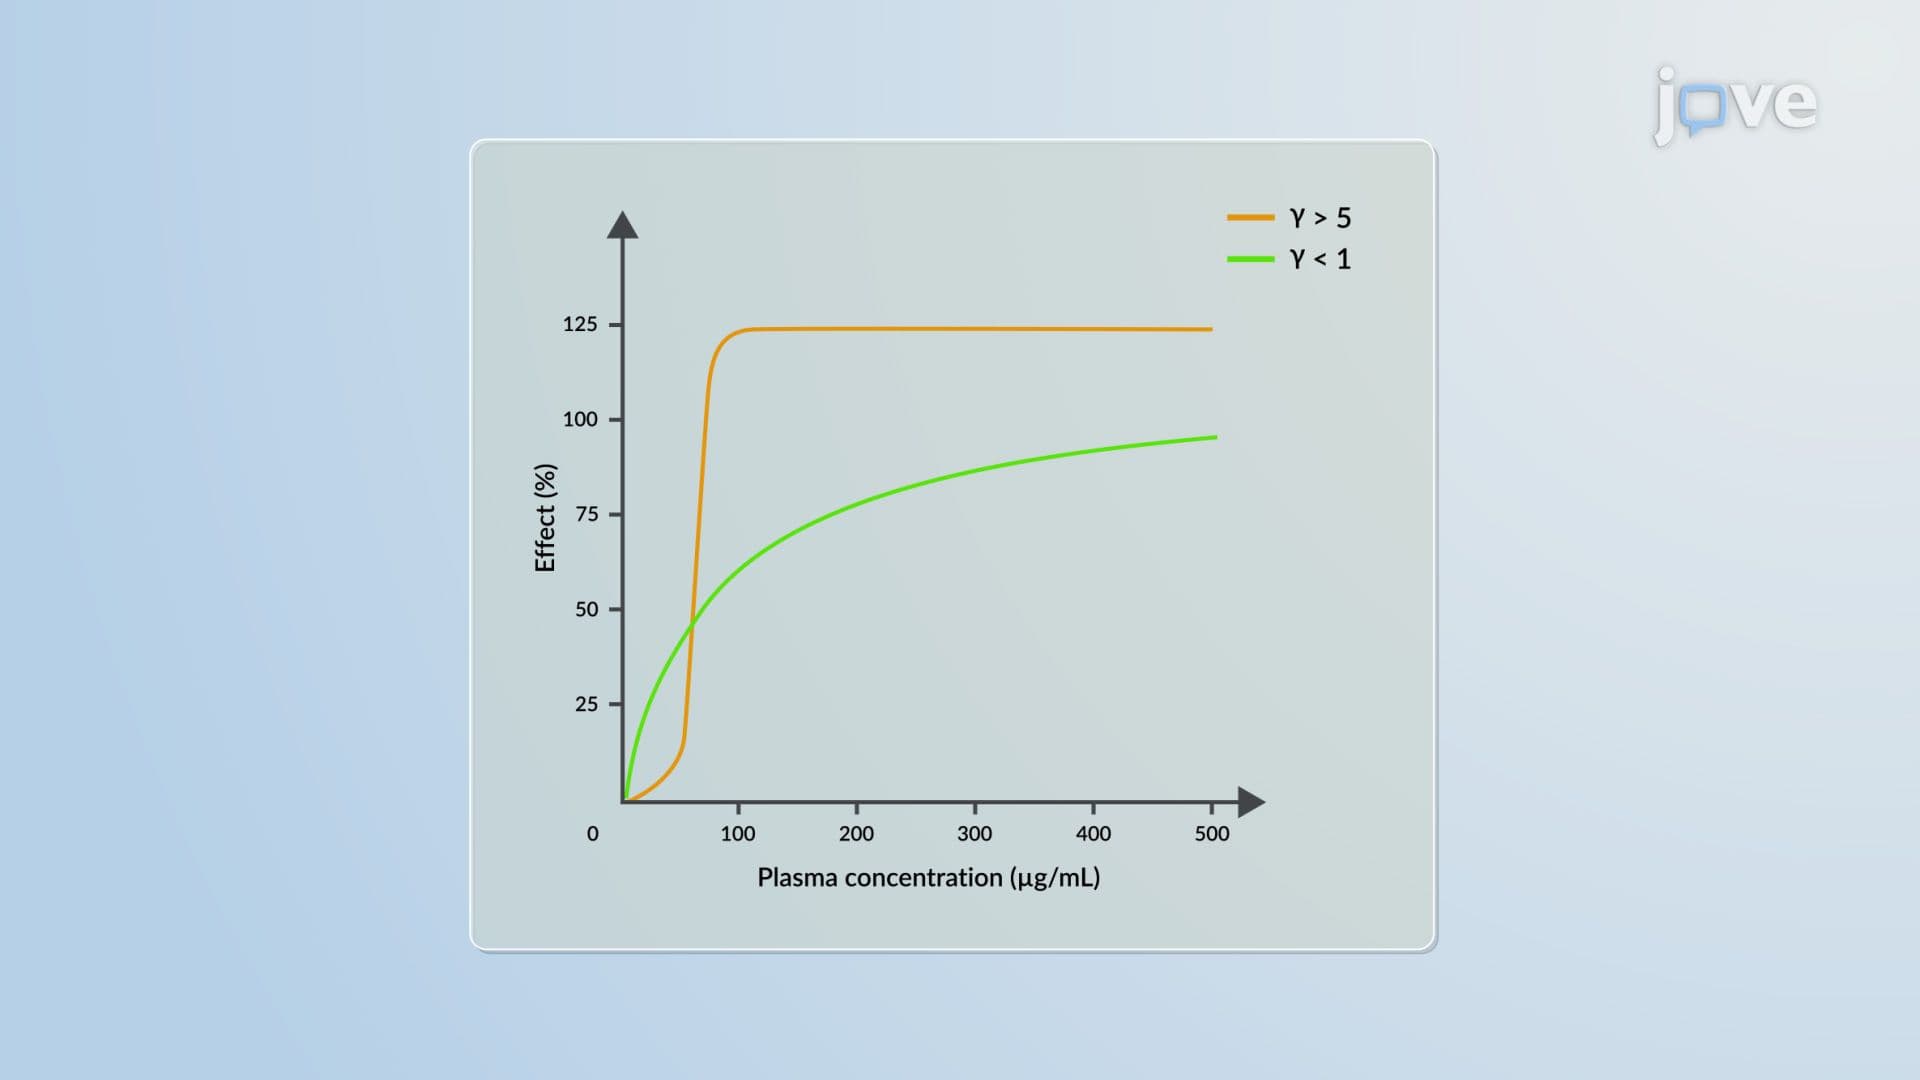
Pharmacodynamic Models: Emax Drug–Concentration Effect Model
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment