Related Experiment Video
Updated: Apr 26, 2026

Author Spotlight: A Reproductive Hysteroscopy Approach for Complete Endometrial Polyp Removal and Enhanced Endometrial Receptivity
Published on: August 2, 2024
Treatment of simple and complex endometrial non-atypical hyperplasia with natural progesterone: response rate to
Chiara Marra1, Cristina Penati1, Luisa Ferrari1
1a Division of Obstetrics and Gynecology, San Gerardo Hospital, University of Milan-Bicocca Monza Italy.

Abstract:
The aim of this study is to evaluate the response rate to natural progesterone in non-atypical endometrial hyperplasia and to identify the lowest effective dose. A total of 197 patients of childbearing age with simple or complex hyperplasia were retrospectively identified. The women were treated with a cyclic administration of progesterone at different dosages (100 versus 200 versus 300 mg daily). Endometrial biopsies were performed at 6, 12, 18 months. In comparing progesterone to a regimen of no therapy, a significantly higher remission rate was observed in the progesterone group than in the latter (95 versus 75%, p = 0.05 for simple hyperplasia; 89 versus 35%, p < 0.001 for complex hyperplasia). Out of 60 women with simple hyperplasia, remission was observed in 9/11 (81.8%), 40/41 (97.5%) and 8/8 (100%) patients treated, respectively, with progesterone 100, 200 and 300 mg daily. Out of 72 women with complex hyperplasia, remission was observed in 3/5 (60%), 49/53 (92.4%) and 12/14 (85.7%) patients treated with progesterone 100, 200 and 300 mg daily, respectively. There was no statistically significant difference in the response rate in the two groups, neither with simple nor with complex hyperplasia. In conclusion, progesterone increased the regression rate of both simple and complex hyperplasia.

Related Concept Videos
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH...
 01:20
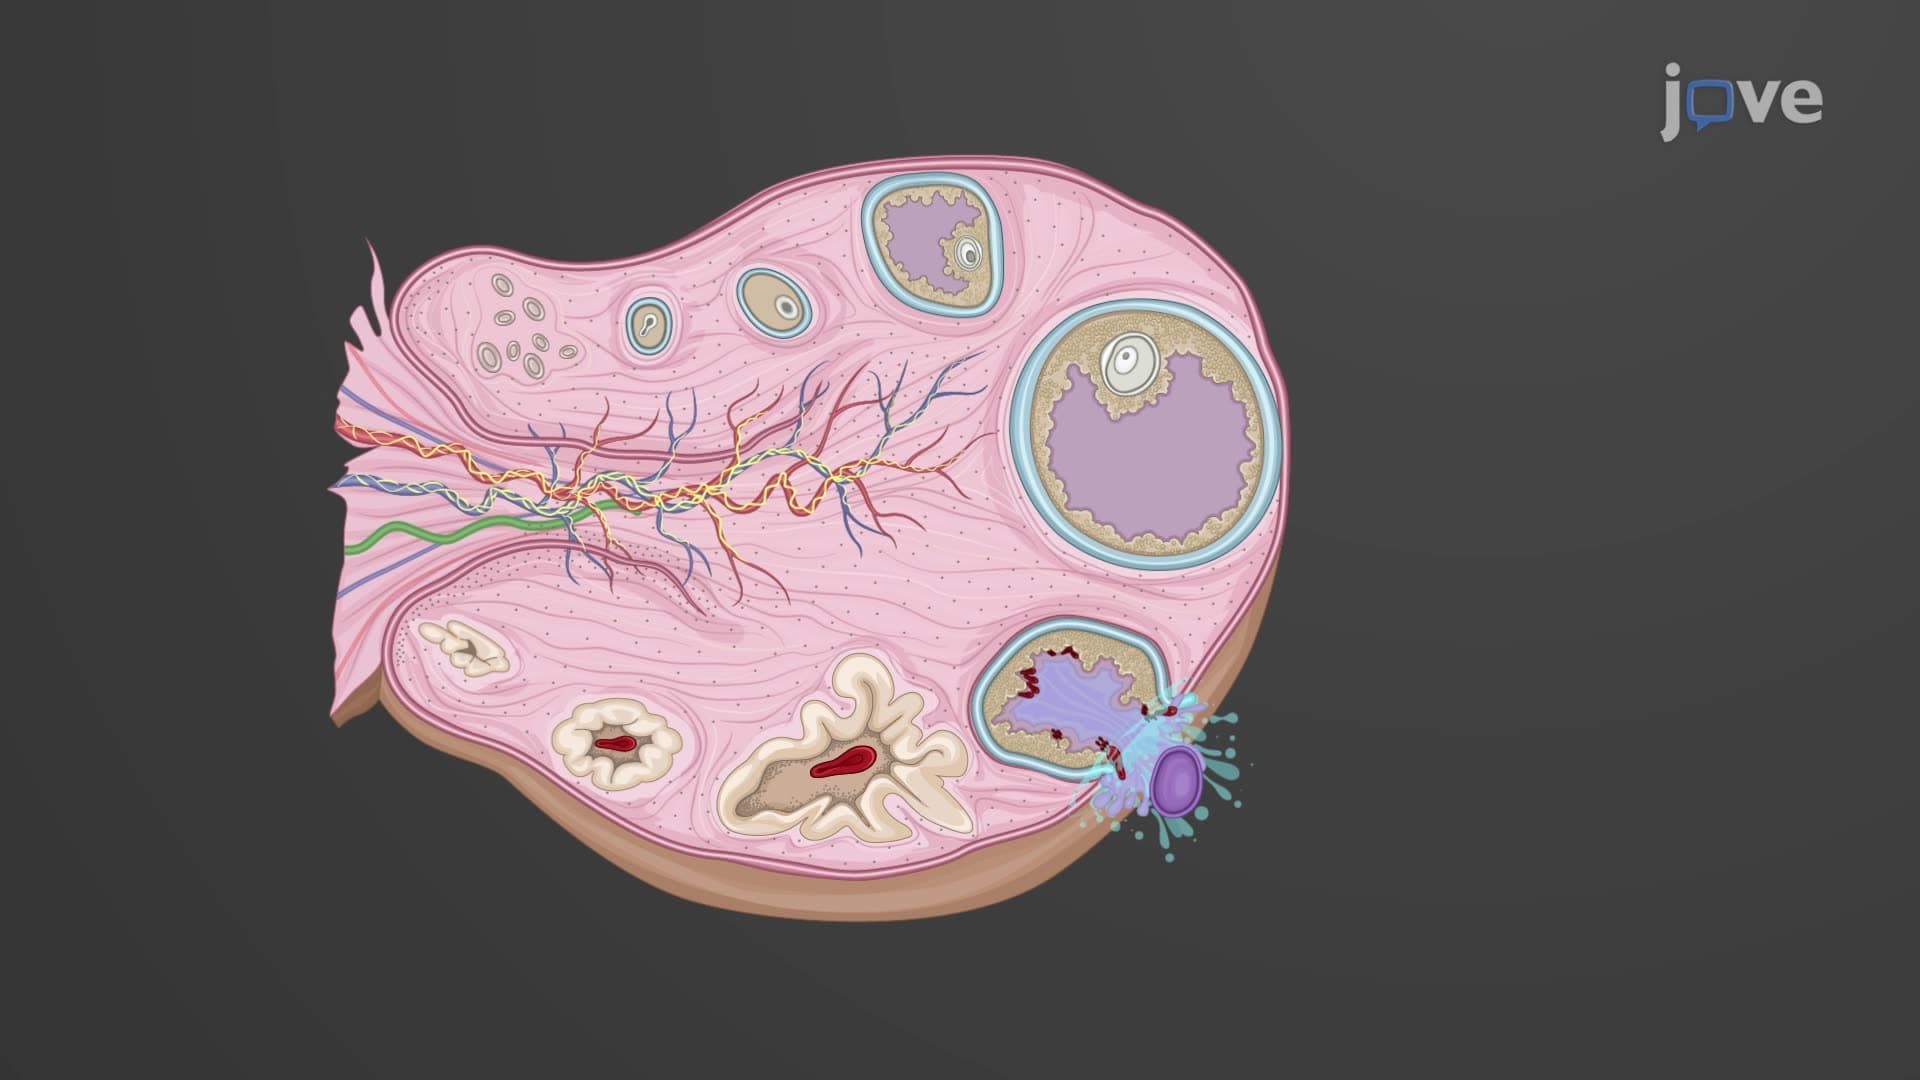
Proliferative Phase
Notably, the stratum basale, the basal layer of the endometrium, including the basal parts of the uterine glands, remains unaffected by menstruation. Stem cells in this layer undergo mitosis, regenerating the stratum functionalis and thickening the...
 01:27
Ovarian Cycle
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:22
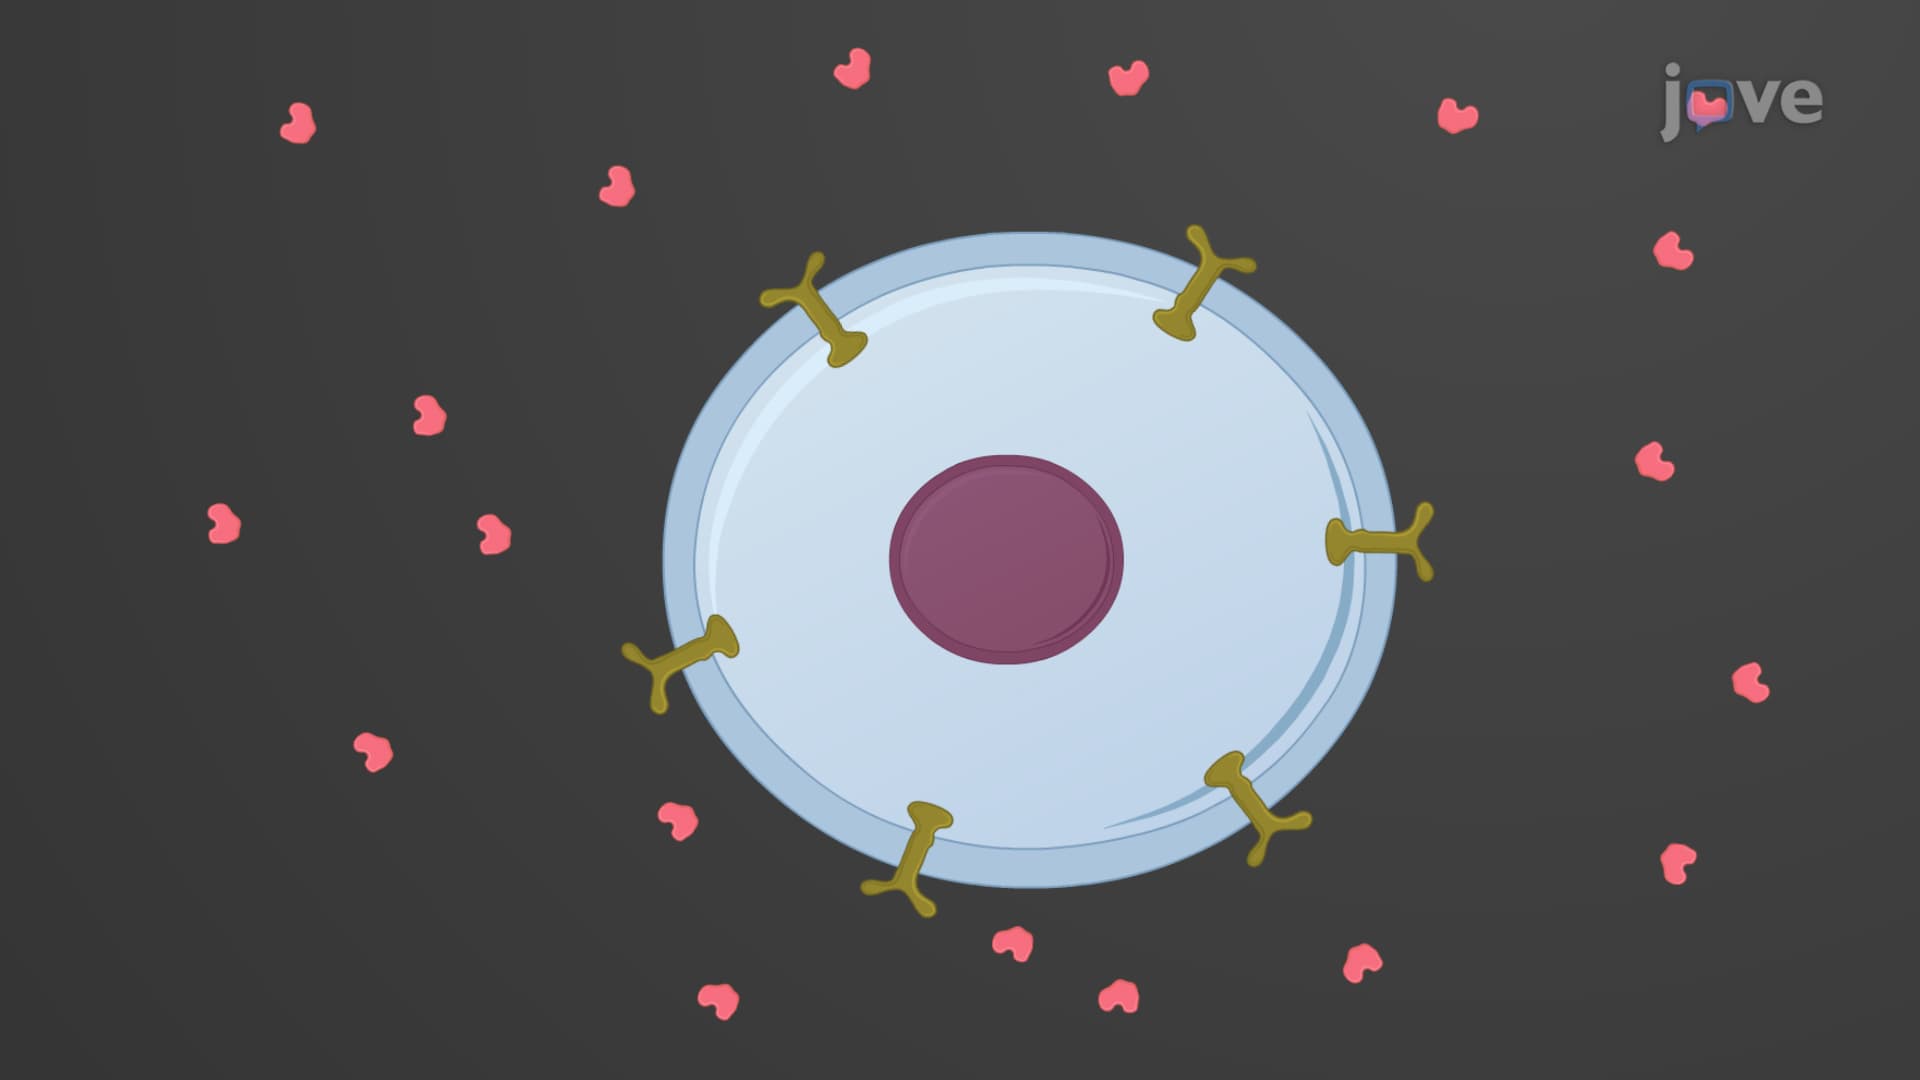
Target Cell Response to Hormones
Notably, the cellular response can be regulated by altering the number of receptors expressed in the cell. For example, prolonged exposure to elevated hormone levels results in a gradual decline or down-regulation in the number of receptors for that specific hormone on the cell surface. Conversely, in response to low hormone levels, cells may use up-regulation, producing an...
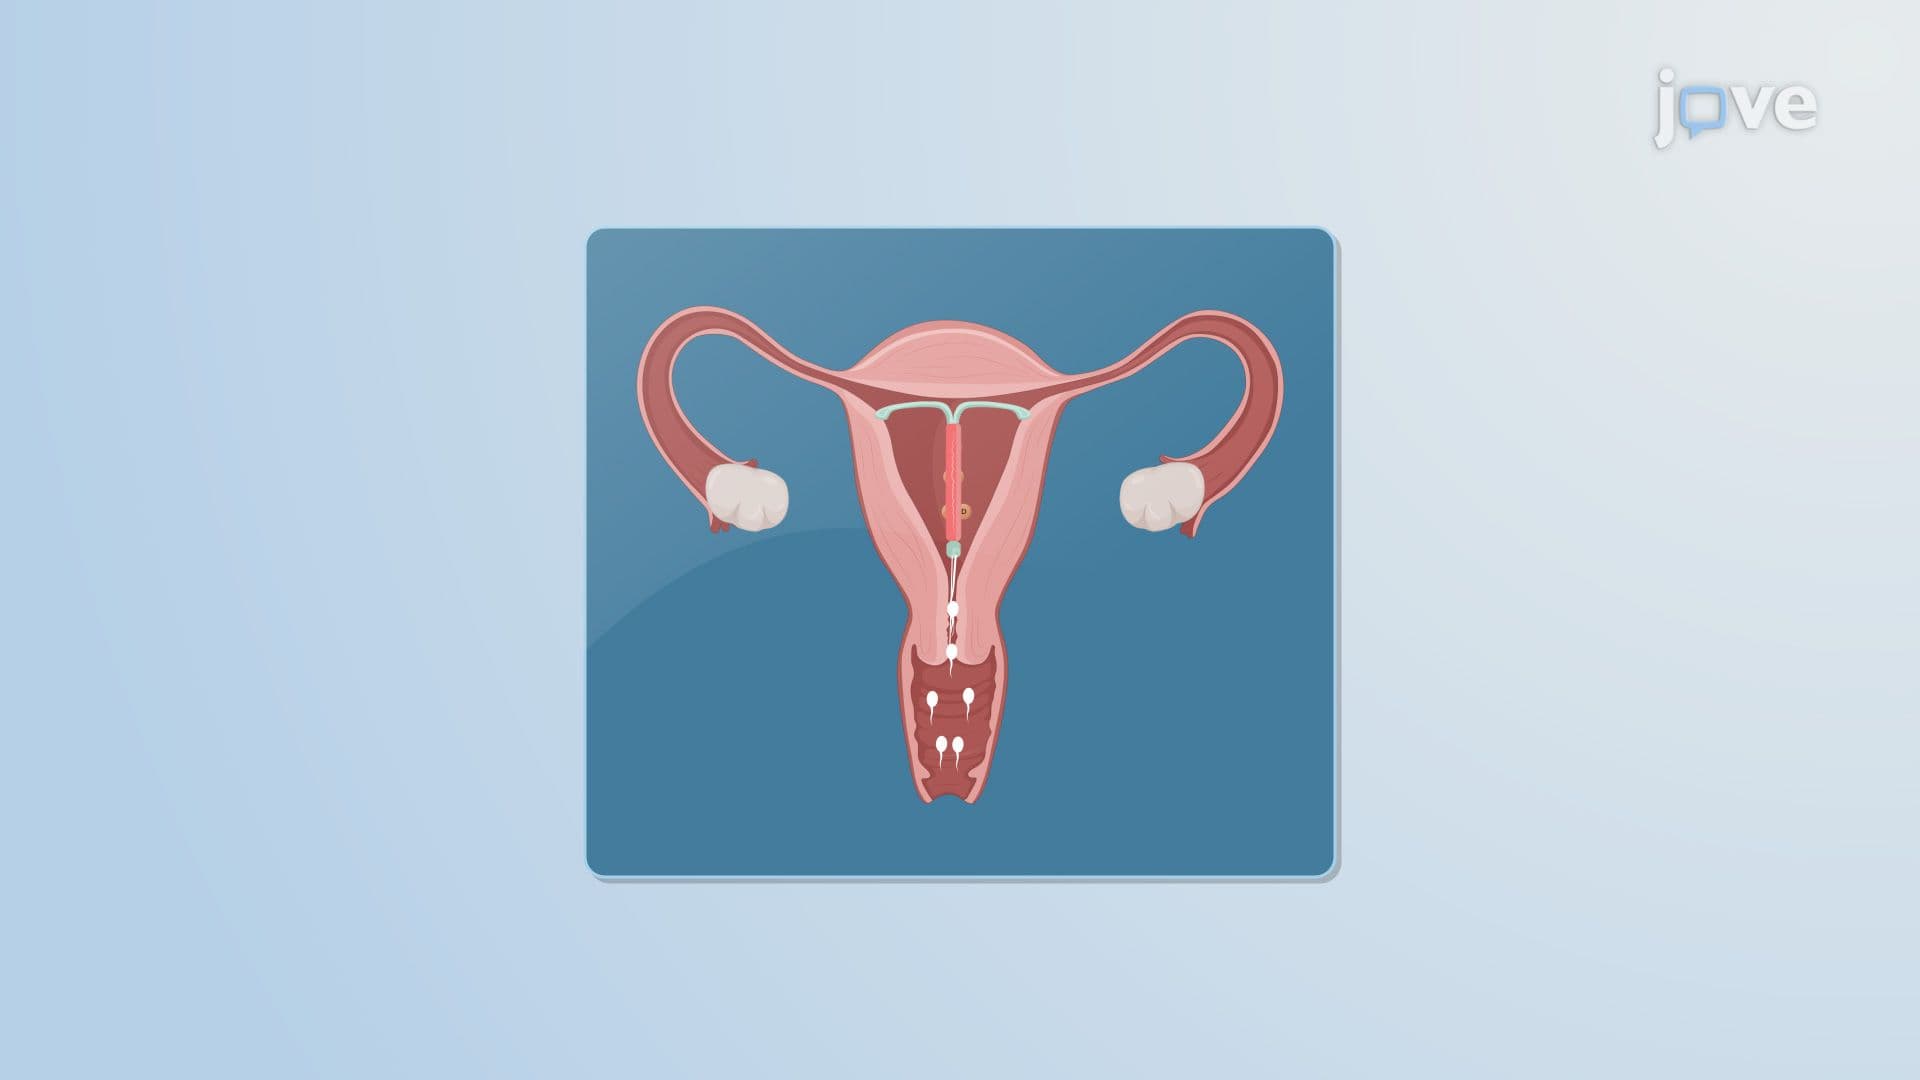 01:21
Intrauterine Drug Delivery Systems