Related Experiment Video
Updated: Apr 25, 2026
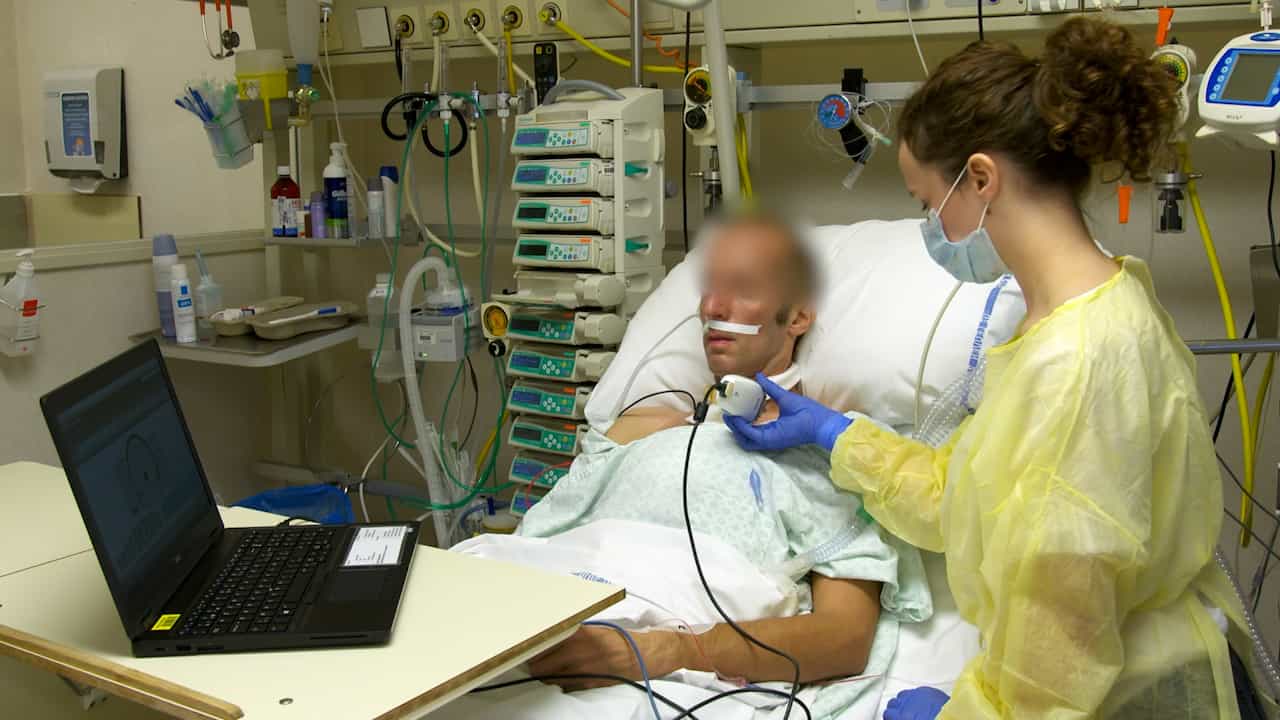

Inspiratory Muscle Training as an Adjunct to the Treatment of Weaning Failure in Critically Ill Patients: A Practical Guide
Published on: January 30, 2026
Evolution of inspiratory diaphragm activity in children over the course of the PICU stay
Guillaume Emeriaud1, Alexandrine Larouche, Laurence Ducharme-Crevier
1Pediatric Intensive Care Unit, CHU Sainte-Justine, Université de Montréal, Montreal, Quebec, Canada, guillaume.emeriaud@umontreal.ca.

Insights
Critically ill children on mechanical ventilation often show low diaphragm activity, indicating potential overassistance or oversedation. Monitoring electrical activity of the diaphragm (EAdi) can help identify these issues.
Area of Science:
- Pediatric critical care medicine
- Respiratory physiology
- Diaphragm monitoring
Background:
- Mechanical ventilation can lead to diaphragm atrophy in critically ill patients.
- Monitoring the electrical activity of the diaphragm (EAdi) is crucial for assessing diaphragm function.
- Lack of reference values for EAdi in pediatric intensive care units (PICU) complicates interpretation.
Purpose of the Study:
- To describe EAdi values in critically ill children throughout their PICU stay.
- To assess the impact of ventilatory support on EAdi in children.
- To establish reference EAdi values for pediatric critical care.
Main Methods:
- Prospective longitudinal observational study.
- Inclusion criteria: children requiring mechanical ventilation for ≥24 hours.
- EAdi recorded using a validated method during acute phase, pre-extubation, post-extubation, and pre-discharge.
Main Results:
- Fifty-five children were enrolled.
- Low EAdi values and frequent diaphragm inactivity were observed during conventional mechanical ventilation.
- EAdi significantly increased after extubation during spontaneous ventilation (p < 0.001).
- Lung pathology was associated with higher EAdi.
Conclusions:
- This study provides the first systematic description of EAdi evolution in pediatric ICU patients.
- Frequent low diaphragm activity suggests overassistance or oversedation during mechanical ventilation.
- EAdi monitoring is a valuable tool for detecting inappropriate ventilator settings or sedation levels.
Purpose:
Diaphragm function should be monitored in critically ill patients, as full ventilatory support rapidly induces diaphragm atrophy. Monitoring the electrical activity of the diaphragm (EAdi) may help assess the level of diaphragm activity, but such monitoring results are difficult to interpret because reference values are lacking. The aim of this study was to describe EAdi values in critically ill children during a stay in the pediatric intensive care unit (PICU), from the acute to recovery phases, and to assess the impact of ventilatory support on EAdi.
Methods:
This was a prospective longitudinal observational study of children requiring mechanical ventilation for ≥24 h. EAdi was recorded using a validated method in the acute phase, before extubation, after extubation, and before PICU discharge.
Results:
Fifty-five critically ill children were enrolled in the study. Median maximum inspiratory EAdi (EAdimax) during mechanical ventilation was 3.6 [interquartile range (IQR) 1.2-7.6] μV in the acute phase and 4.8 (IQR 2.0-10.7) μV in the pre-extubation phase. Periods of diaphragm inactivity (with no detectable inspiratory EAdi) were frequent during conventional ventilation, even with a low level of support. EAdimax in spontaneous ventilation was 15.4 (IQR 7.4-20.7) μV shortly after extubation and 12.6 (IQR 8.1-21.3) μV before PICU discharge. The difference in EAdimax between mechanical ventilation and post-extubation periods was significant (p < 0.001). Patients intubated mainly because of a lung pathology exhibited higher EAdi (p < 0.01), with a similar temporal increase.
Conclusions:
This is the first systematic description of EAdi evolution in children during their stay in the PICU. In our patient cohort, diaphragm activity was frequently low in conventional ventilation, suggesting that overassistance or oversedation is common in clinical practice. EAdi monitoring appears to be a helpful tool to detect such situations.


Related Concept Videos
 01:24
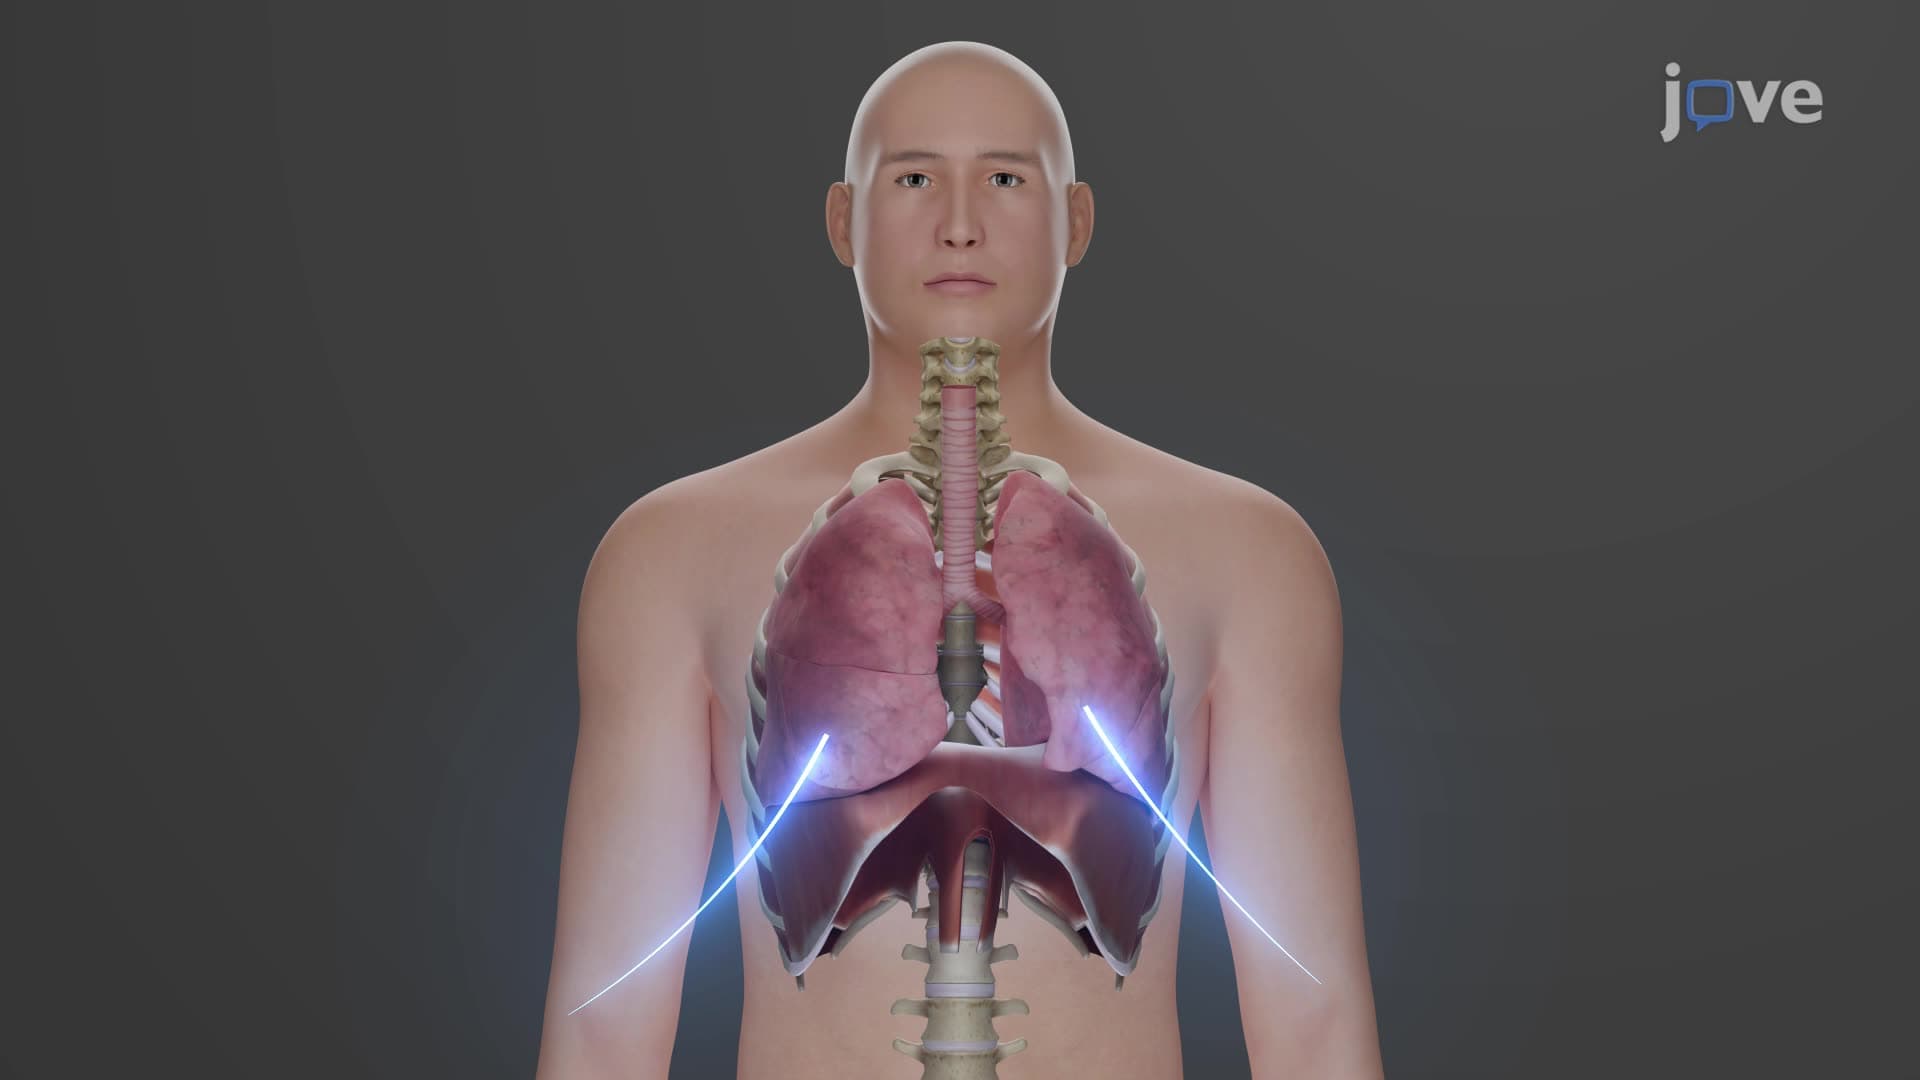
Pulmonary Ventilation: Inhalation
Boyle's law becomes particularly pertinent when examining respiratory...
 01:17
Pulmonary Cycle: Exhalation
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration...
 01:30
Mechanism of Breathing I: Inspiration
The respiratory system, an essential network for breathing, comprises the conducting and respiratory zones, each playing a crucial role in the overall process of respiration. Let us explore the detailed mechanism of inspiration, or inhalation, which is the first phase of the respiratory cycle.
Pathway of Air during Inspiration
During inspiration, air enters our body through the nose or mouth and moves through the conducting zone,...
 01:21
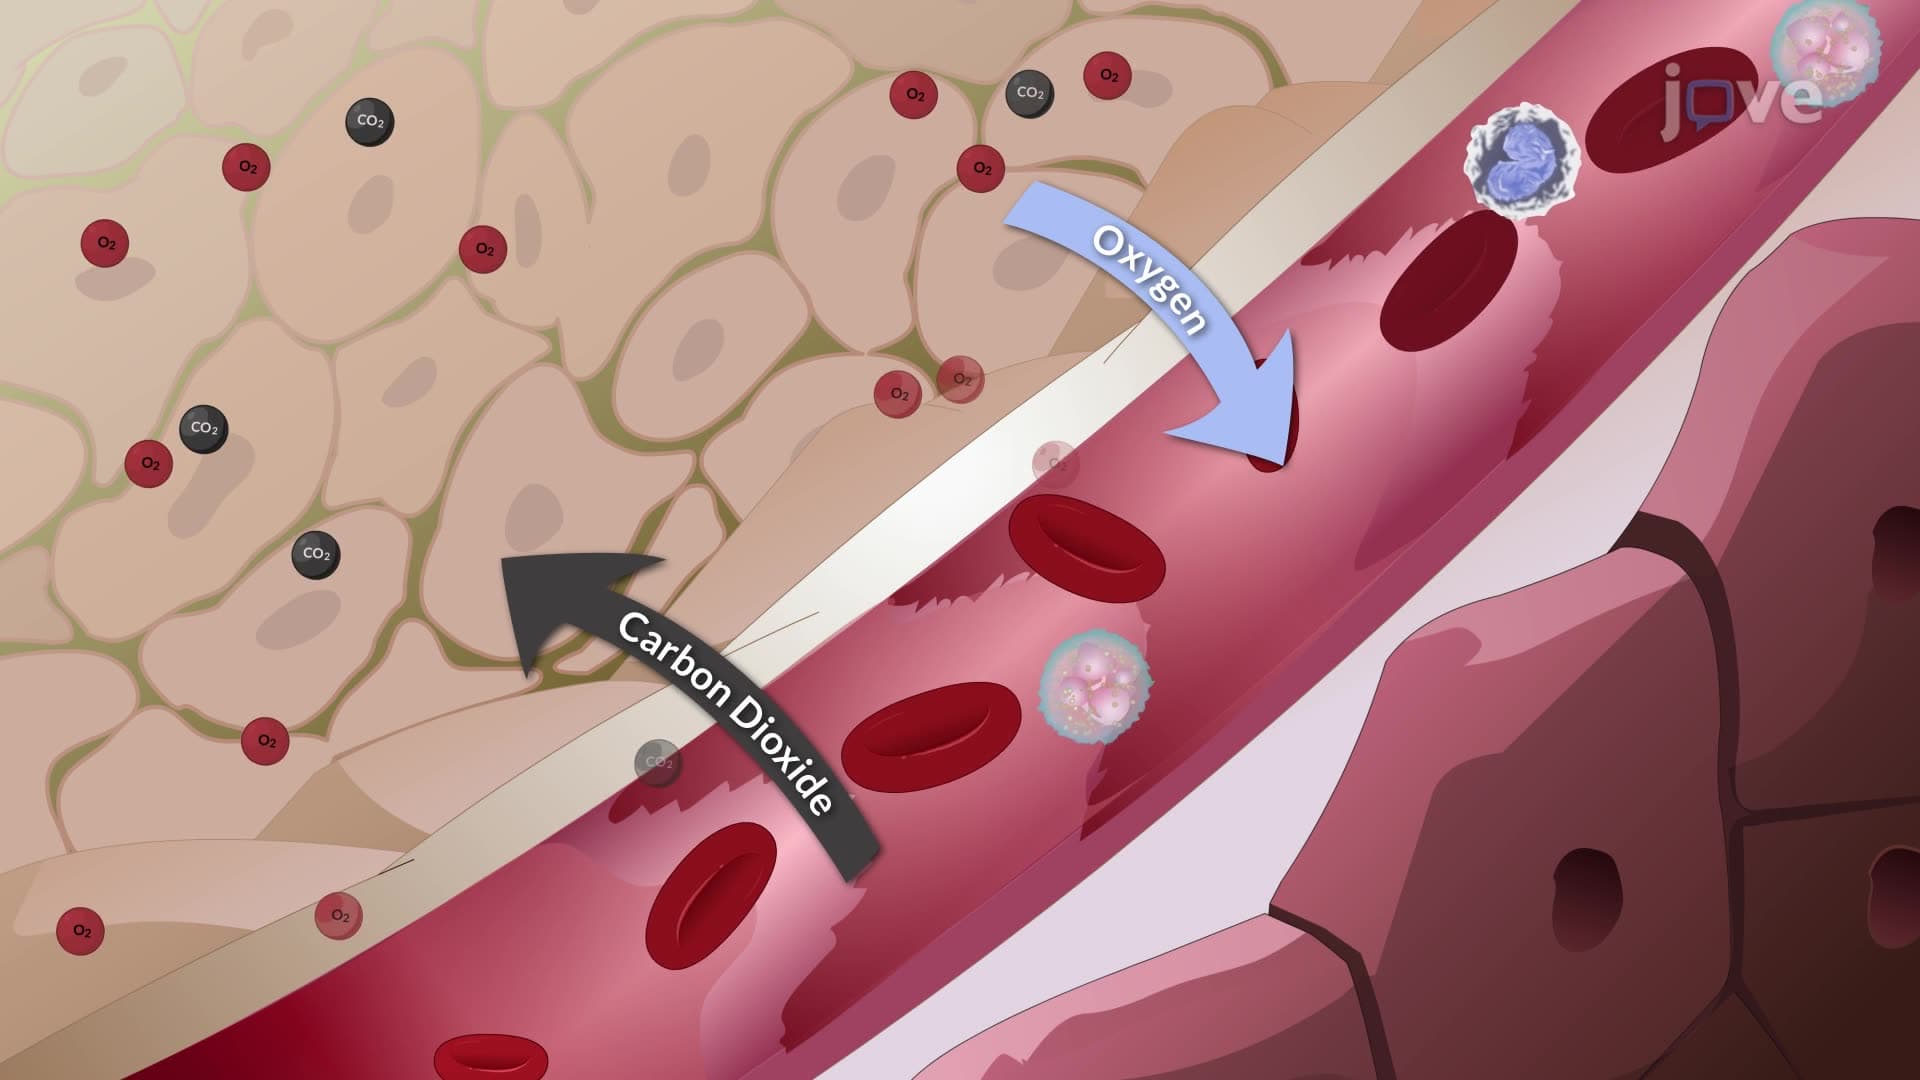
Mechanism of Breathing III: The Accessory Muscles
The respiratory system is a complex network that relies on primary respiratory muscles like the diaphragm, but also involves accessory muscles to enhance lung expansion and airflow during both inhalation and exhalation.
Enhancing Inhalation with Accessory Muscles:
Accessory muscles such as the sternocleidomastoid, scalene, intercostal, and abdominal muscles are crucial when additional respiratory effort is required, such as during deep...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: