Related Experiment Video
Updated: Apr 25, 2026
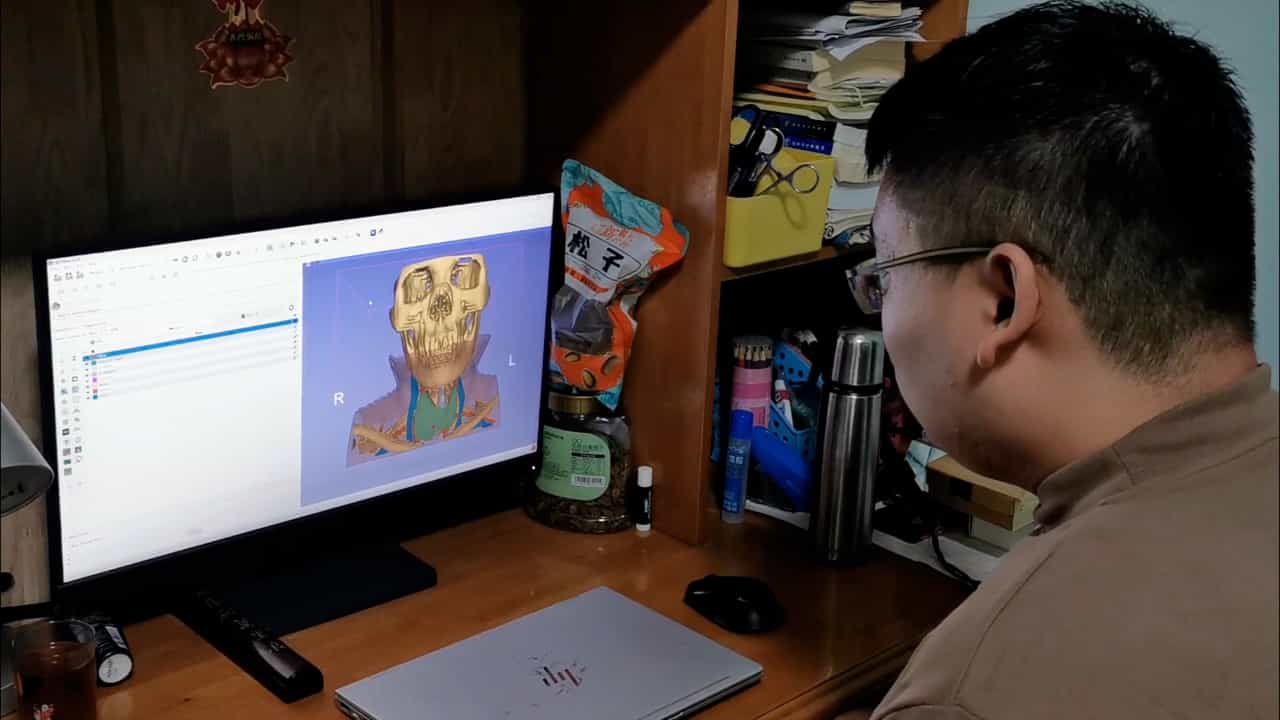

Mixed Reality Assisted Radical Endoscopic Thyroidectomy
Published on: January 31, 2025
Risk factors target in patients with post-thyroidectomy bleeding
Endong Chen1, Yefeng Cai1, Quan Li1
1Department of Surgical Oncology, The First Affiliated Hospital of Wenzhou Medical University Wenzhou, Zhejiang, China.

Abstract:
As the highly blood flow of thyroid gland post-thyroidectomy bleeding (PTB) is a serious and life-threatening complication. Our aim was to investigate factors that influenced bleeding after thyroidectomy. Between February 2008 and September 2012, the data of 4449 consecutive patients with thyroid diseases undergoing thyroidectomy were collected and analysed from the department of surgical oncology retrospectively. During the study period, 88 (2.0%) patients were identified to have clinically PTB. 6 risk factors were significantly related to PTB: gender (OR 3.243; 95% CI 2.078-5.061; P < 0.001), age (OR 1.025; 95% CI 1.006-1.043; P = 0.009), tumor size (OR 4.495; 95% CI 2.462-8.208; P < 0.001), postoperative hypertension (OR 2.195; 95% CI 1.006-1.043; P = 0.035), lymph node dissection (OR 3.384; 95% CI 2.146-5.339; P < 0.001) and Graves' disease (OR 3.744; 95% CI 1.920-7.303; P < 0.001). We addressed the most common explicit source of bleeding by reexploration: infrahyoid muscles (30/88), beside the laryngeal recurrent nerve (22/88), subcutaneous tissue (10/88) and superior pole (10/88). In our study, male gender, older age, tumor size > 3 cm, postoperative hypertension (SP > 150 mmHg), lymph node dissection and Graves' disease were independent risk factors for PTB. The sources of bleeding were identified more frequently in the infrahyoid muscles and beside the laryngeal recurrent nerve. It is helpful for surgeons to decide the potential bleeding points during the reexploration of PTB.

Related Concept Videos
 01:25
Hyperthyroidism I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology
 01:28
Graves' Disease I: Introduction
 01:24
Graves Disease II: Pathophysiology
 01:22
Aneurysm IV: Nursing Management
 01:23
Hypothyroidism II: Pathophysiology