Related Experiment Video
Updated: Apr 25, 2026


New Thrombectomy Technique for Total Portal Vein Thrombosis in Liver Transplantation
Published on: June 27, 2025
Hepatic artery thrombosis in live liver donor transplantation: how to solve--a case report
S Rodrigues1, A Martins1, E Barroso1
1Hepato-Bilio-Pancreatic and Transplantation Centre of Curry Cabral's Hospital, Lisboa, Portugal.

Insights
Living donor liver transplantation offers a vital solution to donor shortages. Prompt intervention for hepatic artery thrombosis, a severe complication, can prevent graft loss and the need for re-transplantation.
Area of Science:
- Hepatobiliary Surgery
- Transplant Surgery
- Vascular Surgery
Background:
- Decreased cadaveric organ availability limits liver transplantation, increasing patient mortality.
- Living donor liver transplantation (LDLT) is a viable alternative to expand donor pools.
- Hepatic artery thrombosis (HAT) is a critical complication following liver transplantation.
Observation:
- A 48-year-old male with hepatocellular carcinoma and chronic hepatitis B virus-induced liver failure underwent LDLT.
- Postoperative Doppler echocardiography revealed absent arterial flow, confirmed as right hepatic artery thrombosis via CT angiography.
- The patient presented with a critical complication of liver transplantation: hepatic artery thrombosis.
Findings:
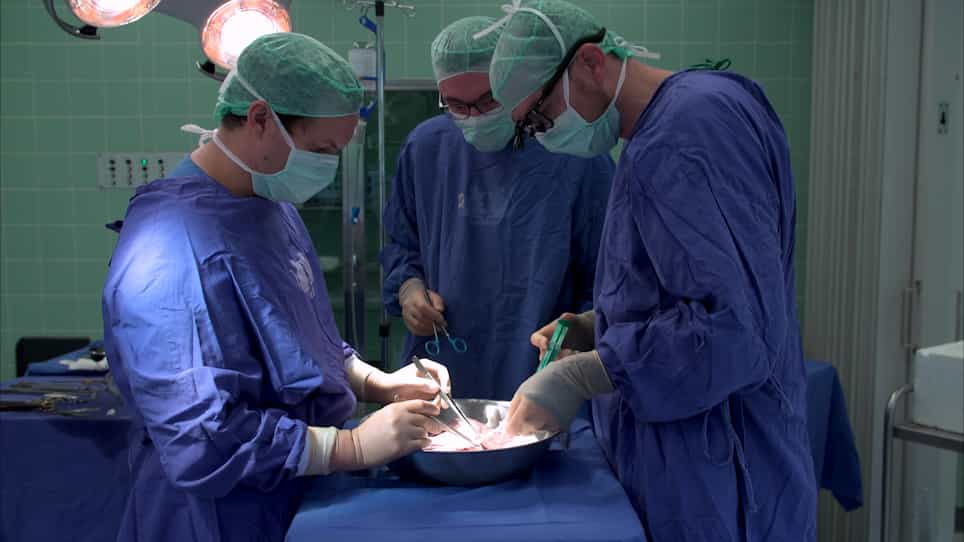
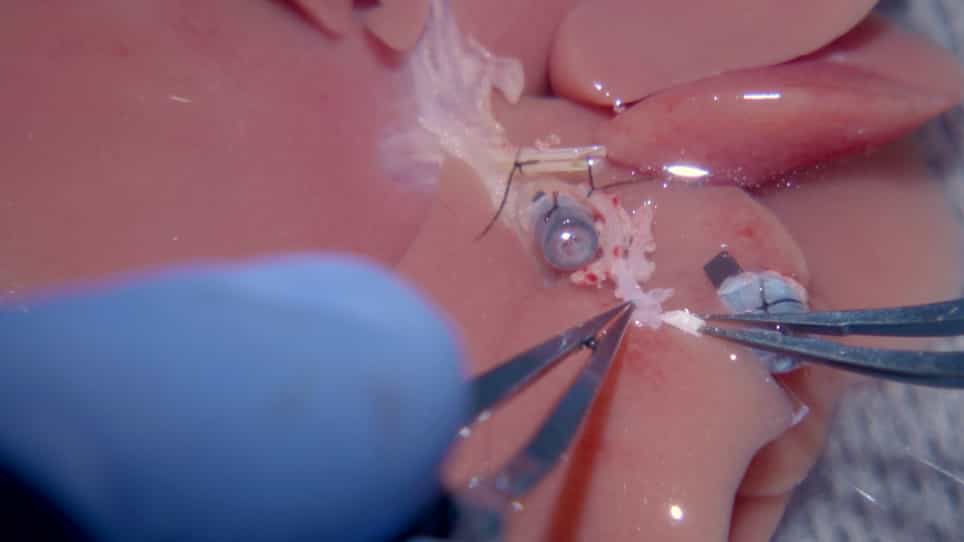
- Urgent re-laparotomy successfully performed thrombectomy and hepatic artery re-anastomosis using a splenic artery interposition graft.
- Post-intervention anticoagulation and antiplatelet therapy (aspirin) maintained graft patency.
- Serial Doppler evaluations confirmed sustained hepatic artery patency, with the patient remaining asymptomatic.
Implications:
- Early diagnosis and prompt surgical revascularization are crucial for managing HAT after LDLT.
- Timely intervention prevents graft ischemia, biliary complications, and hepatic parenchyma damage.
- Successful management of HAT can avert the need for re-transplantation, improving patient outcomes.
Abstract:
The decrease in the number of cadaveric donors has proved a limiting factor in the number of liver transplants, leading to the death of many patients on the waiting list. The living donor liver transplantation is an option that allows, in selected cases, increase the number of donors. One of the most serious complications in liver transplantation is hepatic artery thrombosis, in the past considered potentially fatal without urgent re-transplantation. A white male patient, 48 years old, diagnosed with hepatocellular carcinoma in chronic liver failure caused by hepatitis B virus, underwent living donor liver transplantation (right lobe). Doppler echocardiography performed in the immediate postoperative period did not identify arterial flow in the right branch, having been confirmed thrombosis of the right hepatic artery in CT angiography. Urgent re-laparotomy was performed, which consisted of thrombectomy and re-anastomosis of the hepatic artery with segmental splenic artery allograft interposition. The patient started anticoagulation and antiplatelet therapy with acetylsalicylic acid. Serial evaluation with Doppler echocardiography showed hepatic artery patency. At present, the patient is asymptomatic. One of the most devastating complications in liver transplantation, and particularly in living liver donor, is thrombosis of the hepatic artery; thus, early diagnosis and treatment is vital. The rapid intervention for revascularization of the graft avoids irreversible ischemia of the bile ducts and hepatic parenchyma, thus avoiding the need for re-transplantation.