Related Experiment Video
Updated: Apr 25, 2026
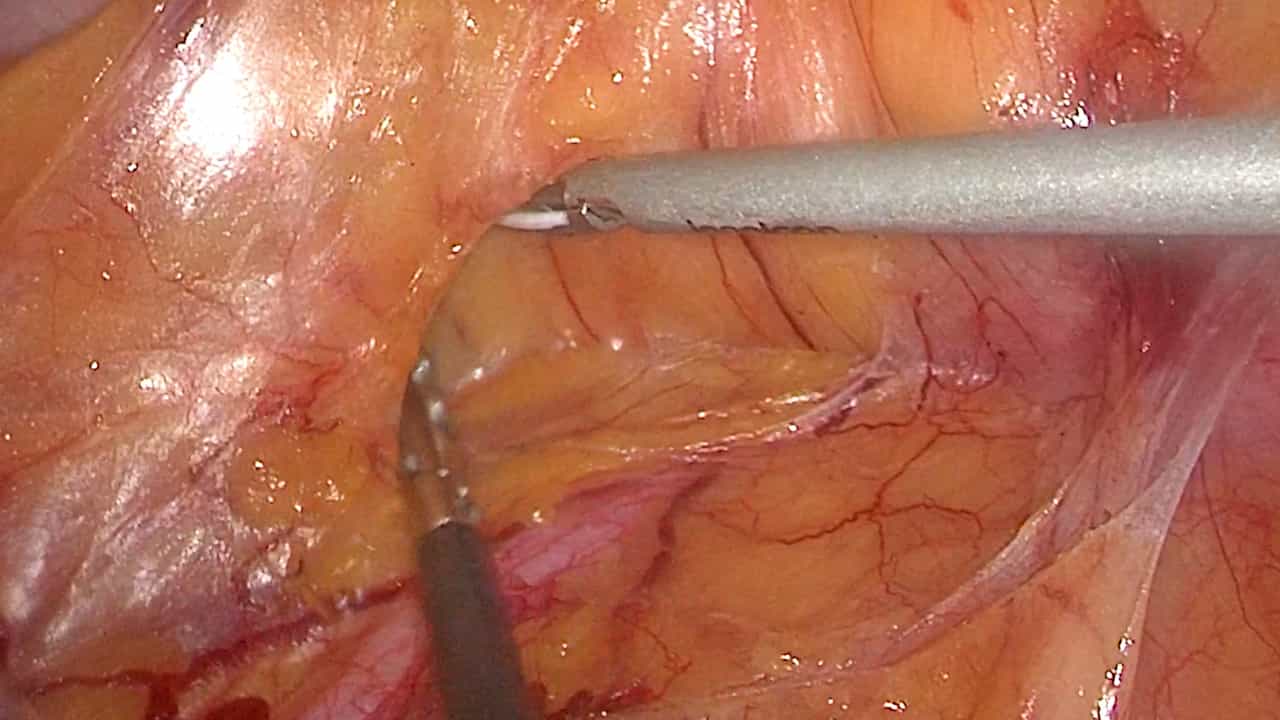

Caudal-to-cranial Approach in Laparoscopic Right Hemicolectomy with Complete Mesocolon Excision and D3 Lymph Node Dissection
Published on: January 9, 2026
Cranial-to-caudal approach for radical lymph node dissection along the surgical trunk in laparoscopic right
Takeru Matsuda1, Takeshi Iwasaki, Masaaki Mitsutsuji
1Department of Surgery, National Hospital Organization Kobe Medical Center, 3-1-1 Nishi-Ochiai, Suma-Ku, Kobe, 654-0155, Japan, takerumatsuda@nifty.com.

Abstract:
Complete mesocolic excision with central vascular ligation is considered to contribute to superior oncological outcomes after colon cancer surgery [1]. For advanced right-sided colon cancer, this surgery sometimes requires lymph node (LN) dissection along the superior mesenteric vein (SMV), with division of the middle colic vessels, or their right branches, at origin [2]. Here, we present cranially approached radical LN dissection along the surgical trunk during laparoscopic right hemicolectomy. The omental bursa is first opened wide, and the gastrocolic trunk of Henle is exposed, using the right gastroepiploic vessels and the accessory right colic vein (ARCV) as landmarks. After division of ARCV, SMV and middle colic vein (MCV) are identified. After dividing MCV at its root, LN dissection along SMV is conducted in a cranial-to-caudal manner. Concurrently, the middle colic artery, or its right branch, is exposed and divided at origin. The transverse colon is then raised ventrally, and LN dissection along SMV using a cranial-to-caudal approach is again performed. The ileocolic and right colic vessels are divided at origin. The ascending and transverse mesocolon, including the pedicles, are then separated from the retroperitoneal tissues, pancreatic head, and duodenum, using a medial approach. The key characteristics in this procedure consist of easy access to pancreas, early division of ARCV and middle colic vessels at origin, and easy dissection along SMV. We performed a laparoscopic colectomy using this approach for 18 patients with right-sided colon cancer. The mean operative time and blood loss were 288 min and 83 ml, respectively. The mean number of harvested LNs was 24. There were 6 cases with positive LN metastasis. There were no recurrent cases at a median follow-up period of 24 months. We consider this approach to be safe and useful for radical LN dissection along SMV for right-sided colon cancers.
More Related Videos
 05:58
Surgical Trunk Oriented Laparoscopic Right Hemicolectomy (ST-LRH) for Right-Sided Colon Cancer
Published on: July 25, 2025
 05:43
The Role of Anatomical Dissection in Defining Colic and Small Bowel Artery Lymphovascular Bundles in the D3 Volume of Small and Large Bowel Mesentery
Published on: August 1, 2025