Related Experiment Video
Updated: Apr 25, 2026


Home-Based Prescribed Pulmonary Exercise in Patients with Stable Chronic Obstructive Pulmonary Disease
Published on: August 24, 2019
Mechanisms of exercise intolerance in global initiative for chronic obstructive lung disease grade 1 COPD
Jordan A Guenette1, Roberto C Chin2, Sicheng Cheng2
1Respiratory Investigation Unit, Queen's University and Kingston General Hospital, Kingston, ON, Canada Dept of Physical Therapy, University of British Columbia, Vancouver, BC, Canada Centre for Heart Lung Innovation, Providence Health Care Research Institute, University of British Columbia, St. Paul's Hospital, Vancouver, BC, Canada.

Abstract:
The purpose of this study was to determine if a dissociation existed between respiratory drive, as estimated by diaphragmatic electromyography (EMGdi), and its pressure-generating capacity during exercise in mild chronic obstructive pulmonary disease (COPD) and whether this, if present, had negative sensory consequences. Subjects meeting spirometric criteria for mild COPD (n=16) and age and sex-matched controls (n=16) underwent detailed pulmonary function testing and a symptom limited cycle test while detailed ventilatory, sensory and respiratory mechanical responses were measured. Compared with controls, subjects with mild COPD had greater ventilatory requirements throughout submaximal exercise. At the highest equivalent work rate of 60 W, they had a significantly higher: total work of breathing (32±17 versus 16±7 J·min(-1); p<0.01); EMGdi (37.3±17.3 versus 17.9±11.7% of maximum; p<0.001); and EMGdi to transdiaphragmatic pressure ratio (0.87±0.38 versus 0.52±0.27; p<0.01). Dyspnoea-ventilation slopes were significantly higher in mild COPD than controls (0.17±0.12 versus 0.10±0.05; p<0.05). However, absolute dyspnoea ratings reached significant levels only at high levels of ventilation. Increased respiratory effort and work of breathing, and a wider dissociation between diaphragmatic activation and pressure-generating capacity were found at standardised work rates in subjects with mild COPD compared with controls. Despite these mechanical and neuromuscular abnormalities, significant dyspnoea was only experienced at higher work rates.
More Related Videos


Related Concept Videos
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:23
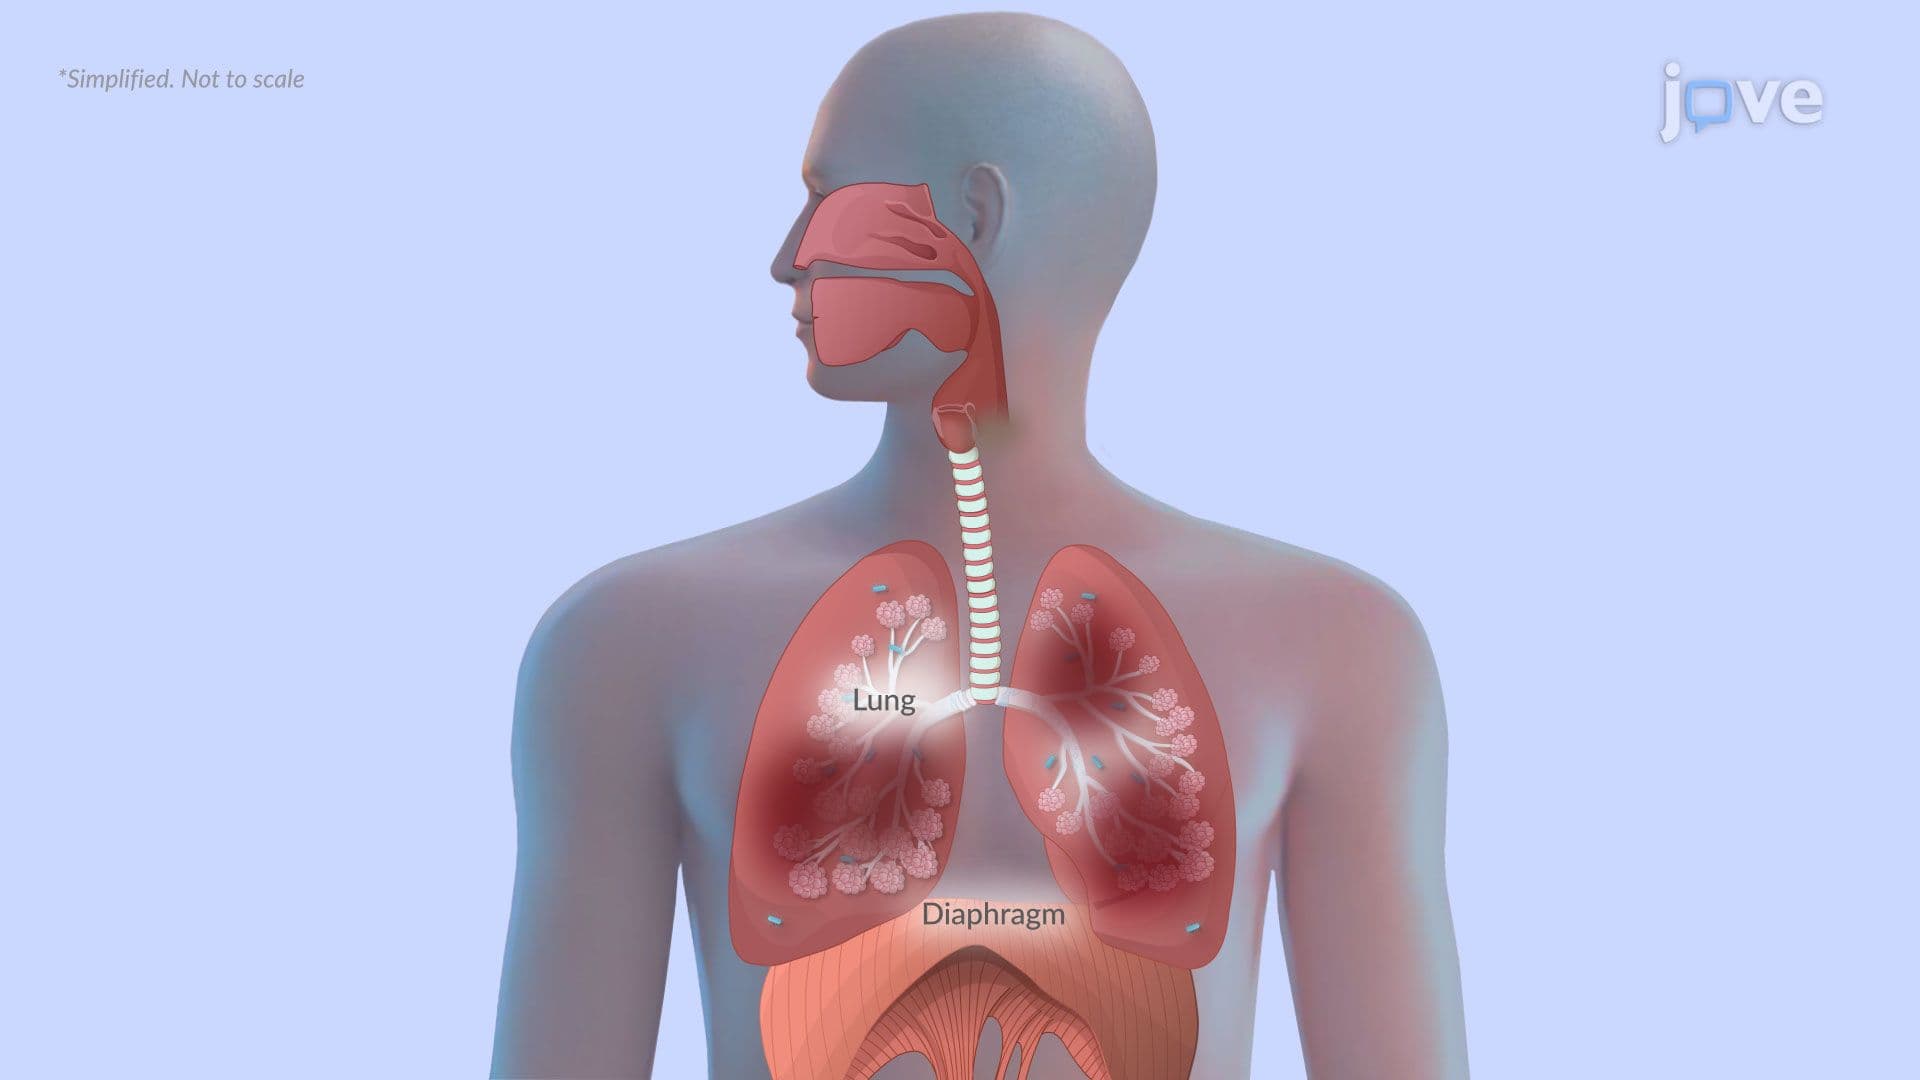
Chronic Obstructive Pulmonary Disease I: Introduction
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:26
COPD: Management Using Bronchodilators and Corticosteroids