Related Experiment Video
Updated: Apr 25, 2026
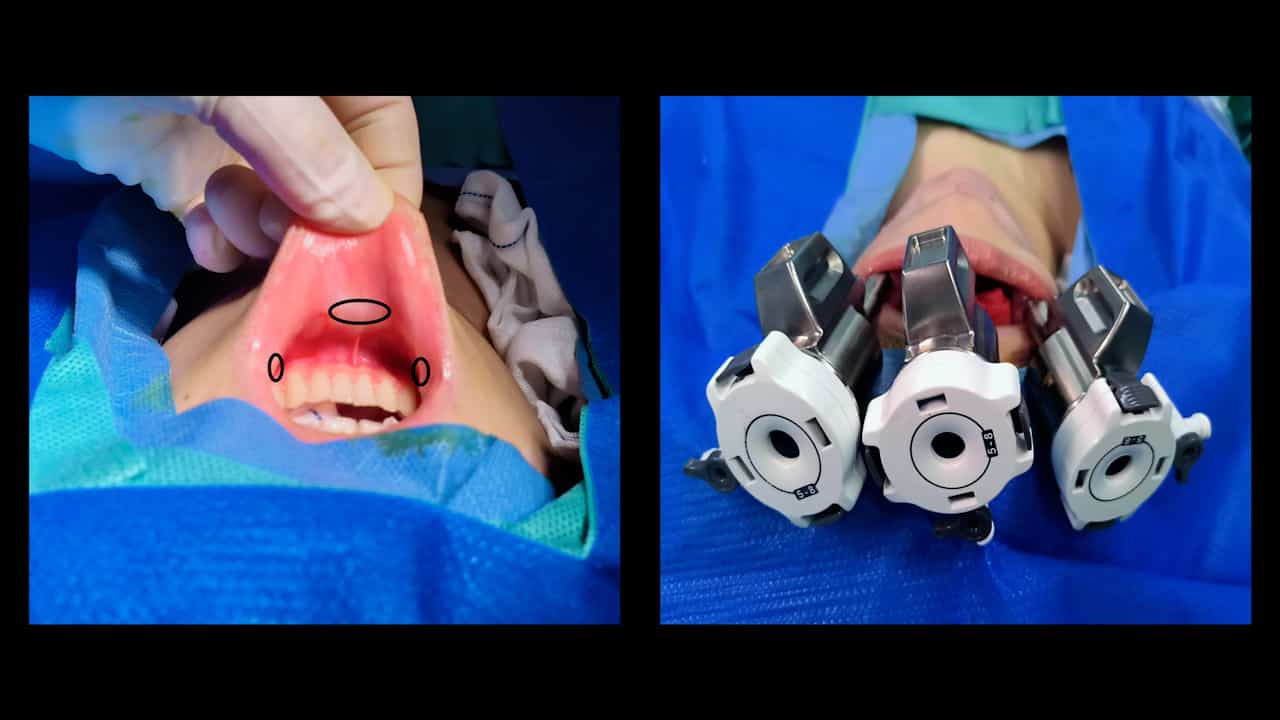

Identification and Protection of the Recurrent Laryngeal Nerve during Transoral Robotic Thyroidectomy
Published on: October 24, 2025
Patients undergoing total laryngectomy: an at-risk population for 30-day unplanned readmission
Evan M Graboyes1, Zao Yang1, Dorina Kallogjeri1
1Department of Otolaryngology-Head and Neck Surgery, Washington University School of Medicine, St Louis, Missouri.

Importance:
Patients undergoing total laryngectomy are at high risk for hospital readmission. Hospital readmissions are increasingly scrutinized because they are used as a metric of quality care and are subject to financial penalties.
Objective:
To determine the rate of, reasons for, and risk factors that predict 30-day unplanned readmission for patients undergoing total laryngectomy.
Design, Setting, And Patients:
Retrospective cohort study at a single academic tertiary referral medical center. The study population comprised 155 patients who underwent total laryngectomy with or without flap closure between January 2007 and December 2012 as either a primary treatment or salvage treatment for prior nonsurgical management.
Interventions:
Total laryngectomy.
Main Outcomes And Measures:
Rate of 30-day unplanned readmission, readmission diagnoses, and risk factors for unplanned readmission. Univariable and multivariable logistic regression were performed to identify risk factors for unplanned readmission within 30 days of discharge.
Results:
The 30-day unplanned readmission rate for patients following discharge after total laryngectomy was 26.5% (41 of 155). The most common readmission diagnoses were pharyngocutaneous fistula (27% of readmissions; n = 11) and stomal cellulitis (16% of readmissions; n = 7). The median time to unplanned readmission was 7 days. Thirty-four percent of readmissions (14 of 41) occurred within 3 days of discharge. Significant predictors of 30-day unplanned readmission on multivariable analysis were postoperative complication after discharge (odds ratio [OR], 11.50; 95% CI, 4.10-32.28), visit to the emergency department within 30 days after discharge (OR, 5.25; 95% CI, 1.84-14.99), salvage total laryngectomy (OR, 3.52; 95% CI, 1.56-13.12), and chyle fistula during the index hospitalization (OR, 5.25; 95% CI, 0.86-29.92). The discriminative ability of the model to predict unplanned readmission, as measured by the C statistic, was 0.88.
Conclusions And Relevance:
Patients undergoing total laryngectomy are an at-risk patient population with a high rate of unplanned readmission within 30 days of discharge. By identifying the risk factors that predict 30-day unplanned readmission, these data can be used to design and implement quality-improvement interventions to decrease readmissions.
Related Concept Videos
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals....
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:16
Tracheostomy Care I: Pre-procedural Steps
Required Equipment
The equipment necessary for tracheostomy care includes: