Related Experiment Video
Updated: Apr 25, 2026
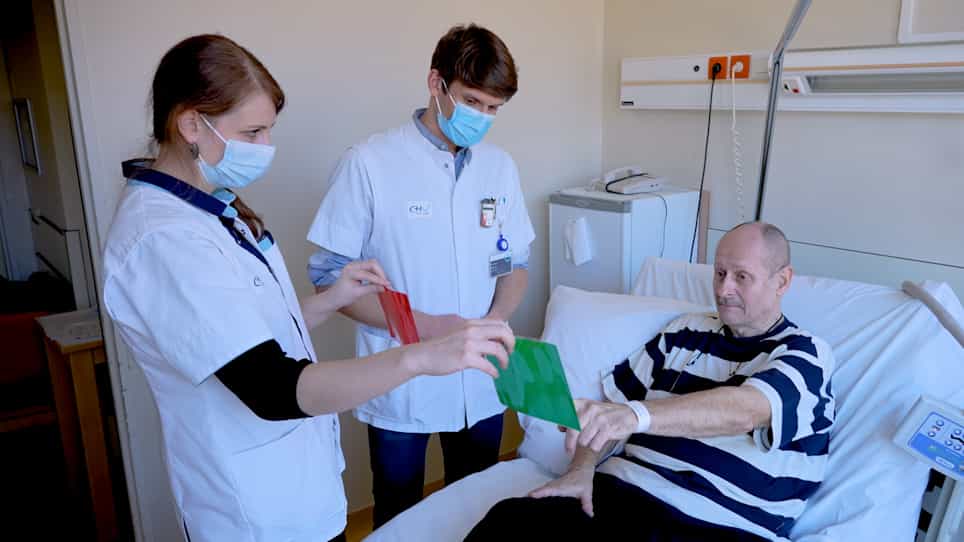

SECONDs Administration Guidelines: A Fast Tool to Assess Consciousness in Brain-injured Patients
Published on: February 6, 2021
[Intensive care unit survey of cognition status of donation after brain death]
Chunhua Yang1, Xuexia Chen, Li Chen
1Department of Critical Medicine, First Affiliated Hospital, Sun Yat-sen University, Guangzhou 510700, China.

Insights
Cognitive gaps in donation after brain death (DBD) among medical staff and families, coupled with concerns about legislation and cultural beliefs, hinder organ donation conversion rates. Establishing a professional transplant coordination team is crucial for national DBD education.
Area of Science:
- Medical Ethics
- Organ Transplantation
- Public Health
Context:
- Assessing the understanding of donation after brain death (DBD) among healthcare professionals and potential donor (PD) families is vital for improving organ donation rates.
- Intensive care units (ICUs) are critical settings for identifying potential donors and engaging with families regarding organ donation.
- Previous studies highlight varying levels of awareness and acceptance of DBD across different populations.
Purpose:
- To analyze the cognitive status of donation after brain death among medical staff and potential donor family members in intensive care units.
- To identify key factors influencing the decision-making process for organ donation after brain death.
- To inform strategies for enhancing organ donation rates through targeted education and support.
Summary:
- Medical staff demonstrated high recognition of DBD significance and acceptance of brain death equivalence but showed gaps in knowledge regarding specific donor criteria and management protocols.
- Family members exhibited high acceptance of brain death equivalence and DBD significance, yet lacked awareness of brain death itself, with cultural beliefs and family opposition being major barriers to donation.
- Low conversion rates of potential donors are attributed to cognitive deficits in DBD understanding, medical staff concerns about legislation, and traditional family beliefs.
Impact:
- Findings underscore the need for comprehensive national education on organ donation after brain death.
- Recommendations include establishing a professional transplant coordination team to improve DBD knowledge and address associated concerns.
- Improving understanding and addressing cultural barriers can significantly increase organ donor conversion rates and save more lives.
Objective:
To explore the development approach of donation after brain death through analyzing the cognition status of donation after brain death among medical staff and potential donor (PD) family members of intensive care unit (ICU).
Methods:
Analysis was conducted for the cognition of donation after brain death among 149 ICU professionals and 879 PD family members at 89 hospitals from July 2011 to April 2013.
Results:
Medical staff: 100% (149/149) recognized the significance of donation after brain death, 96.6% (144/149) approved of donation after brain death, 85.9% (128/149) knew about brain death criteria, 94.0% (140/149) accepted the equivalence of brain death as death. Awareness of standard of potential donor: 13.4% (20/149) were aware of donation age, 40.9% (61/149) familiar with the donation criteria of liver and kidney function and 44.3% (66/149) knew the hepatitis B donation criteria. Necessity of brain death legislation: 79.2% (118/149) considered it necessary, 14.8% (22/149) unimportant and 6.0% (9/149) not necessary. How to manage donation after brain death: 43.6% (65/149) did not know how, 79.2% (118/149) were afraid and 30.9% (46/149) never considered. Family members: 0/879 knew about brain death, 98.6% (867/879) accepted the equivalence of brain death as death, 99.5% (875/879) approved the significance of donation after brain death and 47.0% (413/879) agreed with donation after brain death. The reasons for approving the significance of donation after brain death but not agreeing with donation: 80.5% (372/462) required a full corpse after death and 19.5% (90/462) for other reasons. Reasons for agreeing with donation but refuse: 50.1% (207/413) were opposed by other family members, 11.4% (47/413) beware of neighbors' chat about their organ trading, 9.2% (38/413) hoped to be paid and 8.0% (33/413) for the others.
Conclusions:
The cognitive deficits of donation after brain death for medical staff and family members, medical staff's worries about brain death legislation and traditional thoughts of family members are the main reasons for a low conversion rate of PD. A professional transplant coordinating team should be built for national organ donation knowledge education.
More Related Videos
 09:54
Lung Rapid Recovery Procurement Combined with Abdominal Normothermic Regional Perfusion in Controlled Donation after Circulatory Death
Published on: August 15, 2022
 07:49
Large-Animal Model of Donation after Circulatory Death and Normothermic Regional Perfusion for Cardiac Assessment
Published on: May 10, 2022